Category: Sexual Dysfunction

  • Understanding Deep Penetration Pain: What You Need to Know

    Introduction:

    Intimate topics like painful intercourse, especially deep penetration pain, can be uncomfortable to discuss. However, it’s crucial to recognize that many women experience discomfort during sex that lingers beyond the initial entry. Some describe it as a feeling that their partner is hitting something, while others experience a more widespread ache in their pelvic region.

    In this blog, we’ll explore three common reasons behind deep penetration pain and how seeking help from trained therapists can make a significant difference.

    1. Tailbone Troubles: Imagine a scenario where you’ve had a fall, and it affected your tailbone. Well, that could lead to deep penetration pain. When the tailbone gets pushed forward or to the side due to an injury, and the ligaments and tissues around it are also damaged, it can heal in this misaligned position. Women dealing with this condition may face painful intercourse, discomfort during bowel movements, and difficulty sitting for extended periods.
    2. Cervix Complications: The cervix, a crucial part of the female reproductive system, is held in place by ligaments attached to its sides. However, various factors like infection, inflammation, surgery, or trauma in the vaginal area can lead to the formation of adhesions. These adhesions can pull the cervix out of its normal alignment or tighten it, causing significant pain when deep penetration occurs.
    3. The IUD Influence: Intrauterine Devices (IUDs) are known for their effectiveness in preventing pregnancy. They work by causing inflammation in the uterus. Unfortunately, this inflammation can also result in pain during intercourse. Furthermore, it contributes to the formation of adhesions in the uterus, causing stenosis of the cervix, also known as a stenotic cervix. Even if the IUD has been removed, these adhesions can continue to cause discomfort during sex.

    Seeking Help and Finding Relief for Stenotic Cervix: The good news is that there’s help available for women dealing with deep penetration pain. Therapists trained to address adhesions have achieved remarkable success in treating this issue. In a study, 96% of patients reported a significant decrease in intercourse pain after receiving therapy.

    Conclusion: Deep penetration pain is a real concern for many women, but understanding its common causes can be the first step toward finding relief. Whether it’s a tailbone issue, cervical complications, or IUD-related discomfort, there are solutions available to improve your quality of life and intimate experiences. Don’t hesitate to seek help from trained therapists who can help you on your journey to a pain-free and fulfilling sex life.

    Cervical stricture can be caused by various factors, including congenital abnormalities, scarring from procedures like cone biopsies, or infections that lead to the formation of scar tissue.

    Learn more about our all-natural, hands-on treatment for sexual dysfunction and painful intercourse.

  • Hysterectomy Pain

    Hysterectomy Pain

    Discover lasting relief from post-hysterectomy pain with Clear Passage® Physical Therapy’s Free Consult and Request Info – learn how their unique, non-surgical approach has helped countless women regain comfort and quality of life, and take the first step towards your personalized treatment plan today. To learn more, visit our Apply to Therapy page.

    We Treat Hysterectomy Pain Naturally, Without Surgery or Drugs

    Hysterectomy is a major surgery performed in some of the deepest parts of the body. This surgery can cause adhesions to form, creating pain that lasts long after the surgery. Clear Passage® Physical Therapy is a world leader in the non-surgical, drug-free treatment of pelvic pain and adhesions, with over 30 years of experience treating post-hysterectomy pain. Studies and citations published in peer-reviewed U.S. and international medical journals find that this physio/physical therapy significantly decreases adhesion-related pelvic pain. 

    Complete our online Request Consultation form to receive a free phone consultation with an expert therapist and learn whether our therapy can help you.

    For some women, the pain begins soon after surgery; for others, it may start months or even years after the procedure. Without therapy, most women find the pain never goes away; it remains or gets worse over time.

    Hysterectomy Pain Overview

    The most common surgical technique for hysterectomy is abdominal surgery. To access the uterus, the surgeon must first cut through several structures, including the skin and the peritoneum (tissue enclosing the abdominal and pelvic organs). After surgery, all of the cut tissues must heal.

    Doctors generally expect complete recovery within four to eight weeks. For vaginal surgery, recovery usually occurs within one to two weeks. Either approach presents the possibility for adhesions to form deep within the abdomen, pelvis, or both. 

    Hysterectomy has become a fairly common surgery. In fact, so many women struggle with issues related to the pelvis that one in three women in the U.S. over age 60 has had a hysterectomy. (Office of Women’s Health, 2009b)

    Of the 600,000 women who undergo hysterectomies in the U.S. every year, most recover within the given time frame and return to pain-free lives. (Office of Women’s Health, 2009b) However, a study in 2007 found that 32% of women who underwent hysterectomies experienced chronic pelvic pain one year after their hysterectomy. The study also found that a vaginal surgery (rather than an abdominal surgery) did not significantly lower the risk of chronic pain. (Brandsborg et al., 2007)

    Adhesions are thick strands of collagen that form to help the body heal and repair after infection, trauma, surgery, or various other injuries. Although the body needs these strands to help tissue repair, adhesions can spread, with the unwanted side-effect of binding and restricting structures that were previously mobile. This causes tightness in many women after a hysterectomy.

    The tissues of the pelvis are extremely delicate and are meant to glide easily over each other. During a hysterectomy, the surgeon cuts or burns through pelvic tissues to remove the uterus and sometimes other structures. Tiny but powerful collagen fibers rush in to repair the tissues at the surgical sites. Attached to each other with molecular-chemical bonds called cross-links, the fibers create adhesions (internal scars) as the first step in the process of healing. Thus, adhesions form naturally after surgery. Pain and problems come when these adhesions spread. They can act like a powerful glue, binding neighboring structures – such as the intestines, bowels, vagina, or bladder.

    Symptoms of Adhesions After a Hysterectomy

    When adhesions form after hysterectomy, women can experience a variety of side effects, including:

    • Pelvic or intercourse pain
    • Low back pain (due to adhesive pulls into that area)
    • Uncomfortable tightness or pulling
    • Decreased desire, lubrication, and orgasm
    • Pain with or after urination
    • Constipation or painful bowel movements
    • Small bowel (intestinal) obstruction (SBO)
    • Cramps after hysterectomy
    • Tightness after hysterectomy

    Symptoms can range from moderate discomfort to severe, recurring pain or tightness. In the case of SBO, it can become life-threatening as adhesions block the intestines, preventing food from passing through the digestive tract.

    Intercourse pain and sexual dysfunction after hysterectomy

    Following a hysterectomy, a woman can expect intercourse to be uncomfortable the first couple of times. If a woman has had one or both ovaries removed, she may also experience a decrease in lubrication and desire as her body goes through menopause.

    If a woman feels pain with intercourse after six weeks, she may have a ‘mechanical’ problem, such as vaginal adhesions or adherent pelvic ligaments. Many women feel that if they continue to try and push past the pain, the pain will eventually go away. If it doesn’t resolve after three or four attempts, we generally find that adhesions have formed in this area, pulling or restricting the vagina or attaching its delicate tissues to nearby structures, causing pain with intercourse.

    The Journal of Sex & Marital Therapy classified female sexual function into six measurable domains: desire, arousal, lubrication, orgasm, satisfaction, and pain. (Rosen et al., 2000) Although a woman who has undergone a hysterectomy may initially experience decreased function in these areas, function should return within a few weeks. If they do not, it is a sign that adhesions may be restricting the area, preventing normal sensation and function. In our published studies on this phenomenon, we found that treating the adhesions can significantly restore function in these important areas.

    Abdominal hysterectomy is a common but major surgery. The physician cuts through the skin, muscles, fascia, and abdominal wall to expose and then remove the uterus. Some physicians perform vaginal or laparoscopic hysterectomy, hoping to avoid new adhesions. We find the same types of post-surgical adhesion pain can occur with either approach.
    Whether the surgery is performed vaginally or as an open surgery, cutting so deeply into the body can create significant adhesions as the body heals. These can spread into pain-sensitive structures, causing pain or dysfunction.

    Treatments

    Clear Passage® Treatment

    The Clear Passage® Approach is designed to reduce or eliminate adhesions cross-link by cross-link. It has been shown in numerous peer-reviewed medical journals to decrease pain and improve function without surgery or drugs.

    We know pelvic adhesions well. Thirty years ago, our Director, physical therapist Belinda Wurn, developed severe adhesions after pelvic surgery and radiation therapy. Unable to work due to chronic pelvic pain and having seen the devastating and debilitating effects of pelvic adhesions in her own patients, she was determined to find a non-surgical way to address chronic pelvic pain and to decrease or eliminate pelvic adhesions.

    With her husband, massage therapist Larry Wurn, Belinda took a much deeper look at the etiology and biomechanics of adhesion formation. They found that the molecular bonds that attached each of the tiny collagen fibers to its neighbor appeared to dissipate or dissolve with certain site-specific manual techniques. With this knowledge, they created the Clear Passage® approach to free adhesive bonds and return pain-sensitive structures to a more functional, pain-free state.

    Most patients report significant to profound pain relief and a return to normal life, facts that are reflected in dozens of testimonials and numerous published studies about our work.
    Clear Passage®️ offers a non-surgical treatment. Our therapists focus on breaking down the cross-links that comprise adhesions (shown at a microscopic level). As the adhesive pull is diminished, the pain disappears.

    Other Treatments for Hysterectomy Pain (Surgery, Drugs)

    Until recently, lysis (burning or cutting adhesions during laparoscopy or laparotomy) was the only option to remove adhesions in the pelvis. While lysis of pelvic adhesions can be effective, surgery has major drawbacks:

    • It carries risks associated with anesthesia or infection.
    • Surgeons can mistakenly cut off or burn nearby or underlying structures.
    • Despite the best skills of the finest surgeon, the body tends to create more adhesions as it heals from the very surgery designed to remove them.
    Until recently, surgery to cut or burn adhesions was the only choice for treating post-hysterectomy adhesions. Despite excellent surgical skills, the procedure can cause adhesions (internal scars) to form.

    A study in Digestive Surgery showed that 55% to 100% of women develop adhesions following pelvic surgery. Another study reported that 35 percent of all open abdominal or pelvic surgery patients were readmitted to the hospital more than twice to treat post-surgical adhesions during the 10 years after their original surgery. Thus, pelvic surgery itself has been implicated as a major cause of adhesion formation, and many patients become trapped in a cycle of surgery-adhesions-surgery – with no end in sight. Clear Passage® therapists provide the end to that cycle for many women. 

    Published Success Rates

    To view a full list of our published success rates, please visit our Success Rates page.

    Testimonials

    To read past patient success stories, please visit our Testimonials page.

  • Intercourse Pain

    Intercourse Pain

    “Intercourse used to be extremely painful for me. It became increasingly difficult when my husband and I tried for five years to become pregnant. After my treatment at Clear Passage®, intercourse pain decreased, and I later became pregnant!”​
    – Yvonne

    Eliminate Painful Sex, Improve Sexual Function

    Desire, lubrication, and orgasm should happen normally for all adults. When any of these are not happening, we look first for physical causes – and physical solutions.

    Clear Passage® is a world leader with over two decades of experience treating intercourse pain and female sexual problems with a non-surgical, hands-on physio/physical therapy. Clear Passage® is a world leader with over two decades of experience treating intercourse pain and female sexual problems with a non-surgical, hands-on physio/physical therapy. We have success rates over 90% for eliminating or dramatically decreasing dyspareunia (painful sex).

    Success Treating Lubrication & Orgasm Problems

    Studies published in peer-reviewed U.S. and international medical journals found that our therapy significantly improved all six areas of sexual function, including desire, arousal, lubrication, orgasm, satisfaction, and pain. 

    Complete the online Request Consultation form to receive a free phone consultation with an expert therapist and learn more.

    The female reproductive organs are susceptible to adhesion formation after a fall or accident, surgery, infection, or endometriosis. Invisible to the naked eye, tiny cross-links attach to injured tissues to start the healing process.

    Causes and Frequency of Sexual Dysfunction (Including Lubrication and Orgasm)

    Female sexual dysfunction (FSD) affects approximately 50% of all U.S. women and 43% of women aged 18-59. (Basson et al., 2000; Laumann et al., 1999) In 2000, the Journal of Sex & Marital Therapy classified female sexual dysfunction into six measurable domains: desire, arousal, lubrication, orgasm, satisfaction, and pain. (Rosen et al., 2000) Intercourse pain affects between 46% and 60% of all U.S. women (Heim, 2001; Mathias et al., 1996)

    Sexual intimacy and intercourse should provide some of life’s greatest pleasures. But because the female urogenital and reproductive organs are susceptible to adhesions (tiny but powerful internal scars), intercourse can become a time of pain, dissatisfaction, and embarrassment for many women.

    During the course of life, the female reproductive tract may be subjected to numerous traumas (e.g., falls or abuse), infections (vaginal, urinary, bacterial, or STDs), inflammations (PID, endometriosis), and surgery. Any of these conditions can lead to adhesion and scar tissue formation at the entrance or walls of the vagina, or in nearby structures. In fact, adhesions can form anywhere in the female reproductive tract, causing painful intercourse and decreased or absent sensation, desire, arousal, lubrication, or orgasm.

    Like tiny but very strong straitjackets, adhesions can bind the internal mechanisms of urogenital and reproductive tissues, or attach organs to other structures, restricting movement and function, and sometimes causing pain. Adhesions may act like a blanket, covering and muting the response of some of the delicate tissues that are responsible for sexual response – the vaginal opening, cervix, G-spot, and vaginal walls.

    Stepping back in magnification, collagen cross-links join to form tiny adhesions that bind structures together – even the microscopic muscle cells depicted here.
    Stepping back further, these tiny but powerful structures can attach to the vaginal wall, cloaking it like a blanket, preventing normal function, and often causing intercourse pain.

    Treatment Overview for Sexual Dysfunction

    Clear Passage® Treatment

    The focus of our therapy is to free these tissues from their adhesive constraints. In a remarkable percentage of cases, CP therapy has been shown to restore function and allow women to return to normal sexual function.

    As therapists with years of experience in these areas, we have decreased pain, increased sexual function, and restored the pleasures of intimacy and intercourse for many women. In doing so, we enrich their lives and those of their partners. We recognize and understand the private and intimate aspects of the areas we are treating. All of our work is performed with sensitivity and dignity, by caring professional therapists in private treatment rooms under guidelines established by the American College of Gynecology.

    Pain relievers, lubricants, and psychological counseling do not address the adhesions that cause the problem. Our hands-on therapy can help significantly, based on results published in major medical journals.

    Other Treatment Options

    Other treatment options for sexual dysfunction include medications to numb the pain. While sometimes effective, these medications only mask the symptoms, rather than treating the root cause of the problem: adhesions. 

    Published Results

    Scientific citations published in major gynecologic journals showed significant improvement in all areas of female sexual function for women who received our therapy. A study published in the peer-reviewed journal Medscape General Medicine (Wurn et al., 2004b) showed that after receiving the Clear Passage® Approach:

    • 78% of women had increased desire (libido)
    • 74% had increased arousal
    • 70% had increased lubrication
    • 56% had increased or first-time orgasms

    A second study published in the Journal of Endometriosis showed similar improvements in these areas for women who received our therapy. (Wurn et al., 2011) In fact, these published citations measured statistically significant improvements in all six major areas of female sexual dysfunction: desire (libido), arousal, lubrication, orgasm, satisfaction, and pain.

    To view a full list of published studies treating Sexual Dysfunction with the Clear Passage® Approach, please visit our Success Rates page.

    Pain decreased, and sexual function (desire, lubrication, orgasm) improved for most women in the studies after our therapy alone.

    Testimonials 

    To read past patient success stories, please visit our Testimonials page.

    Related Content:

    • What You Need to Know About Pelvic Adhesions

      What You Need to Know About Pelvic Adhesions

      What are Pelvic Adhesions?

      Many women are not receiving the education needed from their doctors about adhesions. Very few women even know they have adhesions. Most commonly known as “scar tissue,” adhesions are simply scar tissue that forms inside the body. Once formed, the body has no way to deal with the scar tissue, so it will remain in place and sometimes spread to neighboring structures.

      Adhesions consist of tiny strands of collagen that form around injured tissue as the body’s first step in the process of healing. Common areas of adhesion formation are areas affected by a prior infection, inflammation, or endometriosis. Pelvic adhesions can lead to a host of female health problems, ranging from infertility to chronic pain, including pain with intercourse. If you’ve had any kind of surgery, infection, injury, or endometriosis, there’s a good chance you have adhesions. We made a short guide that can help you figure out if you have adhesions after surgery.

      What Causes Pelvic Adhesions?

      You can see here that pelvic and abdominal adhesions can form all around the delicate structures of the body.
      • Surgery – Studies show that 55% to 100% of people who undergo pelvic surgery will develop pelvic adhesions. Cutting into the delicate tissues near your reproductive structures can result in a large amount of scar tissue growing around the healing site. Many of the women we treat for secondary infertility or chronic pelvic pain have undergone a prior C-section, hysterectomy, or appendectomy  (appendix removal).
      • Inflammation – Recurring inflammation is a very common cause of adhesions. Pelvic inflammatory disease (PID) is a major contributor to many of the infertility and pain cases we have treated. The constant inflammation causes scar tissue to grow in the pelvic area, often around the fallopian tubes or ovaries.
      • Infection/STIs – Sexually Transmitted Diseases (STDs) can lead to chronic infection and inflammation, which cause scar tissue to grow within the pelvis. The longer an infection or STD remains untreated, the more adhesions will form as the body attempts to surround and contain the infection. A major cause of blocked fallopian tubes is an untreated infection, as a result of chlamydia or gonorrhea.
      • Trauma – Contact sports, car accidents, falls, or work-related injuries are common traumas that can cause the formation of pelvic adhesions. Since the body’s first step in healing is to create adhesions to contain and isolate the injury, almost everyone has adhesions somewhere in their body.
      • Chronic conditions – Conditions that don’t have a definitive cure and recur periodically are considered chronic conditions. Two conditions responsible for a large portion of pelvic adhesions are polycystic ovarian syndrome (PCOS) and endometriosis. Both conditions share characteristics that result in adhesion formation. Chronic inflammation is explained in detail above, and abnormal growths within a woman’s reproductive tract are discussed. PCOS gets its name from the cysts that form on a woman’s ovary. Both the cysts and the surgeries needed to remove the cysts will cause adhesions. Endometriosis occurs when endometrial tissue forms outside of the uterus. Endometriomas and endometrial implants can become inflamed and cause scar tissue to form around the site, causing endometriosis infertility, period, or intercourse pain.
      • Radiation Therapy – We have treated many previous cancer patients for chronic pelvic pain because of radiation therapy. Radiation therapy is a treatment that can cause significant scarring and mechanical dysfunction inside a woman’s abdomen and pelvis. We often hear these patients describe their pain as a “stuck” or “tight” feeling that won’t go away.
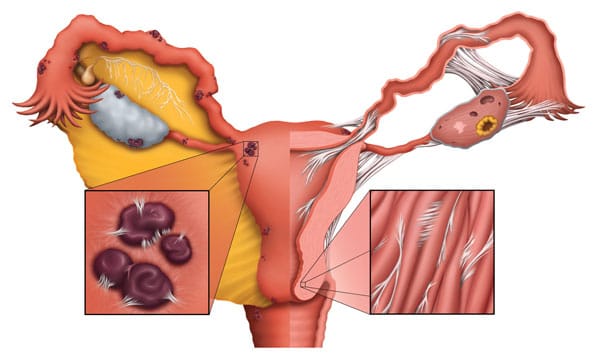
      At left, we can see adhesions at sites of endometriosis. At right, adhesions are shown on the inside of the uterus and fallopian tubes, decreasing fertility. At the bottom, adhesions within the muscle of the cervix can cause pain with deep intercourse.

      Symptoms and Conditions Caused by Pelvic Adhesions

      • Blocked fallopian tubes – One of the most common forms of infertility caused by adhesions is blocked fallopian tubes. Adhesions wrap around delicate structures inside the reproductive tract, preventing the reproductive system from working normally. Adhesions can restrict the flow of sperm through the fallopian tubes, preventing the fertilization of an egg. Most physicians no longer perform surgery on these delicate structures because post-surgical adhesions tend to block the tubes once again when the body heals from the surgery.
      • Hydrosalpinx – Another common tubal blockage is a hydrosalpinx. This occurs when fluid collects in the fallopian tube – generally as the result of an infection. As adhesions form at the end of the tube closest to the ovary, the tube swells, much as your knee might swell after a knee injury. Hydrosalpinx usually indicates a totally blocked tube; in the rare case that the end is open, the sperm still tend to get lost in a large amount of fluid in the tube, greatly decreasing the chance for conception and increasing the chance for an ectopic pregnancy, in which the fertilized egg becomes stuck in the tube.
      • Unexplained infertility – Adhesions don’t show up on most diagnostic tests. In order to verify that a patient has adhesions, an exploratory surgery is required to directly visualize the adhesions. Unfortunately, since most patients are unaware of adhesions, the question is never asked: “Maybe my infertility is caused by adhesions?” This can lead to many women suffering from unexplained infertility.
      • Prior surgery – Surgeries are sometimes necessary to save a woman’s life, as in the case of an appendectomy. There may be less urgency to perform surgery in the case of undiagnosed pain. In these cases, a doctor may suggest doing an exploratory surgery to directly visualize the pelvic contents. Because adhesions form after most pelvic surgeries, the very surgery to correct a problem can be the cause of adhesion formation as the body heals.
      • Chronic pain – Stuck, tight, immobile, constantly uncomfortable. These are all common descriptions we hear from patients suffering from adhesions. Because adhesions bind to structures and create constant tension, it is no wonder that so many patients with adhesions also suffer from chronic pain.
      • Sexual dysfunction – Some non-surgical treatments are available for women with intercourse pain (dyspareunia) or other sexual dysfunction. Studies on our work in this area have shown that women have an increase in every measurable criterion of their sexual health (desire, orgasm, lubrication, pain, and arousal) after being treated for adhesions.

      Treatments for Pelvic Adhesions

      Experience relief from debilitating pelvic adhesions with Clear Passage® Physical Therapy’s Free Consult and Request Info – discover how their unique, non-surgical Clear Passage® Approach has helped countless women overcome infertility, chronic pain, and sexual dysfunction caused by internal scarring, without the risks of additional surgery or medication. To learn more, visit our Apply to Therapy page.

      Few options exist for treating pelvic adhesions. Many treatments are aimed at treating the symptoms of adhesions, rather than the adhesions themselves. Following the Hippocratic Oath that all physicians should adhere to, we have always believed that a natural, non-surgical, and drug-free approach should be the first step in the treatment of adhesions. Below are the options we see that have passed scientific scrutiny and been found to be effective, listed from safest to most invasive:

      • Manual Physical Therapy – A non-surgical, all-natural treatment plan is what we consider the best treatment for adhesions. Clear Passage® has been researching and treating patients with adhesions for over 25 years. The Clear Passage® Approach (CPA) is a hands-on therapy that focuses on detaching and weakening adhesions inside the body. Helping patients have natural pregnancies, live a pain-free life, and avoid future surgeries is our number one goal.

      If you or a woman you know is suffering from the symptoms above, we encourage you to complete a contact form or call us at 1-352-336-1433. You will be able to schedule a phone consultation with a member of our patient support team at no cost, and learn whether our non-surgical and drug-free treatment is right for you.

      • Pain Medications – The rise in chronic pain conditions has been met with a rise in pain medication prescriptions. The opioid epidemic is a well-known phenomenon in America. Pain medication simply masks pain; they do nothing to address the cause of the pain. They do not provide permanent solutions; further, they can lead to severe digestive issues along with addiction and dependency. Pain medications should be considered a temporary palliative measure while the patient searches for an actual treatment.
      • Surgery – Lysis (destruction) of adhesions by cutting or burning them during surgery is one of the most common ways to combat adhesion growth. Many surgeons note that this isn’t a permanent solution and often leads to more surgeries, because surgery is the number one cause of adhesions. Surgery also has risks, such as the risk of anesthesia, complications, or infection, and “inadvertent enterotomy,” in which a surgeon mistakenly cuts into or through an organ s/he had not intended to, in the crowded and adherent structures of the pelvis.
    • Adhesions in the Body: Presentation by Larry Wurn (Video)

      Adhesions in the Body: Presentation by Larry Wurn (Video)

      Larry Wurn, LMT, co-founder of Clear Passage®, presents an overview of 30 years of studying and treating adhesions. With images compiled from a presentation at a conference of physicians, the video provides an in-depth overview of the biomechanics of adhesion formation and the ways in which manual physical therapy can be an effective treatment. We thank endogyn.com for some of the remarkable images of adhesions they provided for this educational video.

      Unlock the secrets of treating adhesions with Clear Passage® Physical Therapy’s groundbreaking approach – Request Information and schedule your Free Consultation today to learn how our expert therapists can help you overcome pain and dysfunction, then visit our Apply to Therapy page to start your journey towards a life free from adhesion-related issues.

      Transcription

      I’m Dr Richard King, a board-certified obstetrician-gynecologist with 40 years of experience. I regularly perform surgeries two days a week during my professional career. In addition, I had the opportunity to conduct Clinical Research in Gynecology and other fields of medicine. I met Larry and Belinda W about 20 years ago. They told me they were having success treating blocked Fallopian tubes in their physical therapy practice using just their hands to clear adhesions and open the Fallopian tubes.

      Naturally, I was quite skeptical. But after reviewing several of the charts from their physical therapy clinic, I realized they were getting results that would be difficult to achieve in surgery, and I’m considered a very good surgeon. I have followed the Wurns and their treatment of adhesions with absolutely no remuneration for the last 20 years for two reasons.

      One, I’m fascinated with what they do and the results they achieve in several conditions normally treated with surgery or for which there is no effective medical treatment.

      Two, I believe this work is important to medicine as a conservative therapy that could eliminate many surgeries. Belinda and Larry have each treated roughly 40,000 patient hours over their career. They have published studies in scientific reports and in some of the most respected journals in the United States, including Fertility and Sterility, Gastroenterology, the Journal of Endometriosis, and WebMD’s Medscape General Medicine, edited by George Lundberg, the former editor of the Journal of the American Medical Association.

      I hope you’ll find this guided trip through three decades of their investigation of the manual treatment of adhesions to be as fascinating as I do. I give you a man I’m proud to call my friend and colleague, Larry Wurn.

      Hello, and thank you for that kind introduction. I am Larry Warren. My wife and I, physical therapists, have been treating adhesions and involved with adhesions for 30 years of our professional careers. Initially, we began treating adhesions and investigating them for very personal reasons through a nightmare we were undergoing; then, through hundreds, and finally thousands of patients, we started gathering data.

      Gathering physicians and biostatistical scientists to design and publish studies on whether or not we could actually treat adhesions non-surgically, manually using just our hands, the data is pretty compelling, we think. I’ll let you make your own decisions.

      The upside of this is that if adhesions can be broken apart non-surgically, and we’re not talking about just You can massage that and that’ll go away. No, that’s kind of far-fetched, but what is the actual structure of adhesions? What can we do, and what data do we actually have that have been published in peer-reviewed journals that show that adhesions can be broken down and decreased, perhaps eliminated non-surgically?

      The upside potential is huge for patients, for physicians, and for insurers. Certainly, patients don’t risk undergoing another surgery. Surgery is the normal treatment for adhesions when they get bad enough. A surgeon has to go in there and cut or burn adhesions; the problem is that no matter how brilliant and skilled the surgeon, the body creates new adhesions to heal from the surgery, so with each surgery, you develop more and more adhesions- at least many of these patients do, and there’s good data on this. Other risks include the cost certainty for insurers, which is a big deal for the surgeon, the surgical attendants, the anesthesiologists, and the renting of the surgical suite.

      Those of you who have read the latest data on the effects of anesthesia and multiple anesthetics on the brain know the risks there, and the information coming out is pretty compelling that there is a significant risk for a lot of patients with general anesthesia. The risk of inadvertent ostomy is when a surgeon goes in there, and he or she is looking around, trying to cut through adhesions, and some of these patients are so adhered that it’s really difficult to see what’s going on; you can inadvertently cut the bowel or intestines. A little bit leaks out, and suddenly you’ve got contents of the bowel in a warm, moist, dark environment; then you close that patient up, and three days later they’re in excruciating pain.

      They’re developing peritonitis; you have to open them back up in many cases, pour antibiotics in, and allow that patient to heal from the inside out, creating a huge scarring situation, of course, and adhesions.

      Being internal scars, that is the case where you’re actually intentionally cutting the belly to remove adhered, diseased, or necrotic tissue and reclosing the belly.

      We’ll look at that data. We’re not talking about a simple massage here; the idea that you could actually just go in and massage these is a little far-fetched, but we’re going to look more deeply at the structure of adhesions, how they are composed, and, um, how this can work so you can make your own determinations.

      At the end of this, we will go through the 30 years pretty quickly, now looking at where we started with the structure of adhesions, what data we have found, and where we’re going next.

      In 1984, my dear wife went to a physical therapist from the University of Florida and developed massive adhesions after 72 hours of internal radiation therapy and 40 external radiation treatments. They put her in a lead-lined room with radioactive pellets inserted inside of her and said You know it’s dangerous for any of us to be in this room for more than about five minutes, but don’t worry; we’ll keep you drugged. We really need to get rid of this tumor.

      A year after that experience, she began having debilitating pain whenever she walked, moved, or breathed. She was in excruciating pain.

      I saw my beautiful and brilliant wife just deteriorating before my eyes. We talked to our doctors about it. They said, “Well, you cured our cancer, you know, but you really don’t want us to operate there. I mean, this vaginal tissue and pelvic tissue is so delicate; we’re just going to create more adhesion; she’ll just have to learn to live with it.”

      We were not interested in following that prognosis. We know that she had a frozen pelvis where everything was stuck together; all of the organs in her pelvis were just adhered together and stuck like in a massive straitjacket.

      We could not accept the diagnosis that you’re just going to have to learn to live with the pain. We began to investigate our own ways that we could perhaps decrease adhesions without surgery. We learned that adhesions form naturally in the body whenever and wherever the body heals. They rush in to surround the area that’s been injured; once they form, if they don’t dissipate within 7 to 10 days.

      They’re with you for life. The problem is that adhesions are made of collagen, and collagen covers virtually every structural cell in the body, so the body has no way to dissolve or detach adhesions on its own. Once they are formed, they stay there; they either stay the same or they get worse over the course of life.

      This is probably what my wife’s body looked like a year after her radiation therapy, where everything was stuck together, the adhesions forming ropey structures that glue or squeeze structures that should be able to move freely. It causes dysfunction; infertility can stop literally organ function, and can cause a tremendous amount of pain, gram for gram.

      We know that adhesions are actually stronger than steel. They’ve been estimated at roughly 2,000 lb per square inch, so you can lift a horse with a square inch of them. When they attach to structures, they can cause significant pain, and the surgical answer up till now has always been, well, let’s cut those out, let’s burn them. Certainly, you can cut or burn the ones that you can see; you can’t cut or burn the ones that are inside an organ without cutting into that organ, causing more damage, even when you just cut or burn the external adhesions.

      The data shows that after surgery, and this was a study from several hundred thousand patients- a 50-year study showed that 55 to 100% of pelvic surgeries and 90% of abdominal surgeries cause adhesions to form from digestive surgery, and you have the reference there; you can pull it off our website if you like

      Looking a little deeper, here are some adhesions as they form. They’re like tiny strands of collagen, here depicted in a muscle forming from cell to cell within a muscle. You can imagine that it’s virtually impossible for a surgeon to get to those without injuring the muscle. Looking even closer, we discover that these tiny strands themselves attach to each other and to the underlying structure with a molecular chemical bond.

      That bond we found is susceptible to being disrupted or detached by using sustained pressure and some other techniques that we use; certainly, we have to be very site-specific and understand the anatomy very well.

      Understand where we are in the body and be able to understand what’s adhered, but given that we find that we can be very successful with many of these patients, it takes a bit of time; as those bonds dissolve, that strand detaches, and sure, it’s probably still attached at the other side, but there’s already collagen covering every cell on the body.

      The important thing is that it detaches from the next one and the next one and the next one, so it becomes like pulling out a run in a sweater in a three-dimensional sweater in very slow motion for us. Looking at other depictions, we started after we treated my wife; we started treating other patients who came to us with pain, and we were initially surprised when women with block Fallopian tubes started reporting they were becoming pregnant and their tubes were opening.

      It was very easy to check that because there’s an HSG dye test that is inserted into the uterus, where we radiographically view that you can see it has not come out of this particular tube. There’s a hydrosalpinx contributing to the swelling in that tube as well. After therapy has come through one of the tubes, there is still a hydrosalpinx in that particular tube.

      But this is just one of them when we talk about hydrosalpinx. If you like, we wrote to the gynecologist in town, and we said, you know, we’re seeing results in opening blocked Fallopian tubes. The chief of staff of the hospital, Richard King, whom you just met, called us in as a research gynecologist and surgeon with 30 years’ experience. At that time, he said, “What’s this about opening blocked fallopian tubes?”

      We handed him half a dozen charts, and he looked at them and said, “Gosh, you’re doing things with your hands I’m not sure I could do them surgically!” I said, “Well, is that okay?” and he said, “Well, yeah, it’s actually really great!” It’s neat that you have done any research; no, would you like to be sure? Let’s research this.

      I’ll join you if you like. You need to have somebody who understands research, and I’ll just chip in my time. I’m pretty fascinated.

      So we began doing research on our patients and presented at the American Society of Reproductive Medicine, a meeting of about 9,000 physicians. We did a couple of posters and an oral presentation on decreasing adhesions for hydrosalpinx; in this particular poster, improving some other functions in women with endometriosis, and followed up with a study we published, which is now available at the US National Library of Medicine PubMed and Alternative Therapies in Health and Medicine on opening blocked Fallopian tubes.

      At the time we we just had a very small I think there were 28 patients in this study- and our success rate for opening blocked tubes was 61%, still pretty good, we thought, after just manual therapy. Just using our hands pulled these adhesions apart, but it was a small number. As a matter of fact, in 2015 we published a 10-year study, a retrospective of nearly 1,400 women. Interestingly, in this case we had 235 women with totally blocked fallopian tubes, either both tubes blocked or one removed and the other blocked, so we had half the chance to open tubes; we had a 61% success rate.

      The same success rate here: you can see the comparison of the therapy in blue versus surgery in green interesting sub-note is that the patients who had not undergone tubal surgery prior to our therapy had a 69% success rate for opening tubes; those who had undergone a prior surgery had a 35% success rate. So again, it’s the adhesions that form after surgery that are the problem. For physicians and patients, functionally, our success rates were quite a bit higher than the studies we could find for surgery, where our pregnancy rate was 57%.

      About double what the surgical success rates were for pregnancies after surgery. As an aside, we’ve seen success with other hormone-based conditions.

      We were surprised when FSH levels plummeted in many patients, and we saw that 39% became pregnant even though their FSH was 10 or above, indicating subfertile or infertile conditions when we treated women prior to their IVF transfer. 56% became pregnant with their next IVF, much higher than the national success rate.

      Interestingly, some of our highest successes were in women over 40 the success rates were close to three to five times the pregnancy rates of IVF without a pre-transfer therapy some women started calling us and saying, “Gosh I’m having some unusual side effects anybody ever reported that to you and what are you talking about he said well well it’s a little embarrassing but I’m having orgasms like I’ve never had before and my wife said to them is that okay yeah it’s great actually but it’s just so remarkable that I wanted to report it to you.”

      We started getting more and more reports like this, and we started talking, and we mentioned it to Dr King. He said, “That’s really important”. We said, “Yes, it is he said there’s nothing really in medicine that increases orgasm, and we can measure those responses what do you think we’re doing we said, “Well, we’re doing nothing but what we always do, and we’re treating adhesions, so sometimes they adhere to the cervix and it feels fibrous just to no stiff and we’ll be working on that.

      So the husbands are running into that, then they’re having pain with deep penetration; otherwise, on the vaginal walls, we’re working on the vaginal walls. Maybe those adhesions there are forming from bacterial infections, vaginal infections, or rough sex, or just adhesions there are masking the nerve, decreasing desire or lubrication, and orgasm. I know those particular domains because we could actually measure those domains of sexual function in our patients.

      We did publish a study in Medscape General Medicine, the largest medical journal in the world owned by WebMD, which is the one that George Lenberg edited after editing the JAMA for 17 years, that showed the increases in sexual function and decreases in intercourse pain were very high, and a decrease in improvements in the other domains of sexual function is shown here.

      Desire, arousal, orgasm, lubrication, and so forth, women started coming to us saying, “Gosh, you know I’ve been doubled over for two days every month with endometriosis pain since you treated me. My period came; I never even knew it was coming; it totally surprised me.”

      That was shocking to them, and we really didn’t know that much about endometriosis at the time. Of course, we were just treating adhesions. What could we be doing with these women? Well, we found that adhesions form wherever endometrial tissue lands on the body. It’s frequently and often that we find adhesions forming. We believe that what happens is that we’re not really treating the endometriosis.

      We’re just treating the adhesions that, as those tissues swell every month with a woman’s period, it’s pulling on those adhesions, creating a pull on the underlying structures, creating pain in the underlying structures, and as we break those adhesions or detach them.

      The decrease in pain is significant. The only other thing that these women could do is either go on birth control pills if they didn’t want to have a child, so the tissue wouldn’t swell, or have surgery.

      So this presented a nice alternative for people who did not want to have their IND endometrial implants burned off and didn’t want to undergo surgery. We published in the Journal of Endometriosis, and the founder of the Endometriosis Association joined our Board of Advisors. She was very impressed and started noticing that the study showed the improvements in endometriosis pain just from therapy alone lasted for over 12 months, which is as long as surgery has ever been shown to last.

      As far as function, again in our recently published study or 2015 study, success rates for pregnancy for women who were infertile due to endometriosis were about equal to surgery, so that’s from 299 women who have progressed, and meanwhile, my wife is by this time. She’s working full-time; she’s doing great; she has no pain; she’s gungho and really pretty fascinated.

      We started realizing that there was another problem for a lot of our patients, and that is people started calling us and saying I’m having bowel obstructions; I’m going back and back to the hospital for another and another surgery. I’m in the hospital with an NG tube in my nose and IVs in my arms. They’re cutting me open, and the worst part is I don’t know when I’m going to have to go back.

      Adhesions form in the bowel as they did with Belinda we saw in some of those early slides just as they form anywhere in the body they can form on the outer Loops of the bowel squeezing it like a garden hose they can form inside the bowel as they do in Fallopian tubes bowel adhesions can be massive and this is an image of some adhesions that you can see so you can see that it’s it can be a huge problem when structures like this form in delicate tissues that are supposed to be helping your food move through 21 ft of your small intestines down to your large intestine.

      What do physicians do when the bowels become obstructed? Well, the cost of bowel adhesiolysis surgery, that is, the surgery to decrease adhesions itself, is high.

      From 2010, the Department of Health and Human Services and the patients who just went in for adhesion surgery averaged a little over 8 days in the hospital, and about one out of eight of them were re-admitted to the hospital within 30 days, probably from some of these. Often, from some of these complications I mentioned earlier in the bowel, it can be really serious, as strictures of narrowing or total obstructions prevent food from going through the bowel- a life-threatening condition.

      The average cost to insurers and to the US population is over $100,000 a piece, and there were over 100,000 of them performed in 2010. The cost and quality of life are much higher.

      So here you have an ordinary American citizen who suddenly can’t take food in and feels nauseous. There’s a tremendous pain when nothing’s coming out. They go to the hospital. In the hospital, we do put an IV in them with some fluids or dilute something to help numb things and give them help to slow down.

      It will actually stop mobility together, but then, when we’re going to give them liquid and IV nutrition, put an NG tube through their nose and into their stomach to pump out the contents of their stomach so that we don’t build up pressure there, and now we’re just going to wait. And we’re going to see, Sir or Madam, if this clears well.

      What happens if it doesn’t clear well? If it doesn’t clear, we’re going to we generally will cut you. We always cut you open. We’ll pull out usually all 21 ft and examine that bowel. Wherever it’s bad, we will cut.

      What’s bad, we will throw it away, sew back what’s still okay, and put it back into you, and that’s what we’re looking at while you’re lying here. Okay, we can do a CAT scan to see if we can find out exactly where it is. Hopefully, we can do this laparoscopically, but it is a major surgery, so the average wait in the hospital is over 2 weeks. About one out of five is readmitted to the hospital within 30 days of their surgery due to some of the complications I talked about earlier.

      35% are readmitted, have another surgery, and within 10 years of their life, 2/3 of those are within the first year. This is from The Lancet, a highly respected Journal, as you all know, from 30,000 patients, and you see the data there just as I have extrapolated it.

      The huge problem in medicine is that brilliant surgeons want to help their patients, but in the end, after the surgery, they can look at their patients and say, “Here’s my card. The chances are reasonable that you’re going to be back.

      This is going to happen again for our patients. They tell us, “You know, it used to be that every day I’d look in the mirror and say What do I want to do today? What do I have to do now? I look at the mirror every morning, and I say, “Is this the day I’m going to die? Is this the day I’m going to be put into the hospital and maybe cut open? I’m afraid to go on a trip with my spouse. I’m afraid to go to my sister’s house. I don’t know what I can eat. I’m afraid something’s going to clog it up because I know I’ve been compromised, and I know that those adhesions are going to come back.” My doctor told me, “Well, they’re pretty likely to come back, and they do.”

      A big problem in medicine is an expensive problem, and one of the problems of huge human [Music] suffering surgery is the primary cause of bowel obstruction, so it’s brilliant, and it’s wonderful, and as dedicated as your surgeon is, he or she cannot prevent adhesions from forming, and the films that they’ve used, the tissues, and different things to prevent adhesions.

      None of them has skewed these numbers significantly at all. What are we looking at? Remember, we’re still looking at tiny little strands. Yeah, the surgeon may see ropes or curtains or balls of adhesions, but at its very core, these adhesions are made of tiny strands attached to each other with a small molecular bond.

      What a concept to be able to go in there and, like the run in the three-dimensional sweater, pull those apart so that those little attachments that are susceptible to a sustained stretch begin to dissolve. It’s like pulling out the run in a sweater and without surgery, without the risk of ostomy, without anesthesia, and for a fraction of the cost.

      What a neat concept. Once we realized we could open and clear blocked fallopian tubes, we started to look at adhesions in the bowel. This life-threatening condition we’ve been talking about was one of our early patients; actually, our first patient for bowel obstructions had undergone six bowel obstruction surgeries. She called us up; she said, “Yes, my last surgery was 12 weeks ago, and they’re scheduling my seventh surgery now.

      For those of you who are surgeons out there, you just know how serious and dramatic that surgery is. I’ve lost 18 pounds. I can only ingest liquids; it’s getting worse and worse. You’ve got to help me. They’re trying to help, but they’re killing me.

      She came in, and we treated her. We had by this time developed a 5-day program where patients start on Monday, and they’re done on Friday afternoon, four hours of therapy a day. By Wednesday afternoon, Wednesday evening, Belinda and I took her out to dinner. We had fish and some soft-cooked vegetables. She was able to cancel her surgery; she has started eating again. She can eat pretty much whatever she likes now, and it’s been nearly 8 years now, and she’s not had another surgery on her bowel since.

      Then we began doing more serious research before and after radiologic testing. In one case, we have a radiologic report showing obstruction before therapy, totally cleared of obstruction after therapy, and strictures, which are the tightening of the course of the bowel. In this case, the intestines before therapy and after therapy had no stricture at all, so we began to get excited about the science we were developing. We hired a woman with two PhDs. An expert in disease modeling, familiar with working at very small levels inside the body and at the chemical and molecular level, to help us determine what we were doing and to help us publish studies.

      Those radiologic reports are available in the Journal of Clinical Medicine, published in Healthcare. We created a validated study to look at quality of life differences because, for us as a physical therapy group, quality of life is very important. It’s not just “Do you have pain?” or “Do you not have pain?” “Can you eat?” or “You’re going to die.”

      Yeah, those are very important, but what’s your quality of life? Like, what can you actually do when you look in the mirror? Do you feel like I’ve got a life, or is my life basically over? I’ll never have my life back again.

      Using that, the validated scale was published. In healthcare, we created and published some of the first of our pilot cases, presented to 15,000 gastroenterologists at Digestive Disease Week in Washington, DC, in 2015. Published the pilot study in Gastroenterology as an investigation of treating bowel obstructions.

      Non-surgically, as part of that poster presentation, we found that we improved and had a really tight p-value of 025. We had significant improvements in pain, quality of life, and range of motion because, when you think about it, as you get adhered, it pulls you forward. For so many of these people, they’ve had their iliac valve cut out; you’re getting pulled forward. Right now, you can’t stand up; you can’t bend. You certainly can’t bend backward nearly as well, so we started measuring range of motion as a measure of how well we were doing, as well as pain.

      We did not do as well on diet and medication because we were a little bit skewed by the numbers. Only about half of the patients that we treated had restricted diets or were on medications, so although they showed significant improvements when we threw them in with the ones that had no problems beforehand and no problems afterward. It threw the P values off a bit. Looking a little bit deeper at the poster that we presented, the dark blue at the bottom represents normal, so you can see the changes from the diet pain.

      Gastrointestinal symptoms, quality of life, and medication from before on the left and after therapy on the right. For those of you who prefer numerical graphs, you can see a consistent return to normal in those areas, where the range of motion changes with P values that were pretty much off the chart as far as improvements in all ranges of motion.

      When I asked our PhD, “What do you think the mechanism is? What exactly are we doing here?” These are the areas that she suggested where we were showing improvements, as scientists and all clinicians who are conducting clinical research. Measure the side effects and adverse events.

      We did find that the adverse events, the major ones, are shown at the bottom, but they were transient. They were temporary, and they tended to go away within a few days. We do screen our patients for contraindications to therapy because we’re treating in an interstitial area, and we want to make sure that people do not have infections.

      Sometimes we’ll ask for blood for CDCs with CBCS with different SHS so that we can see if there’s a skewing of the neutrophils. Certainly, we don’t treat anyone who’s had surgery in an area that we’re going to treat within the last 30 or 90 days. We began creating a Home maintenance program because we saw that in the beginning, when we treated one woman, she was having the typical one. She was having bowel obstructions like clockwork every 3 weeks, and after we treated her, we thought she figured she was good to go.

      We opened her tubes before we cleared her bowel obstruction, and instead of having them every 3 weeks, she went 19 months, but then she had another obstruction, and we had two or three of these that showed us two things: one, we were making really dramatic improvements too. It wasn’t just that their guts and their intestines had been compromised, really for life, by their surgery.

      These people have bowel obstructions, so we’ve begun an educational program with each of our patients where we teach them about the structure of adhesions, how they form, how they deform, how they can deform themselves, how they can maintain, and perhaps even increase the results.

      When we get the need for repeat surgeries, it is a huge concern for patients. Having been handed this card, you’ll probably be back, or you may be back. We do know that within a short period of time, 30% of patients will return to the hospital for a repeat surgery; this is from the literature. Before we created our maintenance program, we had a 7% return to the hospital. Since we created and instituted this Home Maintenance program with all of our small bowel obstruction patients, our return to the hospital is 3%, not zero, but better than 30%.

      We’re now conducting a larger Phase 2 study on small bowel obstruction with 350 patients. We’ve also recently started working with Physicians who treat SIBO, which is small intestinal bacterial overgrowth. When the bacteria that normally reside in the large intestine migrate up into the small intestine, it can be inconvenient; those bacteria can actually start eating away at the nutrition. So, we’ve had patients who have lost a tremendous amount of weight, like 80 to 85 pounds, or who have had these bacteria actually eating on the inside of their intestines.

      When Physicians treat them with antibiotics, the antibiotics can really help decrease those bacteria. The problem is that if there are adhesions in the gut, those bacteria will come back, and they don’t escape. They can’t get out, so we started working with a lot of SIBO Physicians to coordinate care with their patients so the patients get antibiotic treatment, whether it’s natural antibiotics or pharmaceutical, and we treat, and they may be back and get a little bit more antibiotic treatment.

      We are the mechanics in the process; we help clear the adhesion so the intestinal bacteria that get blocked up in the intestines can escape, so that’s pretty much it. That’s where we are after 30 years of this investigation. The question in the beginning was, “Can adhesions be treated non-surgically?

      I’ll let you make your own determination; keep in mind that in all of these conditions, all we’ve been doing is treating adhesions. That’s what we know how to do, whether it’s blocked fallopian tubes, infertility, sexual dysfunction, chronic pain, adhesive pain, bowel obstruction, or small intestinal bacterial overgrowth. The common factor for us, and the one that we have used in all of our published data, is treating adhesions with our hands, so to that question to us apparently, the answer is yes.

    • Orgasms Increase Dramatically Using New Massage to the Reproductive Organs

      Orgasms Increase Dramatically Using New Massage to the Reproductive Organs

      Endorsed by gynecologists and shown to be effective in medical journals, the physical therapy decreases pain, increases desire, and increases lubrication

      GAINESVILLE, FL, January 27, 2014 – Nearly half of all women (43%) in the U.S. report sexual problems, including pain with sex, low libido, and decreased or absent orgasms, according to the Journal of the American Medical Association, but physicians are often stymied in providing a solution. Suffering in silence, most of these women experience pain or adverse effects on their relationships due to physical problems with intimacy. Many report infertility, as well.

      Once considered taboo, holistic remedies for treating sexual dysfunction are becoming more and more common as traditional medicine (prescription drugs and counseling) struggles to find a solution. According to research, a gynecologist and former Chief of Staff of North Florida Medical Center, Richard King, MD, said, “A new holistic therapy is showing remarkable success treating intercourse pain and other sexual problems. For many of these cases, doctors have no lasting medical solution.”

      Supported by peer-reviewed studies in gynecologic journals, “The Wurn Technique®”, developed at Clear Passage® Physical Therapy, is a unique hands-on therapy that helps women regain active sex lives. The holistic massage, unlike any other treatment available on the market today, has successfully treated thousands of women worldwide suffering from various sexual problems, including:

      • Intercourse pain
      • Low sex drive
      • Decreased or absent orgasms
      • Poor lubrication
      • Infertility

      “For several years, intercourse was extremely painful,” said Elizabeth, 38. “It felt like my husband was ripping through my tissues, then running into something very painful. I was ready to try anything to make the pain go away.” After one week of targeted massage therapy to her reproductive organs, Elizabeth reported a significant decrease in pain. She regained sensation in her pelvis and had an orgasm for the first time in years.

      National Director, Belinda Wurn, PT, adds, “The results after therapy are often dramatic for patients who suffered from longstanding pain. Published studies showed positive results in over 90% of women.”

      About Clear Passage® Physical Therapy® – Clear Passage® Physical Therapy is a network of physical therapy clinics specializing in the hands-on treatment of adhesions, female infertility, and chronic pain, with an additional focus on women’s health conditions such as endometriosis and pelvic and intercourse pain. Major medical journals and the public media have recognized Clear Passage® for its high success rates and ability to bypass the need for surgery and drugs. The group treats men and women from all over the world at several U.S. clinics.

      Larry Wurn, Founder of Clear Passage® Physical Therapy: Larry Wurn, Clinical Research Director, founded CPT with his wife, Belinda, a physical therapist with 38 years of experience. In 1987, Belinda developed chronic pain after surgery for cervical cancer. Searching for relief from the pain, the couple developed a therapy that has relieved pain for thousands of women. When they used it on women who were diagnosed as infertile, patients began having babies naturally.

    • Hide & Seek: The Female G-Spot

      Hide & Seek: The Female G-Spot

      The latest buzz in the world of sexual health is the potential discovery of the female G-spot. With many believing it to be a major trigger for enhancing female orgasm and others claiming it doesn’t exist, the elusive G-spot has been the subject of debate for years.

      The discovery was made by Dr. Adam Ostrzenski, a gynecologist in St. Petersburg, Fla. He describes the G-spot as a “bluish grape-like composition” with a distinct head, middle, and tail, along with a rope-like vessel emerging from the tail into the surrounding tissue. It is located in the dorsal perineal membrane of the front vaginal wall, says Dr. Ostrzenski.

      Not everyone is convinced that Dr. Ostrzenski is on the cusp of a groundbreaking discovery, arguing that he found it in only one woman, if at all. This will certainly be an interesting story to keep an eye on! Read more here.

    • You Don’t Have to Cope with Painful Intercourse While Trying to Conceive

      You Don’t Have to Cope with Painful Intercourse While Trying to Conceive

      Many women who experience intercourse pain believe the pain is something they just have to live with or tolerate. They manage the pain by having sex sparingly or avoiding sex at times when it might be particularly painful (such as during ovulation or the week before).

      However, if a woman is trying to conceive, she cannot avoid sex or only have sex when it feels best for her. Emily, a former Clear Passage® patient, struggled with just this problem. When she and her husband married, she was disappointed to find that sex was extremely painful. She told us that the pain “was almost unbearable.” Emily and her husband seldom had sex due to the pain, but when they decided to have children, she had to endure the pain. Emily told us, “We tried to have sex more often, and the stress of trying to push past the pain was making my menstrual cycles irregular.”

      Painful intercourse is not normal. In fact, pain with intercourse is a clue that there might be something else wrong. Clear Passage® has treated many women who experienced infertility, and a large majority of them experienced painful intercourse as well. We feel that painful intercourse is a sign that adhesions have formed in the reproductive tract, possibly adhering, restricting, and preventing proper function and fertility.

      When Emily came to us for help, Clear Passage® therapists delicately and sensitively treated adhesions in her reproductive tract. Emily stated, “I felt very comfortable at Clear Passage® and in control of the treatment. At times, it was uncomfortable because they were treating a very pain-sensitive area, but I could tell the difference as the pain decreased with each session.”

      Emily and her husband were eventually able to resume regular intercourse. Emily reported, “Before treatment, my husband had never been able to enter me fully, and finally he was able to!” Emily’s menstrual cycle also returned to a regular cycle, and she is currently expecting.

      Emily’s full story, along with stories by over 75 patients, will be featured in our upcoming book, Miracle Moms, Better Sex, Less Pain. To read more about the connection between painful intercourse and fertility, read our blog post: Infertility and Sexual Dysfunction are Linked – And It’s Not All in Your Head.

    • Causes of Decreased Sensation During Intercourse

      Causes of Decreased Sensation During Intercourse

      Sexual intimacy and intercourse should provide some of life’s greatest pleasures. But because the female urogenital and reproductive organs are very susceptible to adhesions, intercourse can become painful, dissatisfying, and embarrassing. Many women still believe the old misconception that “there isn’t anything that can be done,” or “it’s just the way it is,” or “my mother didn’t enjoy sexual intimacy and neither did hers, therefore I won’t be able to either.”

      If you are not satisfied with sexual intercourse, you are not alone. Did you know:

      • Approximately 50% of all US women and 43% of women aged 18-59 experience female sexual dysfunction (FSD), according to data from Urology and the Journal of the American Medical Association.
      •  In 2000, the Journal of Sex & Marital Therapy classified female sexual dysfunction into six measurable domains: desire, arousal, lubrication, orgasm, satisfaction, and pain. 
      • Intercourse pain affects between 46% and 60% of all US women, according to reports in American Family Physician (2001) and Obstetrics & Gynecology (1996). 

      Although sexual dysfunction and intercourse pain are prevalent among women, these conditions should not be considered “normal” or “untreatable.” A study published by the Journal of Sexual Medicine (2006)1 found that many female competitive bicyclists experienced decreased genital sensation. The researchers found that external genital nerves and arteries were negatively affected by being directly compressed in women who consistently cycled an average of at least 10 miles a week, four weeks per month. The results of their study can also be applied to other physical activities such as horseback riding.

      Other known causes of sexual dysfunction and intercourse pain include bladder infections, yeast infections, inflammatory disorders, sexually transmitted diseases, pelvic surgeries, physical or sexual abuse, etc. All of these conditions can cause adhesions to form within the reproductive tract. Adhesions can restrict and blanket the delicate structures of the reproductive system, causing decreased sensation (such as in bicyclists) or painful intercourse.

      So what can a woman do once she experiences sexual dysfunction or painful intercourse? First, she should speak with her doctor to make sure there is not a greater problem at hand, such as endometriosis or a sexually transmitted disease. The doctor can then ascertain if the vulva has been damaged in any way and determine the proper treatment.

      Our therapists have helped many women overcome pelvic pain and dysfunction. Request a free phone consultation with an expert therapist to learn more about our treatment.

      “Our results: sexual function and pain level improvements”

      • 93% of women in the natural fertility study reported decreased pain 2
      • 96% of sexual function study participants reported reduced sexual intercourse pain 3
      • 56% had improved or first-time orgasms 3
      • 65% had increased satisfaction 3
      • 70% had increased lubrication 3
      • 74% had increases in their arousal 3
      • 78% had greater or renewed desire (libido) 3
      • 91% had overall increased sexual function 3

      References

      1. Marsha K. Guess, Kathleen Connell, Steven Schrader, Susan Reutman, Andrea Wang, Julie LaCombe, Christine Toennis, Brian Lowe, Arnold Melman, Magdy Mikhail. “Genital Sensation and Sexual Function in Women Bicyclists and Runners: Are Your Feet Safer than Your Seat?” Journal of Sexual Medicine. Vol. 3, No. 6.
      2. Wurn BF, Wurn LJ, King CR, et al. Treating female infertility and improving IVF pregnancy rates with a manual physical therapy technique. Medscape General Medicine. 2004;6(2). Available (registration required) at http://www.medscape.com/viewarticle/480429.
      3. Wurn LJ, Wurn BF, King CR, et al. Increasing orgasm and decreasing dyspareunia with a manual physical therapy technique. Medscape General Medicine. 2004;6(4). Available (registration required) at http://www.medscape.com/viewarticle/493989.
    • Infertility and Sexual Dysfunction Are Linked – And It’s Not All in Your Head

      Infertility and Sexual Dysfunction Are Linked – And It’s Not All in Your Head

      Maintaining a sexually satisfying relationship can be difficult for couples struggling with infertility.  Judith C. Daniluk, author of an article entitled “Keeping Your Sex Life Alive While Coping with Infertility,” explains that “Infertility affects a person’s feelings about themselves – their masculinity or femininity, their self-worth, their self-esteem, their body.”

      Many women experience a deterioration of sexual satisfaction during infertility treatments, often related to feelings of disappointment, guilt, or low self-esteem. These feelings can decrease a woman’s sexual desire, arousal, ability to lubricate, and overall satisfaction.

      A study published in Fertility and Sterility (October 2007) found that women experience greater levels of anxiety and sexual stress due to infertility than men. For some women, infertility treatments directly decrease desire and arousal because of altered hormonal levels.

      Although these articles and studies show that decreased sexual satisfaction can be related to emotional and mental health, it is imperative that women know that sexual dysfunction or painful intercourse is not always “all in your head.”

      At CPT, we often find that female infertility and sexual dysfunction are physically linked. Frequently, a woman will experience a common event, such as a car accident, vaginal infection, STD, sexual abuse, or surgery, that causes adhesions to form within the reproductive tract. These adhesions can lead to infertility by restricting or pulling the fallopian tubes, ovaries, uterus, and vagina. Although some women may not initially experience any pain or sexual dysfunction at the time, the continued pulling and restriction can cause more adhesions to form, eventually resulting in painful intercourse and sexual dysfunction six to twelve months later. Because of the delayed onset, women often do not see the connection between their infertility and sexual dysfunction.

      CPT therapists see sexual dysfunction as a clue to discovering the cause of a woman’s infertility. We often ask patients, “When did your sexual dysfunction begin? How often does it occur? Are you experiencing trouble with arousal, desire, satisfaction, orgasm, pain, or lubrication? In what sexual positions does sex hurt? Where exactly does it hurt, and what does it feel like?”

      The answers to these questions shape our individualized treatment of each woman. Many women find that when we resolve the cause of their infertility, we also resolve the cause of their sexual dysfunction and pain.

      Learn more about our treatment for sexual dysfunction, painful intercourse, and female infertility.

      View our Related Research