Category: Infertility Issues

  • Spirituality Can Help Women with Premature Ovarian Failure

    Spirituality Can Help Women with Premature Ovarian Failure

    Premature Ovarian Failure (POF), when a woman’s ovaries stop working before the age of 40, can be a life-changing diagnosis for any woman. Former plans of children can suddenly be cut short, in addition to a woman dealing with symptoms of menopause. Many women find themselves re-examining their lives or battling depression.

    A study published by Fertility & Sterility (March 2007) examined the functional and spiritual well-being of women with POF (average age of 28). The study found a positive correlation between spiritual well-being and functional well-being. More specifically, they found that women who had higher levels of “meaning” or “inner peace” were more likely to function better in their lives. The study suggests that improving spiritual well-being may be an effective therapeutic approach to reducing “the emotional suffering that accompanies the life-altering diagnosis of POF.”

    If you have been diagnosed with POF, you may find it beneficial to take some time to examine your personal life. Even if you do not subscribe to any religion or spiritual belief, you can still benefit from examining what gives you “meaning” in life and what brings you peace. Have patience with yourself, as answers to spiritually deep questions are not always easily unearthed. You may find assistance by becoming more active in your church, reading a book designed to help you discover your inner self, speaking with a psychologist, or taking time to meditate each day.

    Learn more about treating female infertility and premature ovarian failure naturally.

  • The Three Types of Fallopian Tube Blockages

    The Three Types of Fallopian Tube Blockages

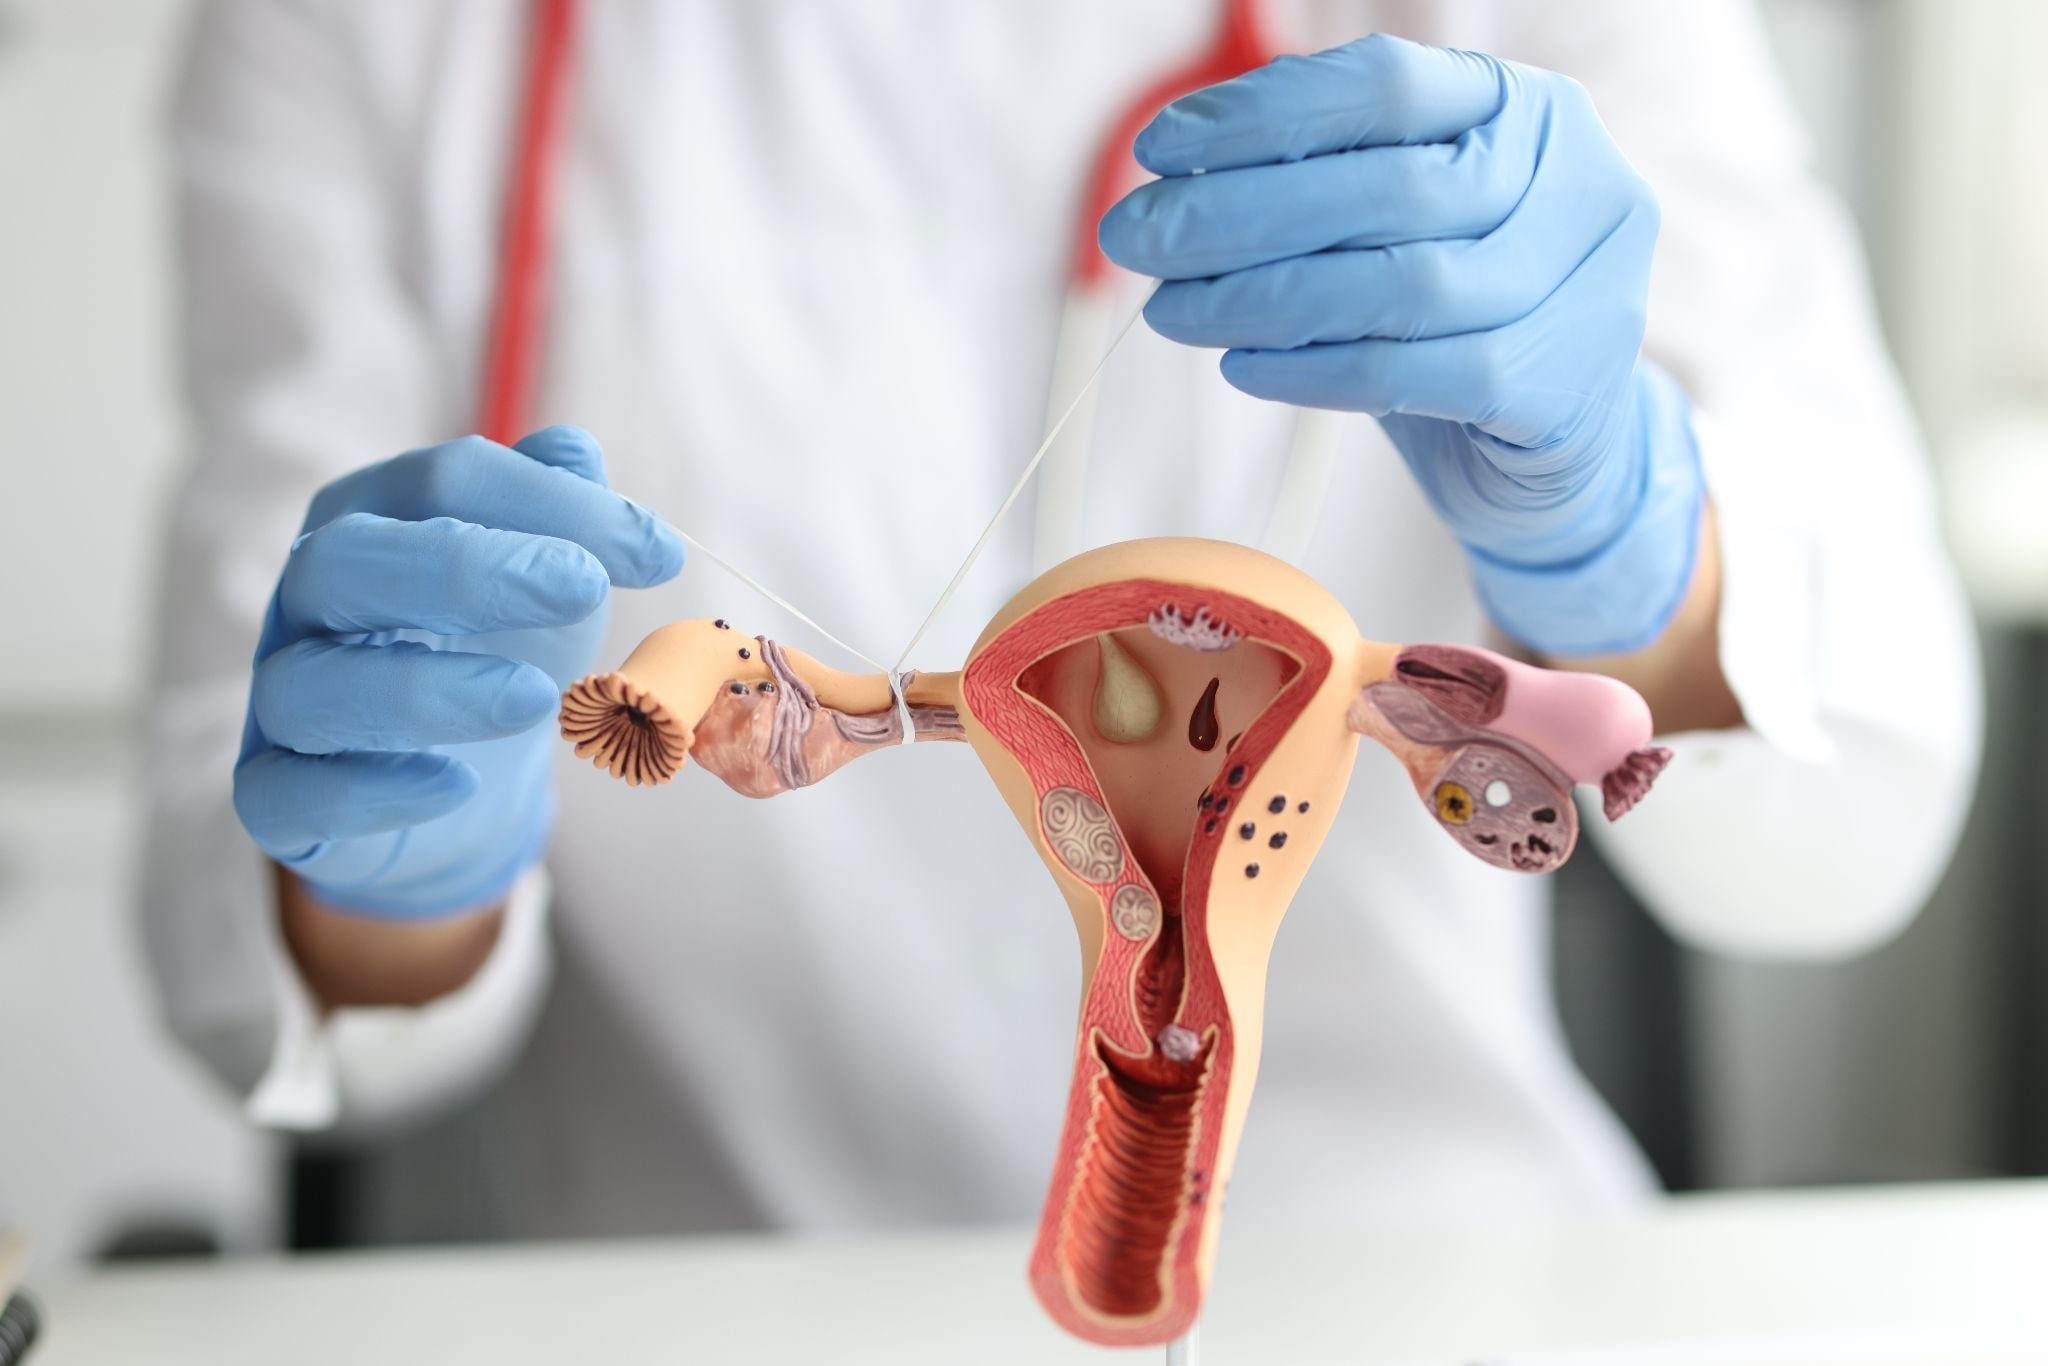
    When trying to make treatment choices for fallopian tube occlusion, it is crucial to understand the type of blockage. The success of treatment options varies greatly depending on the location of the blockage. Fallopian tubes can be blocked in three places:

    • Proximal: Near the uterus
    • Medial: In the middle of the tube
    • Distal: At the end of the tube, near the fimbria

    Fallopian tubes that are blocked proximally have the highest success rate for opening with conventional treatment. Doctors generally recommend a procedure in which a catheter is inserted through the uterus into the fallopian tube. Once there, a balloon can be used to try and open the tube. The success rate for proximally blocked fallopian tubes is high, granting women a window of time to become pregnant.

    If the blockage is located medially, it is harder for the doctor to access it. Doctors generally recommend laparoscopic surgery, in which adhesions are cauterized, and the tube is cut and then rejoined. Because it is a much more complicated procedure and scar tissue can easily grow and block the tube, success rates are lower for medially blocked fallopian tubes.

    Fallopian tubes that are blocked distally are the hardest to treat. Because the blockage is located near the delicate fimbria, a surgeon may not be able to remove adhesions without damaging the fimbria. Furthermore, the area is harder to access, and if adhesions re-grow, they can cover the ovary. Doctors generally do not recommend surgery for this type of blockage because of the success rates and instead offer IVF.

    Learn more about treating blocked fallopian tubes naturally.

    Unlock your fertility potential with Clear Passage® Physical Therapy’s Free Consult and Request Info – discover their groundbreaking, non-surgical approach that has successfully opened all three types of fallopian tube blockages, offering hope for natural conception without the risks of traditional surgery. To learn more, visit our Apply to Therapy page.

  • Overcoming the Fear of Another Ectopic Pregnancy

    Overcoming the Fear of Another Ectopic Pregnancy

    “In early 2004, I became pregnant for the first time,” Savannah told us. “But my husband and I were soon devastated when we learned it was an ectopic pregnancy.”

    Once a woman experiences an ectopic pregnancy, her perspective on pregnancy is forever changed. The excitement of a positive pregnancy test can be quickly transformed into fear.

    Doctors find that adhesions in or around the fallopian tubes can lead to ectopic pregnancies. After Savannah’s ectopic pregnancy, she underwent diagnostic laparoscopic surgery, and her doctor found adhesions around her ovaries and fallopian tubes.

    Her doctor removed what adhesions he could. Although Savannah trusted the hands of her doctor, she was still fearful that another ectopic pregnancy might occur.

    While a surgeon can remove many adhesions, she or he may be unable to access or cut areas that would impair fertility. Furthermore, adhesions frequently regrow as a direct result of the surgery.

    Savannah told us, “I wanted to do everything I could to reduce adhesions and avoid another ectopic pregnancy.” She found our clinic and underwent our 20-hour treatment program. The day she returned home, Savannah became pregnant. Her ultrasound later showed her pregnancy was progressing normally. Nine months later, she gave birth to a beautiful boy. Remarkably, she went on to have a second son.

    Women shouldn’t have to fear another ectopic pregnancy due to adhesions. Learn more about treatment for adhesions and the infertility page.

  • Ten Clues to Solving Secondary Infertility

    Ten Clues to Solving Secondary Infertility

    Women who experience secondary infertility are often baffled by their diagnosis. “I was able to easily conceive before,” many women tell us. “Why am I now having trouble?”

    When our therapists examine women with secondary infertility, they look for ten key changes:

    1. C-Section – Did the patient have a C-section? Adhesions and scar tissue after a C-section can cause blocked fallopian tubes or prevent proper implantation
    2. Episiotomy – Did the patient have an episiotomy? An episiotomy scar can cause adhesions that extend into the vagina and cervix, causing the cervix to become stiffened and preventing the passage of sperm
    3. Hormonal Changes – Has the patient had her hormone levels checked since giving birth? Has the patient’s period changed in heaviness or number of days? Pregnancy and aging can cause hormones to change, which may cause infertility
    4. Surgeries – Did the patient undergo any surgeries since pregnancy? Surgeries can cause adhesions to form and impair fertility
    5. Trauma – Has the patient experienced any car accidents, falls, abuse, or similar traumatic events? These events can cause long-lasting injuries, pelvic imbalances, adhesion formation, and other factors that can negatively impact fertility
    6. Infection – Has the patient had any bladder, vaginal, or yeast infections since pregnancy? Infections can cause adhesions to form in the delicate structures of the female pelvis. These adhesions can impair female fertility in multiple ways
    7. Inflammation – Has the patient been diagnosed with any new inflammatory conditions, such as endometriosis or PID? Inflammation directly causes adhesion formation, which can lead to infertility
    8. Pelvic or Back Pain – Has the patient experienced any hip, back, or pelvic pain since pregnancy? Pain is a sign that something is wrong. Pain in the pelvis may be linked to infertility, such as a hip injury that is located near the fallopian tubes.
    9. Sexual Dysfunction or Intercourse Pain – Has the patient experienced any sexual dysfunction or intercourse pain since pregnancy? Any problems with decreased desire, arousal, lubrication, orgasm, or satisfaction are signs that adhesions have formed in the delicate structures of the reproductive tract, possibly causing infertility
    10. Ovulation or Menstrual Pain – Has the patient experienced any new ovulation or menstrual pain since pregnancy? Ovulation pain is a sign that adhesions may be restricting and impairing the proper function of the ovary. New menstrual pain is a sign that adhesions may have formed around the uterus, preventing proper implantation.
  • Blocked Fallopian Tubes After Chlamydia

    Blocked Fallopian Tubes After Chlamydia

    Chlamydia, often known as the “silent” STD, can cause extensive scarring and adhesions within the female reproductive tract. Because Chlamydia produces relatively few noticeable symptoms, women are often unaware they have it until they struggle with infertility and undergo extensive diagnostic testing. Although doctors can cure Chlamydia with pharmaceuticals, the adhesions and scar tissue caused by the disease will remain in the body.

    The only option conventional medicine can offer women with adhesions is laparoscopic surgery. However, surgery to open blocked fallopian tubes is not always successful. Furthermore, laparoscopic surgery itself can cause more adhesions and scar tissue to form.

    Nicole, one of our former patients, struggled with just this problem. When Nicole and her husband couldn’t become pregnant after three years, they sought the help of a reproductive endocrinologist (RE). Her RE performed a series of tests. Nicole told us, “That was when I found out I had an undetected STD, Chlamydia. It had caused scar tissue to form around and block my fallopian tubes.”

    Her specialist recommended surgery to open the tubes or IVF. Nicole sought a second opinion with another RE who suspected she had fibroids in her uterus in addition to blocked tubes. He suggested she undergo a myomectomy to remove the fibroids, and he would also try to open her blocked fallopian tubes at the same time. He successfully removed the fibroids, but he couldn’t open her tubes.

    Nicole then tried three IVFs, all of which were unsuccessful or ended in miscarriage. Afterward, she heard about our clinic on an infertility chat site and decided to attend. After treatment, her HSG test showed her fallopian tubes were clear!

    However, Nicole’s doctor encouraged her to undergo IVF. Nicole, concerned about her biological clock, chose to undergo the procedure and told us, “At nine weeks, I discovered I had twins, but one passed away early in the pregnancy.” Nicole later gave birth to her baby girl, Joy.

    Everyone was later surprised when Nicole became unexpectedly pregnant after the birth of Joy. Nicole exclaimed, “We didn’t try anything, and we got pregnant!” Nicole’s tubes had indeed opened, and she later gave birth to a little boy.

    Learn more about natural treatment for blocked fallopian tubes. Nicole’s story, along with the stories of 75 former patients, will be showcased in our upcoming book, Miracle Moms, Better Sex, Less Pain.

  • Physical Therapists Open Blocked Fallopian Tubes Without Surgery

    Physical Therapists Open Blocked Fallopian Tubes Without Surgery

    New Orleans, LA, November 2, 2006/PRNewswire/ — Scientists at the Annual Meeting of the American Society for Reproductive Medicine (ASRM) reported that therapists were able to open totally blocked fallopian tubes using a new pelvic physical therapy that feels similar to a deep massage. Previously, surgery was the only treatment option for women with blocked fallopian tubes.

    The manual treatment (Wurn Technique®) opened blocked fallopian tubes in several women, some of whom conceived naturally after the therapy, according to the study abstract published in Fertility and Sterility (9/2006).

    The abstract examined eight women with totally blocked fallopian tubes. One patient had only one tube, and it was blocked, but she had a natural pregnancy and childbirth after receiving the therapy. Half of the women had at least one tube opened by the therapy; half of those became pregnant naturally and gave birth.

    The study cases were further complicated by a condition known as hydrosalpinx. Not only were the tubes blocked, but they were filled with a liquid that is considered toxic to embryos.

    “Hydrosalpinx is generally thought to render a fallopian tube useless and may decrease the chance for successful in vitro fertilization (IVF),” said co-author Mark Kan, MD, a reproductive endocrinologist at the Newport Fertility Center in Newport Beach, CA. “The therapy opened several affected tubes, and apparently returned function to some of them.”

    “While this study was small, the results are clear,” said physical therapist Belinda Wurn, who developed the technique with her husband, massage therapist Larry Wurn. “A diagnostic test clearly shows whether either tube has opened. The full-term pregnancies indicate a return of function.”

    Research gynecologist and former Chief of Staff at North Florida Regional Medical Center, Richard King, MD, called the results remarkable. “The therapy is a natural adjunct to gynecologic care,” King says.

    The therapists began developing the technique in 1987 to treat author Belinda Wurn’s pelvic pain after cancer and surgery. It is now used to treat female infertility, endometriosis pain, and female sexual dysfunction (including painful intercourse). The therapy is available at Clear Passage® Therapies® clinics throughout the United States.

  • Three Friends Overcome Years of Infertility With ‘Massage’ When Recently Investigated Hands-On Therapy Succeeds After Medical Science Fails

    Three Friends Overcome Years of Infertility With ‘Massage’ When Recently Investigated Hands-On Therapy Succeeds After Medical Science Fails

    GAINESVILLE, Fla., Sept. 27, 2004 /PRNewswire/ — Struggling with years of infertility can be stressful and heartbreaking. But the battle is over for three friends who credit their success to a new “infertility massage.”

    Alexandra, Angie, and Cathleen all attribute their children to a patent-protected massage therapy called the Wurn Technique®(R). The therapy, which uses no drugs or surgery, appears to decrease adhesions and scar tissue that cause half of all female infertility, according to physical therapist Belinda Wurn, co-developer.

    “We use our hands to find adhered areas in and around a woman’s reproductive organs,” said Belinda Wurn. “We apply a sophisticated ‘infertility massage‘ to free the reproductive tissues from adhesions that prevent proper function and cause infertility.”

    The therapy’s effectiveness was recently chronicled in Medscape General Medicine, Ob/Gyn & Women’s Health. The peer-reviewed journal reported that 71% of infertile women conceived within one year after the treatments without any further medical or surgical intervention. A second study followed women who received in vitro fertilization (IVF) transfer after therapy. Two-thirds (67%) of the transfers resulted in pregnancy, beating the 41% national average reported by the CDC. But for the three friends, pregnancy came without surgical intervention.

    Alexandra was the first of the three friends to discover the therapy’s success. With one blocked fallopian tube and the other tube scarred and adhered from a C-section, her physician told her it was unlikely she would ever conceive again. Yet, she has had two children since therapy and is now pregnant again. “I recommended the therapy to my friend Angie, who had been struggling with infertility for so long,” Alexandra said.

    Angie was infertile for five years, with a history of endometriosis, miscarriages, and seven failed intrauterine inseminations (IUI). But after receiving the new therapy, Angie also conceived naturally and gave birth to a beautiful baby girl. “I know that the therapy is what my body needed to be successful,” Angie said. She called her friend, Cathleen.

    Cathleen was given a 5% chance of ever becoming pregnant, even with IVF. Her tubes were scarred, and her fimbriae were clubbed with adhesions. After five years of infertility and four IVF attempts, she was crushed. She had never had a single pregnancy. “Angie bugged me to try the therapy, so I finally went. A few months after therapy, to my utter amazement, I was pregnant,” Cathleen said. Cathleen also gave birth to a little girl.

    “We are very excited about the results we are seeing with our therapy. At least 60 babies have already been born or are presently expected by women who were diagnosed as infertile,” said massage therapist Larry Wurn, co-developer of the Wurn Technique® and Director of Clinical Studies at Clear Passage® Therapies.