Category: Women’s Health

  • Overcoming Intercourse Pain: Reclaiming Desire and Orgasm

    Overcoming Intercourse Pain: Reclaiming Desire and Orgasm

    TRANSCRIPT: Overcoming Intercourse Pain: Reclaiming  Desire and Orgasm

    This is what sex is supposed to feel like. This r­­ocks.  We can do this again. I had an orgasm for the first time in years. That sounds weird, probably for some people, but for people who have dealt with chronic pelvic pain, not having orgasms goes along with it. To know that it came back and to feel that — that was pretty awesome. Hi,  I am a physical therapist. I came to Clear Passage® to receive treatment for my own pain. As a physical therapist, I know it is hard for other people to believe that we therapists have pain as well and deal with pain issues ourselves. So, for many years, I went on experiencing discomfort, pain, and a lack of desire, and my libido went down.

    I felt really guilty for not wanting to have intimacy with my husband, and that continued to grow as I did not have anybody to speak to about this condition. It’s something so private; women who are dealing with pelvic pain and pain with intercourse don’t have anybody to talk to. It was hard. It was really painful. It felt like ripping through tissue. It felt like your muscles just bound down. It feels like a hot poker, a jolting pain with movement and thrusting that I know is not normal. It would cause my whole body to tense up. I would not be able to breathe.  I couldn’t relax. It was just not pleasant.  It was emotionally stressful, as well as physically stressful, because you want to be intimate, and you want to be present, but the pain is really blocking it.  So, you are just not into it. You’re not into sex. There is an embarrassing factor in talking about painful intercourse. What is portrayed in the media is that it is wonderfully orgasmic every time you have sex, and that is not reality. The reality is that sex is not always like that, and it is definitely not like that for women who have pain with intercourse.

    My doctor thought, “OK, you have pain with intercourse, so let’s do an ultrasound to make sure there is nothing wrong with you. Let’s do some sonograms and let’s test you. Nope, everything is normal.” So they look at me like it’s in my head. Why would you have pain with intercourse if all your tests come back normal, and you look healthy and feel fine? So where do I go from here? In the middle of treatment, my husband came to visit so he could assess my progress and how I felt with intercourse.

    This was only two days after treatment. First of all, I had a desire to want to be with my spouse. The desire had really subsided and decreased over the years. When you think of how painful sex is, your body shuts down, and your desire goes away.  So just the fact that the desire to want to be with my spouse was there, and physically I had more sensation.  I had a lot more sensation in my pelvic area. I was able to respond to touch stimuli.  Just what naturally happens during intercourse. You get excited. I was able to feel that excitement again, and the urge to want to be intimate was huge. I had a lot more room in my pelvic floor,  even during the actual thrusting motion.  Before, it was like a jackknife every time my husband would thrust; I would hold my breath and tense up.  It wasn’t him, and instantly it would also affect my spouse, and he would hold back and say, “Oh no, I am hurting you.”

    This time around, it was just like “Holy cow! This is what sex is supposed to feel like. This r­­ocks! We can do this again.” I had an orgasm for the first time in years. That sounds weird, probably for some people, but for people who have dealt with chronic pelvic pain, not having orgasms goes along with it. To know that that came back and to feel that, that was pretty awesome.
  • Hide & Seek: The Female G-Spot

    Hide & Seek: The Female G-Spot

    The latest buzz in the world of sexual health is the potential discovery of the female G-spot. With many believing it to be a major trigger for enhancing female orgasm and others claiming it doesn’t exist, the elusive G-spot has been the subject of debate for years.

    The discovery was made by Dr. Adam Ostrzenski, a gynecologist in St. Petersburg, Fla. He describes the G-spot as a “bluish grape-like composition” with a distinct head, middle, and tail, along with a rope-like vessel emerging from the tail into the surrounding tissue. It is located in the dorsal perineal membrane of the front vaginal wall, says Dr. Ostrzenski.

    Not everyone is convinced that Dr. Ostrzenski is on the cusp of a groundbreaking discovery, arguing that he found it in only one woman, if at all. This will certainly be an interesting story to keep an eye on! Read more here.

  • The Role of the Cervix in Menstrual Pain

    The Role of the Cervix in Menstrual Pain

    Discover relief from menstrual pain with Clear Passage® Physical Therapy’s Free Consult and Request Info – learn how their unique, non-surgical approach can address cervical issues, adhesions, and alignment problems that may be causing your discomfort, potentially transforming your menstrual experience without invasive procedures. To learn more, visit our Apply to Therapy page.

    When women think of menstrual cramps, they normally think of the constant ache or throbbing pain in the pelvis. We seldom think of stenosis of the cervix, also known as a stenotic cervix, but it is a key player in dysmenorrhea. Dysmenorrhea is the medical term for abdominal cramps and pain experienced during menstruation. The main symptoms of dysmenorrhea are pain in the abdominal and pelvic region, sometimes accompanied by digestive issues or headaches.

    During menstruation, the lining of the uterus detaches and exits the body through the cervix. The cervix is the opening to the uterus. In its natural, midline position, it opens slightly, allowing menstrual blood to pass into the vagina.

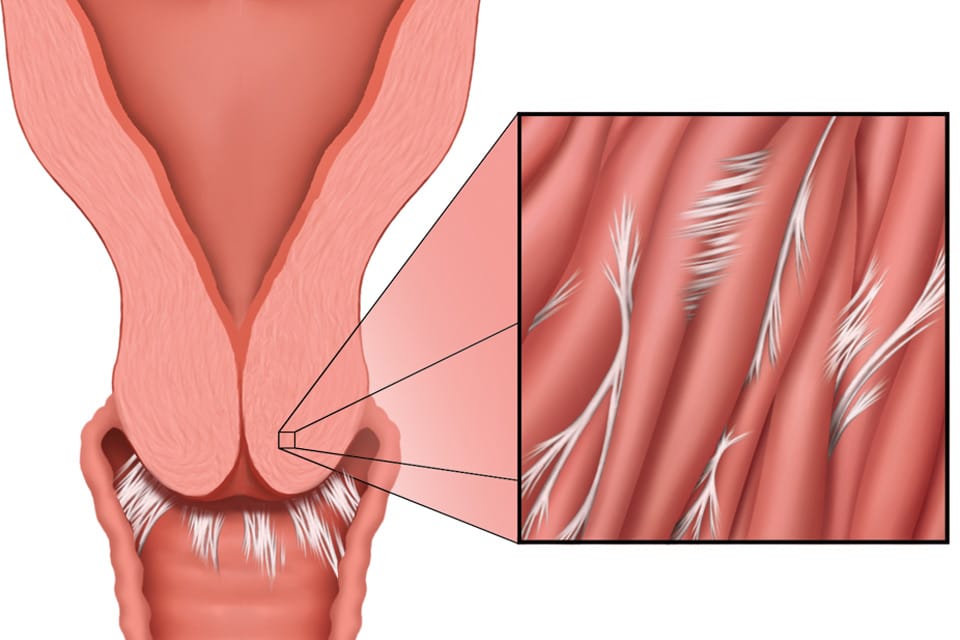
    But if the cervix has been damaged or adhesions have formed on or near the cervix, the cervix can cause a great deal of pain during menstruation. If the cervix is pulled or pushed forward, backward, or to one side, it can make the passage of menstrual blood difficult and painful. If adhesions have formed on or near the cervix, the opening of the cervix can be constricted. When blood tries to pass through the constricted opening, it can elicit a great amount of pain.

    Because the cervix is protected inside the vagina, many women are not aware of how easily the cervix can be damaged. Sexual intercourse or sexual abuse can physically push the cervix out of alignment. Sexually transmitted diseases can create inflammation that leads to adhesion formation. STDs can also inflame the cervix, making the passage of menstrual blood painful. Radiation therapy causes the same process of adhesion formation and can leave the entire pelvis adhered. Even vaginal or yeast infections can lead to adhesion formation that constricts the cervix or pulls it out of alignment.

    Adhesions on the cervix can lead to more than just period pain. Dyspareunia, also known as intercourse pain, is commonly caused by adhesions forming within a woman’s reproductive system. Many women who have adhesions in their reproductive tract or have cervixes that are out of alignment also experience pain during sexual intercourse. The same adhesions that constrict the cervix can also constrict the vaginal walls, leading to pain when stretched.

    Unfortunately, this condition often goes untreated because of the personal, sensitive nature of the topic — and reluctance to discuss it with a doctor. If you experience pain during or after intercourse, we encourage you to learn more about this condition that affects millions of women.

    To read more about the role of the cervix in intercourse pain, read Three Common Causes of Deep Penetration Pain.

    Conventional treatment for adhesions involves laparoscopic surgery to lyse (burn) any adhesions. However, few women are willing to undergo surgery in a very delicate, personal area when their chief complaint is menstrual pain.

    Clear Passage® offers a unique and effective alternative that directly treats adhesions and the cervix. Using manual physical therapy techniques, our therapists deform and detach adhesions. They also gently enable the cervix to move back to its natural position. Following treatment, many women report that their menstrual pain is significantly decreased or gone. Many women who previously experienced pain with intercourse also report that sex is no longer painful. To learn more about our treatment for menstrual cramps or how we can decrease painful intercourse, see our menstrual pain page or dyspareunia page.


  • You Don’t Have to Cope with Painful Intercourse While Trying to Conceive

    You Don’t Have to Cope with Painful Intercourse While Trying to Conceive

    Many women who experience intercourse pain believe the pain is something they just have to live with or tolerate. They manage the pain by having sex sparingly or avoiding sex at times when it might be particularly painful (such as during ovulation or the week before).

    However, if a woman is trying to conceive, she cannot avoid sex or only have sex when it feels best for her. Emily, a former Clear Passage® patient, struggled with just this problem. When she and her husband married, she was disappointed to find that sex was extremely painful. She told us that the pain “was almost unbearable.” Emily and her husband seldom had sex due to the pain, but when they decided to have children, she had to endure the pain. Emily told us, “We tried to have sex more often, and the stress of trying to push past the pain was making my menstrual cycles irregular.”

    Painful intercourse is not normal. In fact, pain with intercourse is a clue that there might be something else wrong. Clear Passage® has treated many women who experienced infertility, and a large majority of them experienced painful intercourse as well. We feel that painful intercourse is a sign that adhesions have formed in the reproductive tract, possibly adhering, restricting, and preventing proper function and fertility.

    When Emily came to us for help, Clear Passage® therapists delicately and sensitively treated adhesions in her reproductive tract. Emily stated, “I felt very comfortable at Clear Passage® and in control of the treatment. At times, it was uncomfortable because they were treating a very pain-sensitive area, but I could tell the difference as the pain decreased with each session.”

    Emily and her husband were eventually able to resume regular intercourse. Emily reported, “Before treatment, my husband had never been able to enter me fully, and finally he was able to!” Emily’s menstrual cycle also returned to a regular cycle, and she is currently expecting.

    Emily’s full story, along with stories by over 75 patients, will be featured in our upcoming book, Miracle Moms, Better Sex, Less Pain. To read more about the connection between painful intercourse and fertility, read our blog post: Infertility and Sexual Dysfunction are Linked – And It’s Not All in Your Head.

  • Causes of Decreased Sensation During Intercourse

    Causes of Decreased Sensation During Intercourse

    Sexual intimacy and intercourse should provide some of life’s greatest pleasures. But because the female urogenital and reproductive organs are very susceptible to adhesions, intercourse can become painful, dissatisfying, and embarrassing. Many women still believe the old misconception that “there isn’t anything that can be done,” or “it’s just the way it is,” or “my mother didn’t enjoy sexual intimacy and neither did hers, therefore I won’t be able to either.”

    If you are not satisfied with sexual intercourse, you are not alone. Did you know:

    • Approximately 50% of all US women and 43% of women aged 18-59 experience female sexual dysfunction (FSD), according to data from Urology and the Journal of the American Medical Association.
    •  In 2000, the Journal of Sex & Marital Therapy classified female sexual dysfunction into six measurable domains: desire, arousal, lubrication, orgasm, satisfaction, and pain. 
    • Intercourse pain affects between 46% and 60% of all US women, according to reports in American Family Physician (2001) and Obstetrics & Gynecology (1996). 

    Although sexual dysfunction and intercourse pain are prevalent among women, these conditions should not be considered “normal” or “untreatable.” A study published by the Journal of Sexual Medicine (2006)1 found that many female competitive bicyclists experienced decreased genital sensation. The researchers found that external genital nerves and arteries were negatively affected by being directly compressed in women who consistently cycled an average of at least 10 miles a week, four weeks per month. The results of their study can also be applied to other physical activities such as horseback riding.

    Other known causes of sexual dysfunction and intercourse pain include bladder infections, yeast infections, inflammatory disorders, sexually transmitted diseases, pelvic surgeries, physical or sexual abuse, etc. All of these conditions can cause adhesions to form within the reproductive tract. Adhesions can restrict and blanket the delicate structures of the reproductive system, causing decreased sensation (such as in bicyclists) or painful intercourse.

    So what can a woman do once she experiences sexual dysfunction or painful intercourse? First, she should speak with her doctor to make sure there is not a greater problem at hand, such as endometriosis or a sexually transmitted disease. The doctor can then ascertain if the vulva has been damaged in any way and determine the proper treatment.

    Our therapists have helped many women overcome pelvic pain and dysfunction. Request a free phone consultation with an expert therapist to learn more about our treatment.

    “Our results: sexual function and pain level improvements”

    • 93% of women in the natural fertility study reported decreased pain 2
    • 96% of sexual function study participants reported reduced sexual intercourse pain 3
    • 56% had improved or first-time orgasms 3
    • 65% had increased satisfaction 3
    • 70% had increased lubrication 3
    • 74% had increases in their arousal 3
    • 78% had greater or renewed desire (libido) 3
    • 91% had overall increased sexual function 3

    References

    1. Marsha K. Guess, Kathleen Connell, Steven Schrader, Susan Reutman, Andrea Wang, Julie LaCombe, Christine Toennis, Brian Lowe, Arnold Melman, Magdy Mikhail. “Genital Sensation and Sexual Function in Women Bicyclists and Runners: Are Your Feet Safer than Your Seat?” Journal of Sexual Medicine. Vol. 3, No. 6.
    2. Wurn BF, Wurn LJ, King CR, et al. Treating female infertility and improving IVF pregnancy rates with a manual physical therapy technique. Medscape General Medicine. 2004;6(2). Available (registration required) at http://www.medscape.com/viewarticle/480429.
    3. Wurn LJ, Wurn BF, King CR, et al. Increasing orgasm and decreasing dyspareunia with a manual physical therapy technique. Medscape General Medicine. 2004;6(4). Available (registration required) at http://www.medscape.com/viewarticle/493989.
  • Ask the Experts

    Ask the Experts

    Belinda and Larry Wurn are experts in manual therapy for chronic pain and dysfunction, such as endometriosis, intercourse pain, adhesion-related disorders, and female infertility. Together, they have more than 50 years of clinical experience treating a wide variety of complex conditions. Studies have been published about their work in some of the most prestigious medical journals in the US.

    The Wurns are pleased to share their decades of knowledge by answering individual questions on this Facebook page. If you have a question you would like answered by either of them, you may post it there.

  • Infertility and Sexual Dysfunction Are Linked – And It’s Not All in Your Head

    Infertility and Sexual Dysfunction Are Linked – And It’s Not All in Your Head

    Maintaining a sexually satisfying relationship can be difficult for couples struggling with infertility.  Judith C. Daniluk, author of an article entitled “Keeping Your Sex Life Alive While Coping with Infertility,” explains that “Infertility affects a person’s feelings about themselves – their masculinity or femininity, their self-worth, their self-esteem, their body.”

    Many women experience a deterioration of sexual satisfaction during infertility treatments, often related to feelings of disappointment, guilt, or low self-esteem. These feelings can decrease a woman’s sexual desire, arousal, ability to lubricate, and overall satisfaction.

    A study published in Fertility and Sterility (October 2007) found that women experience greater levels of anxiety and sexual stress due to infertility than men. For some women, infertility treatments directly decrease desire and arousal because of altered hormonal levels.

    Although these articles and studies show that decreased sexual satisfaction can be related to emotional and mental health, it is imperative that women know that sexual dysfunction or painful intercourse is not always “all in your head.”

    At CPT, we often find that female infertility and sexual dysfunction are physically linked. Frequently, a woman will experience a common event, such as a car accident, vaginal infection, STD, sexual abuse, or surgery, that causes adhesions to form within the reproductive tract. These adhesions can lead to infertility by restricting or pulling the fallopian tubes, ovaries, uterus, and vagina. Although some women may not initially experience any pain or sexual dysfunction at the time, the continued pulling and restriction can cause more adhesions to form, eventually resulting in painful intercourse and sexual dysfunction six to twelve months later. Because of the delayed onset, women often do not see the connection between their infertility and sexual dysfunction.

    CPT therapists see sexual dysfunction as a clue to discovering the cause of a woman’s infertility. We often ask patients, “When did your sexual dysfunction begin? How often does it occur? Are you experiencing trouble with arousal, desire, satisfaction, orgasm, pain, or lubrication? In what sexual positions does sex hurt? Where exactly does it hurt, and what does it feel like?”

    The answers to these questions shape our individualized treatment of each woman. Many women find that when we resolve the cause of their infertility, we also resolve the cause of their sexual dysfunction and pain.

    Learn more about our treatment for sexual dysfunction, painful intercourse, and female infertility.

    View our Related Research

  • Spirituality Can Help Women with Premature Ovarian Failure

    Spirituality Can Help Women with Premature Ovarian Failure

    Premature Ovarian Failure (POF), when a woman’s ovaries stop working before the age of 40, can be a life-changing diagnosis for any woman. Former plans of children can suddenly be cut short, in addition to a woman dealing with symptoms of menopause. Many women find themselves re-examining their lives or battling depression.

    A study published by Fertility & Sterility (March 2007) examined the functional and spiritual well-being of women with POF (average age of 28). The study found a positive correlation between spiritual well-being and functional well-being. More specifically, they found that women who had higher levels of “meaning” or “inner peace” were more likely to function better in their lives. The study suggests that improving spiritual well-being may be an effective therapeutic approach to reducing “the emotional suffering that accompanies the life-altering diagnosis of POF.”

    If you have been diagnosed with POF, you may find it beneficial to take some time to examine your personal life. Even if you do not subscribe to any religion or spiritual belief, you can still benefit from examining what gives you “meaning” in life and what brings you peace. Have patience with yourself, as answers to spiritually deep questions are not always easily unearthed. You may find assistance by becoming more active in your church, reading a book designed to help you discover your inner self, speaking with a psychologist, or taking time to meditate each day.

    Learn more about treating female infertility and premature ovarian failure naturally.

  • The G-Spot and Sexual Function

    The G-Spot and Sexual Function

    Unlock the potential for improved sexual function and satisfaction with Clear Passage® Physical Therapy’s Free Consult and Request Info – discover how their unique, non-invasive approach has helped women experience increased desire, arousal, and orgasm while reducing pain by up to 96%. To learn more, visit our Apply to Therapy page.

    Female sexual function relies on adequate levels of desire, arousal, lubrication, orgasm, and satisfaction. So why do so many women experience trouble in these areas? We believe the G-spot is key to unraveling this puzzle.

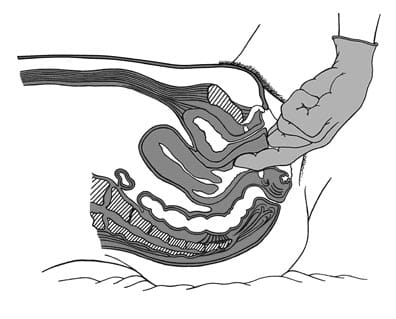
    The G-Spot is located just two inches inside the vagina. To find it, place one finger inside the vagina as far as it will go, and then curl your finger up towards your belly button. When you feel this area, do you notice any textures? Is the tissue smooth and mobile, or are there bumps or something that feels like corduroy, a stocking, or a hairnet? If the tissue is anything but smooth, it is a sign that adhesions have formed in this area.

    When adhesions form over the G-spot, they can desensitize it or pull the delicate tissues of the vagina. This can lead to decreased lubrication, orgasm, and satisfaction. When a woman is not satisfied with her sexual experience or experiences difficulty lubricating, it can later be difficult to desire sex or become aroused.

    At CPT, we treat sexual dysfunction and pain by addressing adhesions that form in and around the reproductive tract. Our study, published in Medscape General Medicine, found that after treatment, women experienced increased desire (78%), increased arousal (74%), increased lubrication (70%), increased satisfaction (65%), increased orgasm (56%), and decreased pain (96%).

    To learn more about our treatment for sexual dysfunction and intercourse pain, please visit our site.

  • Three Common Causes of Deep Penetration Pain

    Three Common Causes of Deep Penetration Pain

    Few women feel comfortable discussing painful intercourse, much less deep penetration pain. However, many women experience pain that lasts after initial entry. Some women report that “It feels like my partner is hitting something.” Other women experience a broader ache in their pelvis.

    So what can cause this type of pain? Below are three common culprits:

    Tailbone: A fall onto the tailbone can cause it to be pushed forward or to the side. If the ligaments and tissues attached to the tailbone are also injured, the tailbone can heal in this position. Women with this condition experience painful intercourse, pain with bowel movements, and difficulty sitting for long periods.

    Cervix: The cervix is held in its midline position by ligaments that attach to the tailbone. If infection, inflammation, surgery, or trauma occurs in the vagina, adhesions can form and pull the cervix out of alignment. Adhesions can also tighten the cervix, causing a cervical stricture, which can cause significant pain when impacted by deep penetration.

    IUD: An IUD is designed to prevent pregnancy by causing inflammation in the uterus. If the uterus is inflamed, a woman may experience pain during intercourse. Inflammation also causes adhesions to form in the uterus and cervix. Even if the IUD has been removed, a woman can still experience pain during intercourse due to these adhesions.

    Our therapists, trained to reduce adhesions, have had great success treating intercourse pain. In our latest study, 96% of patients experienced a decrease in intercourse pain.

    The symptoms of stenosis of the cervix may include painful periods, difficulty inserting tampons, and challenges with fertility.

    Learn more about our treatment for stenosis, sexual dysfunction, and painful intercourse.