A primary author of several studies on Clear Passage®
Board of Advisors member
With a doctorate in Medical Sciences, two postdoctoral appointments, and over a decade of work as a researcher and instructor at the University of Florida College of Medicine, Dr. Rice is the consummate clinical researcher. Her wide range of expertise includes examining the latest studies in the field of effective therapies, creating science-based analyses of our work, gathering and collating patient data, and applying bio-statistical analysis to her findings.
Over the last 15 years, Dr. Rice has become increasingly fascinated with the body’s self-healing mechanisms and with non-surgical and alternative methods of healing. She felt that many natural and less invasive techniques could be as effective as common medical procedures, without the associated risks or costs. With her strong scientific background and her interest in less invasive techniques of healing, she is perfectly suited to design and conduct research on Clear Passage®’s unique manual therapy, the Wurn Technique®®.
“It’s a perfect setting for me,” she says. “As an on-site scientist, I get to meet the patients, build data sets with the therapists, and analyze data in order to evaluate the treatment for different medical conditions, many of which are not addressed effectively by mainstream medicine. This is a scientist’s dream position — to be at the forefront of a cutting-edge therapy while witnessing the improvements for the patients and the end of their suffering.”
Publications:
Rice, A.D., Patterson, K., Reed, E.D., Wurn, B.F., Klingenberg, B., King III, C.R., & Wurn, L.W. (2016). Treating small bowel obstruction with manual physical therapy: A prospective efficacy study. BioMed Research International, 2016: 7610387. doi: 10.1155/2016/7610387
King, C. R.; Rice, A. D. (2015) “Alternative Treatment of Non-Malignant Bowel Obstruction in Patients with Gynecological Cancer.” In Intussusception and Bowel Obstruction: Symptoms, Diagnosis and Treatment Options; ed Rosie Miller. NOVA Scientific Publishing: Hauppauge, NY, 125–140.
Rice, A. D.; King, C. R. (2015) “Decreasing Post-Surgical Adhesions That Cause Recurrent Small Bowel Obstructions with a Conservative Manual Physical Therapy”. In Intussusception and Bowel Obstruction: Symptoms, Diagnosis and Treatment Options; ed Rosie Miller. NOVA Scientific Publishing: Hauppauge, NY, 113–124.
Yuan D, Zhu Z, Tan X, Liang J, Zeng C, Zhang J, Chen J, Ma L, Dogan A, Brockmann G, Goldmann G, Medina E, Rice AD, Moyer RW, Man X, Yi K, Li Y, Lu Q, Huang Y and Huang S. (2014) Scoring the collective effects of SNPs: association of minor alleles with complex traits in model organisms. Science China Life Sciences, in press.
Rice AD, Adams MA, Lindsey SF, Swetnam DM, Manning BR, Smith AJ, Burrage AM, Wallace G, MacNeil AL, and Moyer RW. (2014) Protective Properties of Vaccinia-Based Vaccines: Skin scarification promotes a nonspecific immune response that protects against orthopox disease. Journal of Virology, 88(14):7753-63.
Rice AD, Wakefield LB, Patterson K, Reed ED, Wurn BF, Klingenberg B, King CR, and Wurn LJ. (2014) Development and validation of a questionnaire to measure serious and common quality of life issues for patients experiencing small bowel obstructions. Healthcare, 2(1): 139-149.
Rice AD, Wakefield LB, Patterson K, Reed ED, Wurn BF, King CR, and Wurn LJ. (2014) Decreasing Adhesions and Avoiding Further Surgery in a Pediatric Patient Involved in a Severe Pedestrian versus Motor Vehicle Accident. Pediatric Reports, 6:5126.
Amanda D. Rice, Evette D’Avy Reed, Kimberley Patterson, Belinda F. Wurn, and Lawrence J. Wurn. (2013) Manual Physical Therapy for Non-Surgical Treatment of Small Bowel Obstruction. Journal of Clinical Medicine.
Amanda D. Rice, Evette D’Avy Reed, Kimberley Patterson, Belinda F. Wur,n and Lawrence J. Wurn. (2012) Clearing Bowel Obstruction and Decreasing Pain in a Terminally Ill Patient via Manual Physical Therapy. Journal of Palliative Medicine, in press.
Dejian Yuan, Zuobin Zhu, Xiaohua Tan, Jie Liang, Ceng Zeng, Jiegen Zhang, Jun Chen, Long Ma, Ayca Dogan, Gudrun Brockmann, Oliver Goldmann, Eva Medina, Amanda D. Rice, Richard W. Moyer, Xian Man, Ke Yi, Yanke Li, Qing Lu, Yimin Huang, Dapeng Wang, Jun Yu, Hui Guo, Kun Xia, and Shi Huang. (2012) Minor alleles of common SNPs quantitatively affect traits/diseases and are under both positive and negative selection. arXiv:1209.2911[q-bio.GN]
Denzler KL, Rice AD, MacNeill AL, Fukushima N, Lindsey SF, Wallace G, Burrage M, Swetnam DM, Gray SA, Manning BR, Smith AJ, Moyer RW, and Jacobs BL. (2011) The NYCBH vaccinia virus deleted for the innate immune evasion gene, E3L, protects rabbits against lethal challenge by rabbitpox virus. Vaccine, 29(44):7659-69.
Rice AD, Gray SA, Li Y, Damon I, Moyer RW. (2011) An Efficient Method for Generating Poxvirus Recombinants in the Absence of Selection. Viruses, 3(3), 217-232.
Amanda D. Rice, Mathew M. Adams, Bernhard Lampert, Scott Foster, Randall Lanier, Alice Robertson, George Painter, and RW Moyer. (2011) Efficacy of CMX001 as a Prophylactic and Presymptomatic Antiviral Agent in New Zealand White Rabbits Infected with Rabbitpox Virus, a Model for Orthopoxvirus Infections of Humans. Viruses, 3(1), 47-62.
Rice AD, Turner PC, Embury J, Moyer RW. (2010) Pathogenesis of vaccinia virus in intratracheally infected mice and control of host interferon response genes PKR and RNaseL. Journal of Virology, 85(1):550-67.
Zhuang H, Kosboth M, Lee P, Rice A, Driscoll DJ, Zori R, Narain S, Lyons R, Satoh M, Sobel E, Reeves WH. (2006) Lupus-like disease and high interferon levels corresponding to trisomy of the type I interferon cluster on chromosome 9p. Arthritis & Rheumatism, 54(5):1573-1579.
Empig C, Kenner JR, Perret-Gentil M, Youree BE, Bell E, Chen A, Gurwith M, Higgins K, Lock M, Rice AD, Schriewer J, Sinangil F, White E, Buller RM, Dermody TS, Isaacs SN, Moyer RW. (2006) Highly attenuated smallpox vaccine protects rabbits and mice against pathogenic orthopoxvirus challenge. Vaccine, 24(17):3686-94.
Doerner KC, Braden W, Cork J, Cunningham C, Rice A, Furman BJ, McElroy D. (2005) Population Genetics of Resurgence: White-tailed Deer in Kentucky. Journal of Wildlife Management, 69(1):345-355.
University of Florida College of Medicine, Ob-Gyn Residency – 1976
C. Richard King, M.D., is the Medical Director at Clear Passage®. Dr. King is a Board Certified American College of Obstetrics and Gynecology physician with more than 40 years of clinical and surgical experience. He received his M.D. at the Medical College of Georgia in 1972 and completed his residency at the University of Florida College of Medicine in 1976.
In addition to his decades of clinical experience in private practice, he has over 20 years of experience in medical research as an investigator and author for studies focused on women’s health issues. He has served as Chief of Staff at North Florida Regional Medical Center, and as Chairman of that hospital’s institutional review board (IRB) – a position that gave him in-depth knowledge and oversight of the processes for gathering data and assuring patient safety in a wide variety of clinical trials. As the medical director of the multicenter Florida Medical Research unit, he gained extensive experience in the direct oversight and management of multiple concurrent clinical trial protocols. His dual background in medicine and clinical research provides him with a unique perspective on patient safety and study design as he leads the Clear Passage® team in testing and measuring results of the Clear Passage® Approach.
“I help bring oversight and guidance for research efforts. My 40+ years of medical and surgical experience and my interest in exploring effective new therapies, such as those offered by Clear Passage®, provide me with a unique opportunity to oversee, teach, learn, and grow.”
Selected peer-reviewed publications (in chronological order):
King, C.R. and Daly, J.W., and Monif, R.G. (1975). Topical Kanamycin in the Prevention of Abdominal Wound Infections. J. Abdominal Surgery 17:156-160
King, C.R.; Daly, J.W. (1975) The Prevention of Postoperative Pulmonary Emboli with Low-Molecular-Weight Dextran. J. OB-GYN 12:46-50
King, C.R.; Daly, J.W., and Monif, R.G. (1978) Progressive Necrotizing Wound Infections in Postirradiated Patients. J. Obstetrics And Gynecology Supp. Vol. 52 No. 1: 5S-8S
Wurn BF, Wurn LJ, King CR, Heuer MA, Roscow AS, Scharf ES, Shuster JJ. (2004) Treating Infertility and Improving IVF Pregnancy Rates with a Manual Physical Therapy Technique. Med Gen Med: 51. PMID 15266276.
Wurn LJ, Wurn BF, Kan M, King CR, Roscow AS, Scharf ES. (2006) Treating hydrosalpinx with manual physical therapy. Fertil Steril. 86 (Supp 2): S307. Abstract.
Wurn LJ, Wurn BF, King CR, Roscow AS, Scharf ES, Shuster JJ. (2006) Improving sexual function in patients with endometriosis via pelvic physical therapy. Fertil Steril.; 86 (Supp 2): S29-30. Abstract.
Wurn LJ, Wurn BF, King CR, Roscow AS, Scharf ES, Shuster JJ. (2006) Improving sexual function in patients with endometriosis via pelvic physical therapy. Fertil Steril.; 86 (Supp 2): S29-30. Abstract.
Wurn BF, Wurn LJ, King CR, Heuer MA, Roscow AS, Hornberger K, Scharf ES. (2008) Treating Fallopian Tube Occlusion with Manual Pelvic Physical Therapy. Altern Ther Health Med.;14(1):18-23. PMID 18251317.
Highlighted in Contemporary Ob/Gyn, Technology, Vol. 53, April 15, 2008, p. 12.
Rice AD, King CR, Reed ED, Patterson K, Wurn BF, and Wurn LJ. (2013) Manual Physical Therapy for Non-Surgical Treatment of Adhesion-Related Small Bowel Obstructions: Two Case Reports. Journal of Clinical Medicine, 2:1-12. doi:10.3390/jcm2010001
Rice AD, Wakefield LB, Patterson K, Reed ED, Wurn BF, King CR, and Wurn LJ. (2014) Decreasing Adhesions and Avoiding Further Surgery in a Pediatric Patient Involved in a Severe Pedestrian versus Motor Vehicle Accident. Pediatric Reports, 6:5126. PMID: 24711912
Rice AD, Wakefield LB, Patterson K, Reed ED, Wurn BF, Klingenberg B, King CR, and Wurn LJ. (2014) Development and validation of a questionnaire to measure serious and common quality of life issues for patients experiencing small bowel obstructions. Healthcare, 2(1): 139-149. doi:10.3390/healthcare2010139
Rice AD, Patterson K, Wurn BF, King CR, and Wurn LJ. (2014) Update on “Decreasing dyspareunia and dysmenorrhea in women with endometriosis via a manual physical therapy: results from 2 independent studies”. Journal of Endometriosis, 6(3):161-162. DOI: 10.5301/je.5000193
Rice AD, Patterson K, Wakefield LB, Reed ED, Breder KP, Wurn BF, King CR, and Wurn LJ. (2015) Ten-year retrospective study on the efficacy of manual physical therapy to treat female infertility. Alt Ther Health Med, 21(3):32-40.
King, C. R.; Rice, A. D. (2015) “Alternative Treatment of Non-Malignant Bowel Obstruction in Patients with Gynecological Cancer.” In Intussusception and Bowel Obstruction: Symptoms, Diagnosis and Treatment Options, ed. Rosie Miller. NOVA Scientific Publishing: Hauppauge, NY, 125–140.
Rice, A. D.; King, C. R. (2015) “Decreasing Post-Surgical Adhesions That Cause Recurrent Small Bowel Obstructions with a Conservative Manual Physical Therapy”. In Intussusception and Bowel Obstruction: Symptoms, Diagnosis and Treatment Options, ed. Rosie Miller. NOVA Scientific Publishing: Hauppauge, NY, 113–124.
Rice, A.D., Patterson, K., Reed, E.D., Wurn, B.F., Klingenberg, B., King III, C.R., & Wurn, L.W. (2016). Treating small bowel obstruction with manual physical therapy: A prospective efficacy study. BioMed Research International, 2016: 7610387. doi: 10.1155/2016/7610387
Pain at the tailbone (coccyx bone) can range from inconvenient to totally debilitating. As pain increases, some people find it difficult or virtually impossible to sit, making their lives miserable. Unfortunately, very few treatment regimens have been studied to treat this condition.
Coccyx pain (coccydynia or coccygodynia) generally begins with a trauma – often a fall or accident that pushes the tailbone forward or to the side. Persistent or repeated pressures on the coccyx from horseback riding, bicycling, or similar seating sports, or even office sitting for long hours, can cause tailbone pain. It can also occur after pelvic surgery or infection.
As the body begins to heal, strong collagen fibers, similar to the strands of a nylon rope, lay down in a random pattern across the injured area. These fibers attach to the traumatized tissues and to each other with a chemical-molecular bond in a process called cross-linking. As they lie down one upon each other, they create adhesions (internal scars) to help stop bleeding and to isolate the injury, as the first step in healing.
Once the body has healed, these linked fibers remain in place. The resulting bond can leave the tailbone stuck in a position that is forward, bent to the side, or both. This flexed position of the tailbone can cause inflammation that is exacerbated with sitting. Unable to move out of the way when a person has a bowel movement or a woman has intercourse, the fixed position of the tailbone can act like a partially closed door, causing significant pain with these movements. Sometimes the tailbone sticks out at an unnatural angle, causing pain while sitting.
Physicians will sometimes suggest an anti-inflammatory or may inject a steroid along with a numbing agent to help decrease the pain. These can provide temporary relief in some cases. Since these treatments focus more on the symptom than the cause of the pain, they may not provide a long-term solution.
Avoiding Surgery (Coccygectomy)
When pain is persistent or severe, patients begin to seek other treatments for their tailbone pain in order to regain their quality of life. Some become so frustrated that they opt to have part or all of the tailbone surgically removed. While we have seen this help in some cases, for other patients, surgery has brought a lifetime of constant, debilitating pain – often worse than the original tailbone pain.
The intent of surgery is generally to remove the coccyx so it no longer causes pain. The intent of therapy, on the other hand, is to free the bound tissues, enabling the coccyx to return to normal, to the usual pain-free position and flexibility it had before the trauma and healing events occurred.
Discover lasting relief from tailbone pain without surgery – Clear Passage® Physical Therapy offers a Free Consultation and Request Info to explore their unique, non-invasive approach that has helped countless patients regain comfort and mobility, potentially avoiding risky coccygectomy and its long, painful recovery. To learn more, visit our Apply to Therapy page.
Two Forms of Treatment
According to medical literature, adhesions in the abdomen or pelvis can be addressed in two distinctly different ways:
Clear Passage® Approach
Surgery (coccygectomy)
Therapy to Decrease Adhesions
Description of the procedure. The Clear Passage® Approach is a manual physical therapy that uses no drugs and no surgery. It has been cited in numerous studies and peer-reviewed medical journals for its ability to decrease adhesions. The studies show effectiveness with abdominopelvic pain and dysfunction caused by adhesions.
In the case of coccydynia (tailbone pain or coccyx pain), we find the tailbone is generally bound by adhesions that formed after the initial trauma or cause. In these cases, the coccyx may be pulled forward or to the side (or both), causing inflammation and pain. The pain often increases with movements such as sitting, bowel movements, and sexual intercourse.
To relieve the pain and return the body to pain-free mobility and function, we focus on decreasing the adhesions pulling the coccyx out of its normal position. We start with a thorough evaluation of the entire body, with a focus on the structures of the pelvis and lower back. We want to bring all of those areas into symmetry. We suggest – but do not require – that a person with coccyx pain undergo internal treatment via a gloved finger in the vagina or rectum. Due to the structure of the coccyx and its supporting ligaments, success may be limited without internal treatment. We always discuss the need for internal treatment with the patient before starting, and show the utmost respect for the patient’s privacy and comfort.
A good analogy to this part of the treatment is a pup tent, with poles at the front and back held in midline position by ropes on each side. If the rope on one side is pulled too tight, the pole will bend to the side, forward or backward, in a strained, awkward position. By loosening the tightness and restrictions, we return to the normal symmetry and tone, with easy, equal pressure on each side.
This therapy is ‘all natural’ in that it is 100 % ‘hands-on.’ Patients describe it as feeling like a very deep massage. In some areas, the therapy can sometimes be much lighter, depending on the area and depth being treated. Internal treatment is often described as feeling like pressure, rather than pain.
We use our hands to find adhered areas. We work to deform and detach the tiny strands that comprise adhesions – similar to pulling out the strands of a nylon rope or pulling out the run in a sweater. Your therapist may describe it as “pulling out salt-water taffy, in very slow motion.”
The therapy is site-specific; our therapists are experts at palpating and manipulating the soft tissues of the body, where adhesions generally form. We use data from the patient’s history, direct feedback from the patient during therapy, and thorough training and understanding of methods developed over 30 years to deform and detach the molecular/chemical bonds that are at the core of adhesions. The usual protocol, which is cited in our studies, consists of 20 hours of therapy spaced over five days. Treatment for coccyx pain can generally be completed in as little as 10 hours. A small percentage of the work, generally around 10 to 15 percent, is performed internally. View a short video of what Clear Passage® therapy feels like.
Advantages of Therapy
Direct access to the adhesions that are causing the pain. Due to its location and accessibility, we can directly palpate and treat adhesions that are pulling the coccyx out of its normally relaxed, midline position. In doing so, we do not cut or burn anything in your body; we do not remove anything from your body. Our focus is to deform and detach adhesions.
No hospitalization. Therapy is performed in a private treatment room, one-on-one with a highly skilled therapist certified in the work. Patients may bring a partner or family member along for company, if they like.
No anesthesia. The patient is awake and communicative during therapy. Patient involvement is encouraged, with the patient invited to give feedback throughout the course of therapy.
Decreased risk. Risk is minimal. There is no cutting or burning, and no risk of side effects from anesthesia or medications.
No foreign bodies are introduced. No staples, stitches, films, meshes, or surgical instruments are inserted into the body.
Side effects are mild and transient. The most common side effects reported with therapy are temporary tenderness, aching, fatigue, and hip or back pain. When they occur, these symptoms pass within a few days.
Improvements in other areas of the body. Because therapy focuses on detaching adhesions throughout the body, with a particular focus on the pelvis and the lower back for tailbone patients, patients regularly report significant increases in flexibility and range of motion after therapy. Many report decreased pain and/or increased function in areas near the site where they are being treated. Some report this in areas where they had forgotten or had not realized they were having a problem until therapy relieved the pain or tightness. A significant number report decreased back, neck, and headache pain due to relieving pressure on the spinal cord up to the base of the skull.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Disadvantages: Risks and Challenges of Therapy
Temporary soreness. Some people report temporary soreness during therapy, which dissipates within a few days.
Costs of therapy are generally a fraction of the cost of surgery; as with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage® is an out-of-network provider for your insurer.
Travel and time are considerations. The 20-hour therapy protocol generally takes five days (e.g., Monday – Friday); a 10-hour session takes half as long (e.g., 2 1/2 days). Our therapy is only provided by trained, certified therapists in several cities in the U.S. and U.K., and is designed for out-of-town and out-of-country patients. Most patients fly to the clinic city during the weekend, start therapy Monday morning, and are done before the next weekend.
Surgery to Remove Part or All of the Coccyx
Description of common procedures. The surgical option, coccygectomy to remove part or all of the tailbone, is rarely performed. Recovery can be long and uncomfortable for the patient. In general, the surgery involves creating a one-to-two-inch incision over the top of the coccyx. The bone covering (periosteum) is then dissected away from the bone. This allows the coccyx to be separated from the sacrum.
Unless complications arise, the operation is brief and may be done on an outpatient basis. The most difficult part of the operation is the long time it takes for the patient to heal. Reports show that it may take three months or longer after the surgery before patients note the desired relief from their symptoms. Naturally, sitting is very difficult throughout the healing process.
View surgery to remove part of a coccyx by clicking here.
Advantages of Surgery
Ease of access. The surgeon can easily access the coccyx, and surgical removal is relatively easy in most cases.
Disadvantages: Surgical Risks and Challenges
Long, painful recovery. As noted above, recovery from coccyx bone removal (coccygectomy) has been documented to take up to a year. Because the area is involved with basic daily activities (sitting, bowel movements, sexual intercourse), the recovery time can linger since the remaining portion of the sacrum cannot be isolated without activity in order to heal quickly.
Uncertain outcomes. In some cases, we have seen that surgery to remove the tailbone has been very successful. In other cases, it has brought a lifetime of pain, more debilitating than the pain before surgery.
Hospitalization during recovery. In some cases, patients must undergo a hospital stay after surgery to remove the coccyx. Patients are monitored to ensure their recovery and that there are no immediate post-surgical complications or infections.
New adhesions generally form after surgery. Medical literature compiled from over 50 years of abdominal and pelvic surgeries shows that nearly all surgeries cause new adhesions to form. Thus, despite the skills of the finest surgeon, adhesions often recur, sometimes worse than before surgery. Because surgeries cause adhesions, some of our patients feel trapped in a cycle of pain-surgery-adhesions, with no end in sight.
Pre-Treatment Screening (Surgery and Therapy)
Both therapy and surgery require patients to be screened for appropriateness and contraindications before treatment.
Screening before therapy. Before therapy, Clear Passage® directors consult applicants to review goals, risks, and potential benefits they can expect. We conduct a thorough review of the applicant’s history of healing events (prior surgery, trauma, infection, endometriosis, etc.) to determine if and where adhesions have likely formed and how they might be causing problems.
We screen applicants for two reasons:
to determine the likelihood that we can help an applicant reach his/her goal, and
to rule out contraindications that could decrease the effectiveness of therapy or cause problems.
Screening before surgery. Before surgery, physicians consult patients to review the goals, risks, and potential rewards they can expect from the procedure. They may order diagnostic tests to help rule out contraindications, such as active infection, and to help identify problem areas in the body that should be assessed during surgery. It is reasonable to ask your doctor about the likelihood of adhesion formation after surgery.
Small bowel obstruction creates major challenges for physicians and their patients. While a total small bowel obstruction is life-threatening and must often be dealt with surgically, it is an accepted fact that surgery is the number one cause of recurring bowel obstructions. Thus, the last resort medical treatment for small bowel obstruction is also the primary cause of future obstructions, underlining the need for a non-surgical treatment that can break this vicious cycle.
Many people who have undergone surgery or infection in the abdomen undergo recurring “partial small bowel obstructions” due to internal adhesions that squeeze or kink the intestines. In these cases, food may finally pass, often aided by a hospital visit. The hospitalization generally includes the insertion of a nasogastric (NG) tube through the nose into the stomach. Hospital staff will turn on an electric pump designed to constantly empty the stomach contents and relieve pressure on the digestive tract. The physician will often insert intravenous lines to introduce fluids for hydration or narcotic pain relief, in an attempt to relax and hydrate the bowel, so that food will pass. Similar intravenous lines will provide nutrition since the bowels no longer work. Patients describe the experience as a scary, uncomfortable, and harrowing experience that can take many hours or days to clear.
After a partial bowel obstruction, the patient’s ongoing concern is that despite the obstruction clearing, nothing has structurally changed. The patient is sent home with the advice, “This may and probably will happen again.” Thus, many patients feel as if they are living with a time bomb in their gut, concerned with what they can eat, what social or work activities they can and cannot do, whether they can travel, etc. By far, their greatest fear is “What happens next time – if the obstruction does not clear?”
Treating the adhesions that cause recurring bowel obstructions without surgery is considered a major advance. Our manual (hands-on) physical therapy has been shown to greatly improve quality of life and significantly decrease the incidence of small bowel obstruction in patients who receive the therapy. To date, we know of no other non-surgical treatment actually shown to clear adhesions that obstruct the bowel.
Break free from the cycle of recurrent small bowel obstructions and regain control of your life with Clear Passage® Physical Therapy’s Free Consult and Request Info – discover their groundbreaking, non-surgical approach that has been clinically proven to reduce adhesions, decrease pain, and significantly improve quality of life for patients suffering from this debilitating condition. To learn more, visit our Apply to Therapy page.
Treatment Options For Recurrent Bowel Obstructions
Clear Passage®️ Therapy to Decrease Adhesions
Description of the procedure. The Clear Passage® approach is a manual physical therapy that uses no drugs and no surgery. It has been cited in peer-reviewed medical texts and journals for its ability to decrease adhesions in the abdomen and pelvis, non-surgically. Some of the published studies include ‘before and after’ images and reports of individual patients prepared by independent diagnostic physicians. Others examine the effects of the therapy on treating adhesions for conditions, including recurring small bowel obstruction. Some studies show that the results of the therapy equal or exceed the results of surgery for improving structure and function.
The therapy is ‘all natural’ in that it is 100 percent ‘hands-on.’ Many patients describe it as feeling like a very deep massage. Our physical therapists use their hands to locate adhered areas of the body related to the patient’s pain or symptoms. They then transition to very site-specific techniques to deform and detach the tiny strands that comprise adhesions. Therapy may be compared to pulling out the strands of a nylon rope or pulling out the run in a sweater. Our therapists describe it as feeling like “pulling out salt-water taffy, in very slow motion.”
Our therapists are experts at palpating and manipulating the abdomen and pelvis, where bowel adhesions cause problems. They use data from each patient’s history and direct feedback from the patient during therapy, along with training and understanding of methods developed over 30 years to locate and detach adhesions. The protocol cited in the studies consists of 20 hours of therapy, spaced over five or more days. View a short video of what Clear Passage®️ therapy is like.
Advantages of Therapy
No hospitalization. Therapy is always performed in a private treatment room, one-on-one with a highly skilled therapist certified in the work. Patients may bring a partner or family member along for company, if they like.
No anesthesia. Without general anesthesia, there is no risk of neurotoxicity to the brain or other areas of the body. The patient is not only awake and communicative during the procedure, but we also encourage patient involvement; each patient is invited to give feedback throughout the course of therapy. We feel that involving each patient in their care and soliciting their feedback during each therapy session generates better results.
Decreased risk. Risk is minimal. There is no cutting or burning, no risk from anesthesia, and no risk of inadvertently cutting through a nearby organ or other structure.
No foreign bodies are introduced. No staples, stitches, films, or meshes are inserted into the body. No cameras, gas, lights, or surgical instruments enter the body.
Side effects are mild and transient. The most common side effects reported with therapy are temporary tenderness, aching, fatigue, and hip or back pain. Temporary soreness is generally relieved with a 20-minute Epsom salt bath or compress in the evening.
Improvements in other areas of the body. Because therapy focuses on detaching strong adhesions that tend to form in various areas of the body, most patients report increases in flexibility and range of motion after therapy. Many report decreased pain and/or increased function in areas near the site where they are being treated – or even at distal sites. This pain reduction is often noted in the low back due to the freeing of abdominal adhesions from the front of the lumbar vertebrae. Some patients report improvements in areas where they had forgotten or had not realized they were having a problem, until therapy relieved the pain or tightness.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Disadvantages: Risks and Challenges of Therapy
Therapists cannot visualize the adhesions. Initially, we deduce the likelihood of adhesions by conducting a thorough review of each patient’s history and symptoms. To gain further insights, we may require diagnostic tests or documentation from your physician. During therapy, we palpate the areas of your body related to your symptoms and other areas where we note scarring, tightness, spasm, or increased temperature. Because our therapists have been practicing manual therapy for most of their professional lives, they are experts at palpating and treating the body.
Costs of therapy are generally a fraction of the cost of surgery. As with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage®️ is an out-of-network provider for your insurer. When considering the costs, we encourage patients to measure the cost of their quality of life and peace of mind vs. the sacrifices they make due to living with adhesions. Download our Insurance PDF to send to your insurance.
Travel and time are considerations. Therapy generally takes five days (e.g., Monday – Friday); it is only provided by trained, certified therapists in several cities in the U.S. and U.K. The 5-day program is designed for out-of-town and out-of-country patients. We suggest that patients with a history of bowel obstructions remain in town for an extra day before returning home. The goal is to allow the body to return to homeostasis before undergoing changes in bowel air pressure that can accompany an airline flight.
Surgery to Decrease Abdominopelvic Adhesions
Description of common procedures. Some patients with recurring bowel obstructions are encouraged to undergo surgery to decrease adhesions in the abdomen or pelvis. The intent of adhesion surgery (adhesiolysis) is to cut or burn adhesions affecting the bowel and return the intestines to an earlier state of mobility and function. In a laparoscopy, the physician places the patient under general anesthesia and then makes several holes (ports) in the body. Using one of these ports, the doctor will first fill the abdominal cavity with gas to separate the organs. This separation allows the surgeon to view a path to insert the surgical instruments s/he will use to cut or burn adhesions affecting the bowel. The doctor will also insert a light and a camera through the other port(s). You can observe a laparoscopy to decrease adhesions by clicking here.
When intestinal adhesions are extensive, the physician may perform or transition to an open surgery called a laparotomy. In that surgery, the body is cut open with a scalpel, and then the skin and outer layers are separated with a metal retractor. Next, the physician enters with a scalpel, laser, or other surgical instrument to cut or burn any adhesions s/he may find that are affecting the intestines. S/he will repair or cauterize any bleeding that occurs, and may check the area for other problems before exiting the body. Finally, s/he will close the body with stitches and send the patient to a room where recovery can be monitored. You can view an open bowel resection by clicking here.
In a laparotomy, the surgeon will often remove (then replace) all 21 feet (7 meters) of the bowel to search for problem areas.
Advantages of Surgery
Direct visualization. The surgeon can directly see, then burn or cut adhesions that do not appear on diagnostic tests such as MRI or CT scan. Complications can occur in patients with significant adhesions if the doctor has difficulty seeing through the layers s/he is cutting (see below).
Observe nearby areas. In addition to treating the adhered area, the physician can visualize nearby structures. Thus, s/he can note and possibly treat any other problem areas in the vicinity.
Operative report. The doctor will dictate a report that describes what s/he observes and the procedures performed during the surgery.
Disadvantages: Surgical Risks and Challenges
Anesthesia complications. Recent studies have considered whether general anesthesia may have a neurotoxic effect on the brain or other areas of the body. (Perousakis & Hemmings, 2009)
Inadvertent enterotomy. When a patient has significant adhesions, it can be difficult for the doctor to see the structures beneath them. Thus, a surgeon can unintentionally cut into a nearby healthy organ or other structure, called an inadvertent enterotomy (IE). An IE can cause serious problems or death. In a study from the Journal of the Society of Laparoscopic Surgeons, the authors note that:
“IE in laparoscopic abdominal surgery is underreported.”
Hospitalization during recovery. Abdominopelvic lysis of adhesions is a major surgery, and most patients undergo a hospital stay afterwards. During this time, the patient’s condition was closely monitored to ensure recovery and avoid post-surgical complications or infections.
New adhesions generally form after surgery. A mammoth 50-year review of abdominal and pelvic surgery in the U.S. revealed that nearly all abdominal and pelvic surgeries cause new adhesions to form. Thus, adhesions can recur – sometimes worse than before the surgery to remove them.
Surgery is widely regarded as the primary cause of bowel obstructions due to post-surgical adhesion formation.
Pre-Treatment Screening (Surgery and Therapy)
Both therapy and surgery require patients to be screened for appropriateness and contraindications before treatment.
Screening before therapy. Before we can accept you for therapy, our staff will conduct a thorough review of your history of healing events (prior surgery, trauma, infection, endometriosis, etc.) to determine where adhesions have likely formed and how they might be causing problems related to your symptoms and complaints. We then consult with each patient to review goals, risks, and the potential benefits they can expect.
We want you to do well and to have a reasonable chance to reach your goals. We will accept you if we feel we can help you; we will alert you if we have concerns that you will not do well with therapy. Similarly, we will not accept you if we feel that you will not have a favorable outcome.
Screening before surgery. Before surgery, your physician may order diagnostic tests to help rule out contraindications, such as active infection, and to help identify problem areas in the body that should be assessed during surgery. Your doctor should consult with you to review the goals of surgery, along with the risks and potential rewards you can expect. We encourage you to ask your doctor about the risk of post-surgical adhesion formation and an estimate of the need for future surgeries.
Polycystic ovary syndrome (PCOS) is now officially renamed Polyendocrine Metabolic Ovarian Syndrome (PMOS), following an international expert consensus published in The Lancet in May 2026.
Success Treating PCOS Infertility Without Surgery
Clear Passage®️ is a world leader with approaching three decades of experience treating female infertility without surgery or drugs. In a landmark 10-year study[i] treating infertile women, our non-surgical therapy yielded pregnancy rates for women with PCOS similar to standard medical treatments, but without surgery (study chart below).
In addition to studies examining our success in treating the mechanical causes of infertility, clinical trials have demonstrated significant improvement in hormone levels after therapy. Published peer-reviewed medical journal citations noted that our therapy improved fertility for many women. Perhaps the biggest advantage of using Clear Passage® for women with PCOS was to avoid surgery (drilling holes in the ovary, or cutting wedges from it, to improve hormone levels or help trapped eggs escape and fertilize). You can learn more about these surgeries in the following videos:
Successful reproductive activity depends on a medically recognized communication loop between the ovaries (in the pelvis) and the pituitary and hypothalamus glands (deep inside the head). Housed within a well-protected cavity of the sphenoid bone in the center of the skull, the pituitary gland is considered the “master gland” of female reproduction and is intimately involved in hormone production and regulation.
While physicians recognize that a communication loop occurs among the pituitary, hypothalamus, and the ovaries, the exact mechanism of that communication remains a mystery. This interplay among glands, called the hypothalamic-pituitary-ovarian (HPO or PHO) axis, is largely responsible for whether or not a woman’s eggs can reach maturity during the process of reproduction. Due to the very positive results we have documented and published about our patients with PCOS and other hormone-related infertility, we believe there is a strong mechanical mechanism in the body’s hormone systems that we can improve, at least for female infertility.
Published Pregnancy Rates Treating Treating PCOS-Related Infertility
Clear Passage®️ 53.57%
Ovarian Drilling Surgery 20-64%
Ovarian Wedge Surgery 78%
Clear Passage®, then IVF 56.16%
IVF alone: 24.11%
Overview of Treatment Options
According to medical literature, adhesions can be addressed in two distinctly different ways:
Clear Passage®️ Approach
Surgery
Clear Passage® Therapy for PCOS
Our success with women with hormonal disorders is due in large part to our work on the major attachments of the dura. The dura is a fascial sheath that surrounds the spinal cord, from the bottom of the tailbone at the coccyx to attachments at the top of the neck and the base of the skull. From there, it enters the skull through a large opening (the foramen magnum), then spreads out to surround the brain and every structure in the head. Naturally, this includes the sphenoid bone, which houses the pituitary-hypothalamus complex. Strong sheaths of the dura totally surround and infuse the pituitary gland.
Description of the procedure. The Clear Passage® approach is a manual physical therapy; it is ‘all natural’ in that it is 100% ‘hands-on.’ While some patients describe CP as feeling like a very deep massage, others note that it can sometimes be much lighter, depending on the area and depth being treated. Highly trained and certified in this therapy, our licensed therapists use their hands to deform and detach the tiny strands that comprise adhesions – similar to pulling out the strands of a nylon rope or pulling out the run in a sweater. Therapists sometimes say it “feels like I’m pulling out taffy, in very slow motion.”
The therapy is very site-specific for adhesions. Therapists certified to perform this work are experts at palpating and manipulating the soft tissues of the body, where adhesions that affect fertility generally form. We use data from the patient’s history along with direct feedback from each patient during therapy. Each provider receives extensive training to understand the methods developed over 30 years to deform and detach the molecular/chemical bonds that bind reproductive organs and glands to larger nearby structures. In releasing those bonds, the body tends to return to an earlier state of pain-free mobility and function.
During the course of therapy, we treat the full body as we focus on the dura and all of its attachments, from the tailbone to the head. This sheath surrounds the central nervous system, which is responsible for a myriad of complex activities and commands. Any adhesive restriction within that system can create profound effects in various areas of the body.
The usual protocol cited in the published studies consists of 20 hours of therapy spaced over five or more days. Patients often start therapy on Monday morning, receive four hours of therapy a day with a break for lunch, and are done Friday afternoon. Other than that, they are free to work, rest, or take a break from a busy lifestyle. Many women set aside these five days as a “special time to help their bodies heal.” Learn more and view a short video of Clear Passage®️ treatment for blocked tubes by clicking below.
Advantages of Therapy
No hospitalization. Therapy is performed in a clean, private treatment room, one-on-one with a highly skilled physical therapist certified in the work. You are invited to bring a partner or family member along for company, if you like.
No anesthesia. While risks of anesthesia are small, they do exist. Our patients are awake and communicative during the procedure. We actively encourage patient involvement and feedback. In doing so, we invite each patient to be an active member of the team that is working hard to achieve their results. In addition, we provide education on the formation and deformation of adhesions anywhere in the body. We teach each patient self-treatment techniques she can use for her entire life. This education and communication are not available to a person under anesthesia.
Decreased risk. Risk is minimal because there is no cutting or burning. There is no risk of forming post-surgical adhesions that can rebind the delicate reproductive structures or spread to other organs. Therapy also avoids the surgical risk of inadvertently cutting through a nearby structure, such as the bowel, bladder, or even stomach (we have seen all of these).
No foreign objects are placed deep within your body. No stitches, staples, films, or meshes are inserted into the body. No cameras, gas, lights, surgical instruments, or contaminants enter the abdominal cavity from the ‘outside world.’
Side effects are mild, transient, or positive. The most common side effects patients report are temporary tenderness, aching, fatigue, and hip or back pain. When they occur, these PCOS symptoms pass with a 20-minute Epsom salt bath, compress, or both in the evening of your therapy session. Other side effects cited in medical literature are positive. These include decreased intercourse pain, increased desire, arousal, lubrication, and orgasm (including first-time orgasms).
Verified success rates. Several peer-reviewed studies measure the ability of this therapy to decrease pain and increase fertility for women diagnosed with endometriosis. In a ten-year study with hundreds of participants, our fertility success rates for women with blocked tubes equaled or surpassed those of surgery. You may view all of our success rates by clicking here.
Improvements in other areas of the body. Because therapy focuses on detaching adhesions throughout the body, it is common for patients to report a significant increase in flexibility and range of motion after therapy. In addition, many report decreased pain and/or increased function in areas near the sites where they are being treated. Some report this phenomenon in areas they had forgotten or had not realized they were having a problem with, until therapy relieved the pain or tightness.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Risks and Challenges of Therapy
Therapists cannot visualize the adhesions. Initially, we deduce the likelihood of adhesions by conducting a thorough review of your history and symptoms. To gain further insights, we may request diagnostic tests or documentation from your physician. As well as treating the ovaries, tubes, and uterus, we palpate any areas where we note spasm, asymmetry, thickened tissues, or increased temperature. Because our therapists have been doing manual therapy for most of their professional careers, they are experts at palpating the body.
Costs of therapy are generally a fraction of the cost of surgery; as with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage®️ is an out-of-network provider for your insurer.
Travel and time are considerations. Designed for local and out-of-town patients, therapy is given for 20 hours over a five-day period (e.g., Monday – Friday). It is provided by trained, certified therapists in several cities in the U.S. and the U.K.
Surgery to Treat PCOS
Description of surgery. The intent of ovarian surgery is to cut away parts of the ovary (ovarian wedging) or drill holes (ovarian drilling) in it in order to improve hormonal balance. The surgery can also help eggs escape the collagenous blanket covering the ovary. When performed via laparoscopy, the physician puts the patient under general anesthesia, then cuts several holes (ports) in the body. One of the ports is used to fill the cavity with a gas to separate the organs so that the surgeon can create a path through which s/he can visualize the structures s/he needs to remove or repair. Using the other ports, the doctor will insert a light, camera, and surgical instrument(s) with which they can cut away or drill holes in the ovary to improve function.
When adhesions or the problem are extensive, the physician may elect to perform an open surgery called a laparotomy. In that surgery, the physician cuts the body open via a long incision and then separates the sides with a metal retractor. Next, the surgeon enters with a scalpel, laser, or other surgical instrument to cut or burn any adhesions s/he may find. S/he will repair or cauterize any bleeding that occurs and will often check for other problems before exiting the body and sending the patient to a room for post-surgical recovery.
Advantages of Surgery
Direct visualization. The surgeon can directly see the area and visually assess the internal condition. In some cases, s/he may not be able to see through thick blankets of adhesions. This can lead to problems (inadvertent enterotomy), noted below.
Observe nearby areas. In addition to treating the adhered area, the physician can see and assess the condition of nearby structures, noting any areas that may be of concern.
Operative report. The doctor will dictate a report that describes what s/he observes and the procedures s/he performs during the surgery.
Surgical Risks and Challenges
Anesthesia complications. Recent studies have raised some concerns about neurotoxicity, with mild to moderate brain damage for patients who undergo one or more sessions of general anesthesia.
Inadvertent enterotomy. When a patient has significant adhesions, it can be difficult for the doctor to see the structures beneath them. Thus, a surgeon can unintentionally cut into a nearby healthy organ or other structure, called an inadvertent enterotomy (IE). An IE can cause serious problems or death. Authors from a study in the Journal of the Society of Laparoscopic Surgeons note:
“Death from IE is not uncommon.”
“IE in laparoscopic abdominal surgery is underreported”.
“IE was the most common laparoscopic complication at our hospital”.
Hospitalization during recovery. Many surgeries are followed by a hospital stay, during which patient recovery can be monitored for post-surgical complications or infections.
New adhesions generally form after surgery. It is a well-accepted medical fact that nearly all surgeries in the abdomen or pelvis cause new adhesions to form. Thus, pain and adhesions can recur, sometimes worse than before the surgery to remove them.
Risks of laparoscopy include:
Hernia,
Infection,
Blood clots,
Adverse reactions to anesthesia,
Abdominal inflammation or infection,
Bleeding and the potential need for a blood transfusion,
Specific conditions that can increase your risk of complications during surgery include:
Stroke
Obesity
Diabetes
Smoking
Seizures
Drug allergies
High blood pressure
Obstructive sleep apnea
History of heavy alcohol use
History of adverse reactions to anesthesia
Medications, such as aspirin, that can increase bleeding
Other medical conditions involving your heart, lungs, or kidneys
Pre-Treatment Screening (Surgery and Therapy)
Screening every patient for appropriateness and contraindications before therapy or surgery is a necessary part of pre-treatment workup.
Screening before therapy. Clear Passage®️ directors and staff consult with applicants to review goals, risks, and potential benefits that they can expect from therapy. We conduct a thorough review of your history of healing events (prior surgery, trauma, infection, endometriosis, etc.) to determine if and where adhesions have likely formed and how they might be causing problems. In addition, we may require additional tests or correspondence from your physician before we can accept you for therapy.
Screening before surgery. Your surgeon should consult with you to review the goals, risks, and potential rewards you can expect from the procedure. They may order diagnostic tests to help rule out contraindications such as active infection and to help identify problem areas in the body that should be assessed during surgery.
Liakakos, T., Thomakos, N., Fine, P., Dervenis, C., & Young, R. (2001). Peritoneal adhesions: etiology, pathophysiology, and clinical significance. Recent advances in prevention and management. Dig Surg, 18(4), 206–273
Perousanksy, M. and Hemmings Jr, H.C. (2009). Neurotoxicity of General Anesthetics: Cause for Concern? Anesthesiology, 111(6), 1365-1371.
Binenbaum, S. & Goldfarb, M. (2006). Inadvertent enterotomy in minimally invasive abdominal surgery. Journal of the Society of Laparoendoscopic Surgeons, 10(3): 336-340
Fallopian tubes are the delicate environment where life begins. Each of these two narrow structures is the place where a one-celled egg can meet a sperm, creating a life that will continue its journey to implantation in the uterus. As such, this tiny organ must be patent (open) and able to function freely and without restriction for a pregnancy to occur.
The primary cause of tubal occlusion (blockage) is internal scarring by adhesions. Adhesions form as glue-like bonds in the reproductive tract as the body’s initial response to pelvic inflammatory disease (PID), endometriosis, sexually transmitted infection, a prior surgery, or ectopic pregnancy.
After adhesions form, they can remain in the body for a lifetime. When they form at the distal end of the tube (near the ovary), they can cause swelling of the tube in a condition called hydrosalpinx. Adhesions can form and spread into any part of the tube and anywhere in the pelvis. Wherever they form, they can squeeze reproductive structures or attach them to other structures, further decreasing fertility.
The interior dimension of a fallopian tube is tiny, designed to transport a single-celled egg to meet much tinier sperm, in order to create a pregnancy. The inner lining of a fallopian tube looks like a lush underwater garden, lined with microscopic cilia that help the process along. The act of cutting into such delicate structures to perform a surgical repair is both challenging and problematic. While surgery can sometimes open a blocked fallopian tube, physicians know that there is a significant risk of post-surgical adhesions – scar tissue that tends to re-block the tube within a few months.
Surgery to clear proximal occlusion (blockage near the uterus)
Surgery is considered when the site of the blockage is proximal, near the uterus. In this instance, the physician can often access the occlusion by inserting a sterilized wire, sometimes with a tiny balloon attached, into the tube via the uterus. Thus, the doctor can avoid the costs and risks of the additional post-surgical adhesions associated with laparoscopy. Risks with this minimally invasive technique include pinpoint perforations of the vagina, cervix, uterus, or fallopian tube as the wire passes through these structures.
Surgery to clear distal occlusion and hydrosalpinx (blockage in the mid or distal tube)
Most physicians will not operate on tubes that are blocked beyond the portion closest to the uterus. Designed to carry individual cells, the tube is so tiny and delicate that post-surgical scars tend to re-block the tube, even after a successful surgery. For this reason, surgeons generally avoid any attempt to open tubes that are blocked beyond the uterine opening. In some cases, such as hydrosalpinx (swollen tube), the physician will recommend removal of the blocked tube and referral for in vitro fertilization (IVF).
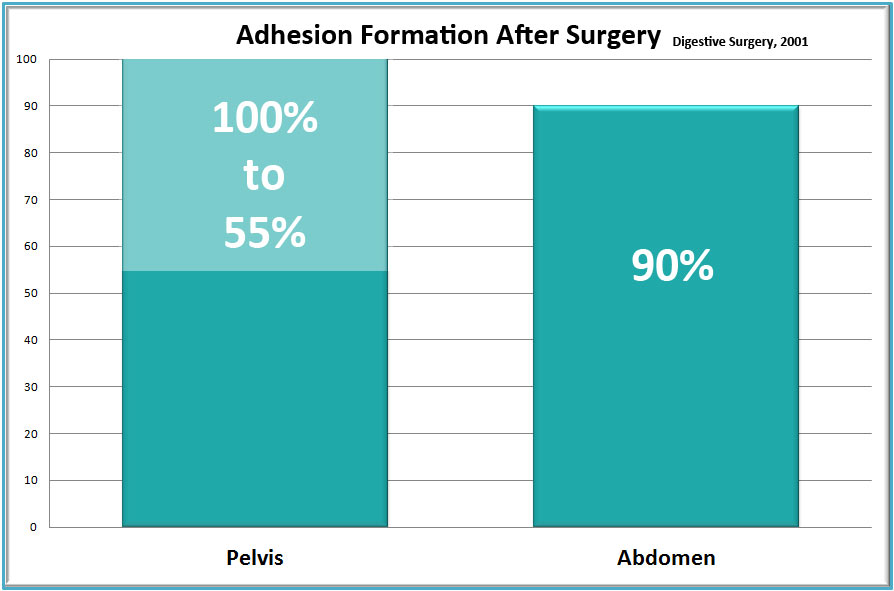
In a mammoth 58-year study of medical literature, researchers found that adhesions occur in more than 90% of patients following major abdominal surgery and in 55-100% of women undergoing pelvic surgery. The study noted that “small-bowel obstruction, infertility, chronic abdominal and pelvic pain, and difficult re-operative surgery were the most common consequences of the adhesions.” Underlining the ongoing difficulty adhesions can cause, the study concluded, “Despite elaborate efforts to develop effective strategies to reduce or prevent adhesions, their formation remains a frequent occurrence after abdominal surgery.” In short, post-surgical adhesions are a major problem for physicians and patients alike.
With over a dozen citations and studies published in medical journals, we can quantify success rates for the dozens of women whose tubes we have opened – most of whom are now mothers. To date, Clear Passage® has seen over 1,000 babies born to our patients – women diagnosed as infertile before they came to us for therapy.
Clear Passage®️ Therapy to Open Tubes, Improve Function and Fertility
Over the last 20 years, numerous peer-reviewed studies and citations have cited Clear Passage® therapy for our ability to increase fertility by decreasing adhesions. Several of the studies have centered on its ability to help women with occluded fallopian tubes, without the need for surgery.
Description of the procedure. The Clear Passage® approach is a manual physical therapy; it is ‘all natural’ in that it is 100% ‘hands-on.’ While some patients describe CP as feeling like a very deep, site-specific massage, others note that it can sometimes be much lighter, depending on the area and depth being treated. Highly trained and certified in this therapy, our licensed therapists use their hands to deform and detach the tiny strands that comprise adhesions – similar to pulling out the strands of a nylon rope or pulling out the run in a sweater. Therapists sometimes say it “feels like I’m pulling out taffy, in very slow motion.”
The therapy is very site-specific for adhesions. Therapists certified to perform this work are experts at palpating and manipulating the soft tissues of the body, where adhesions generally cause problems with infertility. They use data from the patient’s history along with direct feedback from each patient during therapy. Each provider receives extensive training to understand the methods developed by our directors over 30 years to deform and detach the molecular/chemical bonds to the delicate cilia on the inner walls of the fallopian tube or bind the tube to nearby structures. When we are successful in releasing those bonds, the tubes tend to return to an earlier state of pain-free mobility and function.
The usual protocol cited in the published studies consists of 20 hours of therapy spaced over five or more days. Patients often start therapy on Monday morning, receive four hours of therapy a day with a break for lunch, and are done Friday afternoon. Other than that, they are free to work, rest, or take a break from a busy lifestyle. Many women set aside these five days as a “special time to help their bodies heal.” Learn more and view a short video of Clear Passage® treatment for blocked tubes.
Advantages of Therapy
No hospitalization. Therapy is performed in a clean, private treatment room, one-on-one with a highly skilled physical therapist certified in the work. You are invited to bring a partner or family member along for company, if you like.
No anesthesia. While risks of anesthesia are small, they do exist. Our patients are awake and communicative during the procedure. We actively encourage patient involvement and feedback. In doing so, we invite each patient to be an active member of the team that is working hard to achieve their results. In addition, we provide education on the formation and deformation of adhesions anywhere in the body. We teach each patient self-treatment techniques she can use for her entire life. This education and communication are not available to a person under anesthesia.
Decreased risk. Risk is minimal because there is no cutting or burning. There is no risk of forming post-surgical adhesions that can rebind the delicate reproductive structures or spread to other organs. Therapy also avoids the surgical risk of inadvertently cutting through a nearby structure, such as the bowel, bladder, or even stomach (we have seen all of these).
No foreign objects are placed deep within your body. No stitches, staples, films, or meshes are inserted into the body. No cameras, gas, lights, surgical instruments, or contaminants enter the abdominal cavity from the ‘outside world.’
Side effects are mild, transient, or positive. The most common side effects patients report are temporary tenderness, aching, fatigue, and hip or back pain. When they occur, these symptoms are minimized with an anti-inflammatory or a 20-minute compress or soak with Epsom salts, in the evening after therapy. Other side effects cited in medical literature are positive. These include decreased intercourse pain, increased desire, arousal, lubrication, and orgasm (including first-time orgasms).
Verified success rates. Several peer-reviewed studies measure the ability of this therapy to decrease pain, if any, and increase fertility for women diagnosed with blocked fallopian tubes. In a ten-year study with hundreds of participants, our fertility success rates for women with blocked tubes rivaled or surpassed those of surgery. You may view all of our success rates by clicking here.
Improvements in other areas of the body. Because therapy focuses on detaching adhesions throughout the body, it is common for patients to report a significant increase in flexibility and range of motion after therapy. In addition, many report decreased pain and/or increased function in areas near the sites where they are being treated. Some report this phenomenon in areas they had forgotten or had not realized they were having a problem with, until therapy relieved the pain or tightness.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Risks and Challenges of Therapy
Therapists cannot visualize the adhesions. Initially, we deduce the likelihood of adhesions by conducting a thorough review of your history and symptoms. To gain further insights, we may request diagnostic tests or documentation from your physician. As well as treating the tubes and uterus, we palpate any areas where we note spasm, asymmetry, thickened tissues, or increased temperature. Because our therapists have been doing manual therapy for most of their professional lives, they are experts at palpating the body.
Costs of therapy are generally a fraction of the cost of surgery; as with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage®️ is an out-of-network provider for your insurer.
Travel and time are considerations. Designed for local and out-of-town patients, therapy is given for 20 hours over a five-day period (e.g., Monday – Friday). It is provided by trained, certified therapists in several cities in the U.S. and the U.K.
No medical techniques have a 100% success rate. If we are unable to open your tubes, your chances for a successful IVF performed within 15 months after therapy increase by roughly 50%, per published studies. View our success rates.
Description of surgery. The intent of tubal ligation surgery is to cut or burn the adhesions blocking the tube, then reattach any options that were cut or separated. In a laparoscopy, the physician puts the patient under general anesthesia, then cuts several holes (ports) in the body. One of the ports is used to fill the cavity with a gas to separate the organs so that the surgeon can create a path through which s/he can visualize the structures s/he needs to remove or repair. Using the other ports, the doctor will insert a light, camera, and surgical instrument(s) with which they can cut or burn the tube to eliminate any blockage.Click here to view a surgery to open blocked fallopian tubes
When adhesions are extensive, the physician may elect to perform an open surgery called a laparotomy. In that surgery, the physician cuts the body open via a longer incision and then may separate the sides with a metal retractor. Next, the surgeon enters with a scalpel, laser, or other surgical instrument to repair the tubes and to cut or burn any adhesions s/he may find. S/he will repair or cauterize any bleeding that occurs and will often check for other problems before exiting the body and sending the patient to a room for post-surgical recovery.
Advantages of Surgery
Direct visualization. The surgeon can directly see the area and visually assess the internal condition. In some cases, s/he may not be able to see through thick blankets of adhesions. This can lead to problems (inadvertent enterotomy) noted below.
Observe nearby areas. In addition to attempting to repair the tube, the physician can see and assess the condition of nearby structures, noting any areas that may be of concern.
Operative report. As with therapy, the doctor will dictate a report that describes what s/he observes and the procedures s/he performs during the procedure.
Surgical Risks and Challenges
Anesthesia complications. Recent studies have raised possible concerns about neurotoxicity, with mild to moderate brain damage for patients who undergo one or more sessions of general anesthesia.
Inadvertent enterotomy. When a patient has significant adhesions, it can be difficult for the doctor to see the structures beneath them. Thus, a surgeon can unintentionally cut into a nearby healthy organ or other structure, called an inadvertent enterotomy (IE). An IE can cause serious problems or death. Authors from a study in the Journal of the Society of Laparoscopic Surgeons note:
“Death from IE is not uncommon.”
“IE in laparoscopic abdominal surgery is underreported.”
“IE was the most common laparoscopic complication at our hospital.”
Hospitalization during recovery. Some surgeries are followed by a hospital stay, during which patient recovery can be monitored for post-surgical complications or infections.
New adhesions generally form after surgery. It is a well-accepted medical fact that nearly all surgeries in the abdomen or pelvis cause new adhesions to form. Thus, pain and adhesions can recur, sometimes worse than before the surgery to remove them.
Risks of laparoscopy include:
Hernia,
Infection,
Blood clots,
Adverse reactions to anesthesia,
Abdominal inflammation or infection,
Bleeding and the potential need for a blood transfusion,
Specific conditions that can increase your risk of complications during surgery include:
Stroke
Obesity
Diabetes
Smoking
Seizures
Drug allergies
High blood pressure
Obstructive sleep apnea
History of heavy alcohol use
History of adverse reactions to anesthesia
Medications, such as aspirin, that can increase bleeding
Other medical conditions involving your heart, lungs, or kidneys
Pre-Treatment Screening (Surgery and Therapy)
Screening every patient for appropriateness and contraindications before therapy or surgery is a necessary part of pre-treatment workup.
Screening before therapy. Clear Passage®️ directors and staff consult with applicants to review goals, risks, and potential benefits that they can expect from therapy. We conduct a thorough review of your history of healing events (prior surgery, trauma, infection, endometriosis, etc.) to determine if and where adhesions have likely formed and how they might be causing problems. In addition, we may require additional tests or correspondence from your physician before we can accept you for therapy.
Screening before surgery. Your surgeon should consult with you to review the goals, risks, and potential rewards you can expect from the procedure. They may order diagnostic tests to help rule out contraindications, such as active infection, and to help identify problem areas in the body that should be assessed during surgery.
Liakakos, T., Thomakos, N., Fine, P., Dervenis, C., & Young, R. (2001). Peritoneal adhesions: etiology, pathophysiology, and clinical significance. Recent advances in prevention and management. Dig Surg, 18(4), 206–273
Perousanksy, M. and Hemmings Jr, H.C. (2009). Neurotoxicity of General Anesthetics: Cause for Concern? Anesthesiology, 111(6), 1365-1371. Binenbaum, S. & Goldfarb, M. (2006). Inadvertent enterotomy in minimally invasive abdominal surgery. Journal of the Society of Laparoendoscopic Surgeons, 10(3): 336-340
Hydrosalpinx is a condition that occurs when a fallopian tube is blocked and fills with serous or other fluid after blockage or narrowing at the distal end of the tube, near the ovary.
Hydrosalpinx is one aspect of tubal disease. With these conditions, the tube becomes distended, giving the tube a characteristic sausage-like shape. The blockage may occur in one or both tubes. A tube with a hydrosalpinx is considered beyond repair by many physicians who feel it will never support a pregnancy. We believed this to be the case; then we were surprised when several patients, who came to therapy with hydrosalpinx, became pregnant after we treated them.
Swollen tubes are largely attributed to adhesions, internal scars that form as the first step in healing from a pelvic infection, surgery, or endometriosis. Acting like glue in the reproductive tract, adhesions are composed of tiny but powerful collagen fibers that bind to each other in a random pattern. Fallopian tubes are the delicate environment where life begins. Each of these two structures is the place where a one-celled egg can meet a sperm to create an embryo that will continue its journey to implantation in the uterus. As such, this tiny organ must be open and able to function without restriction in order for a pregnancy to occur.
After adhesions form, they can remain in the body for a lifetime. When they form at the distal end of the tube (near the ovary), they can cause swelling of the tube – a hydrosalpinx. From there, adhesions can spread into any part of the reproductive tract or pelvis, including the bladder, rectum, bowel, tailbone, or low back. They can squeeze any of these structures or attach them to others, further decreasing fertility and sometimes causing pain. They can form on the outer walls of the uterus, squeezing it and causing spasm, decreasing the chance for implantation. They can also form on the inner walls, covering parts or all of the surface designed to accept a fertilized egg, which we feel can contribute to miscarriage.
Fallopian tubes are tiny, designed to transport a single-celled egg to meet much tinier sperm, in order to create a pregnancy. The inner lining of a fallopian tube looks like a lush underwater garden, lined with tiny cilia that help the process along. The act of cutting into such delicate structures to perform a repair is problematic.
Surgery to clear distal occlusion and hydrosalpinx (blockage in the mid or distal tube)
Most physicians will not operate on tubes that are blocked beyond the portion closest to the uterus. Designed to carry individual cells, the tube is so tiny and delicate that post-surgical scars tend to re-block the tube, even after a successful surgery. For this reason, surgeons generally avoid any attempt to open tubes that are blocked beyond the uterine opening. In hydrosalpinx (swollen tube), we find that most physicians recommend removal of the blocked tube and referral for in vitro fertilization (IVF).
In a mammoth 58-year study of medical literature, researchers found that adhesions occur in more than 90% of patients following major abdominal surgery and in 55-100% of women undergoing pelvic surgery. The study noted that “small-bowel obstruction, infertility, chronic abdominal and pelvic pain, and difficult re-operative surgery were the most common consequences of the adhesions.” Underlining the ongoing difficulty adhesions can cause, the study concluded, “Despite elaborate efforts to develop effective strategies to reduce or prevent adhesions, their formation remains a frequent occurrence after abdominal surgery.” In short, post-surgical adhesions are a major problem for physicians and patients alike.
Discover hope for your fertility journey with Clear Passage® Physical Therapy’s Free Consult and Request Info – learn how their innovative, non-surgical approach has successfully treated hydrosalpinx, offering a natural alternative to tube removal and potentially restoring your ability to conceive. To learn more, visit our Apply to Therapy page.
Overview of Treatment Options
Clear Passage®️ Therapy to Clear Hydrosalpinx and Improve Fertility
With over a dozen citations and studies published in medical journals, we can clearly quantify success rates for the dozens of women whose tubes we have opened – most of whom are now mothers. To date, Clear Passage® has seen over 1,000 babies born to our patients – women diagnosed as infertile before they came to us for therapy.
Description of the procedure. The Clear Passage® approach is a manual physical therapy; it is ‘all natural’ in that it is 100% ‘hands-on.’ While some patients describe CP as feeling like a very deep massage, others note that it can sometimes be much lighter, depending on the area and depth being treated. Highly trained and certified in this therapy, our licensed therapists use their hands to deform and detach the tiny strands that comprise adhesions – similar to pulling out the strands of a nylon rope or pulling out the run in a sweater. Therapists sometimes say it “feels like I’m pulling out taffy, in very slow motion.”
The therapy is very site-specific for adhesions. Therapists certified to perform this work are experts at palpating and manipulating the soft tissues of the body, where adhesions that affect the reproductive organs generally form. They use data from the patient’s history along with direct feedback from each patient during therapy. Each provider receives extensive training to understand the methods developed by our directors over 30 years to deform and detach the molecular/chemical bonds that bind endometrial implants to the underlying structures. In releasing those bonds, the body tends to return to an earlier state of pain-free mobility and function.
The usual protocol cited in the published studies consists of 20 hours of therapy spaced over five or more days. Patients often start therapy on Monday morning, receive four hours of therapy a day with a break for lunch, and are done Friday afternoon. Other than that, they are free to work, rest, or take a break from a busy lifestyle. Many women set aside these five days as a “special time to help their bodies heal.” Learn more and view a short video of Clear Passage®️ treatment for blocked tubes by clicking below.
Advantages of Therapy
No hospitalization. Therapy is performed in a clean, private treatment room, one-on-one with a highly skilled physical therapist certified in the work. You are invited to bring a partner or family member along for company, if you like.
No anesthesia. While risks of anesthesia are small, they do exist. Our patients are awake and communicative during the procedure. We actively encourage patient involvement and feedback. In doing so, we invite each patient to be an active member of the team that is working hard to achieve their results. In addition, we provide education on the formation and deformation of adhesions anywhere in the body. We teach each patient self-treatment techniques she can use for her entire life. This education and communication are not available to a person under anesthesia.
Decreased risk. Risk is minimal because there is no cutting or burning. There is no risk of forming post-surgical adhesions that can rebind the delicate reproductive structures or spread to other organs. Therapy also avoids the surgical risk of inadvertently cutting through a nearby structure, such as the bowel, bladder, or even stomach (we have seen all of these).
No foreign objects are placed deep within your body. No stitches, staples, films, or meshes are inserted into the body. No cameras, gas, lights, surgical instruments, or contaminants enter the abdominal cavity from the ‘outside world.’
Side effects are mild, transient, or positive. The most common side effects patients report are temporary tenderness, aching, fatigue, and hip or back pain. When they occur, these symptoms pass with a 20-minute soak in Epsom salts or a compress in the evening of therapy. Other side effects cited in medical literature are positive. These include decreased intercourse pain, increased desire, arousal, lubrication, and orgasm (including first-time orgasms).
Verified success rates. Several peer-reviewed studies measure the ability of this therapy to decrease pain and increase fertility for women diagnosed with endometriosis. In a ten-year study with hundreds of participants, our fertility success rates for women with blocked tubes equaled or surpassed those of surgery. You may view all of our success rates by clicking here.
Improvements in other areas of the body. Because therapy focuses on detaching adhesions throughout the body, it is common for patients to report a significant increase in flexibility and range of motion after therapy. In addition, many report decreased pain and/or increased function in areas near the sites where they are being treated. Some report this phenomenon in areas they had forgotten or had not realized they were having a problem with, until therapy relieved the pain or tightness.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Risks and Challenges of Therapy
Therapists cannot visualize the adhesions. Initially, we deduce the likelihood of adhesions by conducting a thorough review of your history and symptoms. To gain further insights, we may request diagnostic tests or documentation from your physician. As well as treating the tubes and uterus, we palpate any areas where we note spasm, asymmetry, thickened tissues, or increased temperature. Because our therapists have been doing this work for an average of over 25 years each, they are experts at palpating the body.
Costs of therapy are generally a fraction of the cost of surgery; as with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage®️ is an out-of-network provider for your insurer.
Travel and time are considerations. Designed for local and out-of-town patients, therapy is given for 20 hours over a five-day period (e.g., Monday – Friday). It is provided by trained, certified therapists in several cities in the U.S. and the U.K.
No medical techniques have a 100% success rate. If we are unable to open your tubes, your chances of a successful IVF performed within 15 months after therapy increase by roughly 50%, per published studies. View our success rates.
Surgery to Open Fallopian Tubes
Description of surgery. The intent of surgery for hydrosalpinx is generally to remove the tube and sometimes to cut or burn the adhesions in the pelvis and abdomen. In a laparoscopy, the physician puts the patient under general anesthesia, then cuts several holes (ports) in the body. One of the ports is used to fill the cavity with a gas to separate the organs so that the surgeon can create a path through which s/he can visualize the structures s/he needs to remove or repair. Using the other ports, the doctor will insert a light, camera, and surgical instrument(s) with which they can cut or burn the tube to eliminate any blockage.Click here to view a surgery to open blocked fallopian tubes
When adhesions are extensive, the physician may elect to perform an open surgery called a laparotomy. In that surgery, the physician cuts the body open via a longer incision and may separate the sides with a metal retractor. Next, the surgeon enters with a scalpel, laser, or other surgical instrument to cut or burn any adhesions s/he may find. S/he will repair or cauterize any bleeding that occurs and will often check for other problems before exiting the body and sending the patient to a room for post-surgical recovery.
Advantages of Surgery
Direct visualization. The surgeon can directly see the area and visually assess the internal condition. In some cases, s/he may not be able to see through thick blankets of adhesions. This can lead to problems (inadvertent enterotomy), noted below.
Observe nearby areas. In addition to treating the adhered area, the physician can see and assess the condition of nearby structures, noting any areas that may be of concern.
Operative report. The doctor will dictate a report that describes what s/he observes and the procedures s/he performs during the surgery.
Surgical Risks and Challenges
Anesthesia complications. Recent studies have raised concerns about neurotoxicity, with mild to moderate brain damage, for patients who undergo one or more sessions of general anesthesia.
Inadvertent enterotomy. When a patient has significant adhesions, it can be difficult for the doctor to see the structures beneath them. Thus, a surgeon can unintentionally cut into a nearby healthy organ or other structure, called an inadvertent enterotomy (IE). An IE can cause serious problems or death. Authors from a study in the Journal of the Society of Laparoscopic Surgeons note:
“Death from IE is not uncommon.”
“IE in laparoscopic abdominal surgery is underreported”
“IE was the most common laparoscopic complication at our hospital.”
Hospitalization during recovery. Most surgeries are followed by a hospital stay, during which patient recovery can be monitored for post-surgical complications or infections.
New adhesions generally form after surgery. It is a well-accepted medical fact that nearly all surgeries in the abdomen or pelvis cause new adhesions to form. Thus, pain and adhesions can recur, sometimes worse than before the surgery to remove them.
Risks of laparoscopy include:
Hernia,
Infection,
Blood clots,
Adverse reactions to anesthesia,
Abdominal inflammation or infection,
Bleeding and the potential need for a blood transfusion,
Specific conditions that can increase your risk of complications during surgery include:
Stroke
Obesity
Diabetes
Smoking
Seizures
Drug allergies
High blood pressure
Obstructive sleep apnea
History of heavy alcohol use
History of adverse reactions to anesthesia
Medications, such as aspirin, that can increase bleeding
Other medical conditions involving your heart, lungs, or kidneys
Pre-Treatment Screening (Surgery and Therapy)
Screening every patient for appropriateness and contraindications before therapy or surgery is a necessary part of pre-treatment workup.
Screening before therapy. Clear Passage®️ directors and staff consult with applicants to review goals, risks, and potential benefits that they can expect from therapy. We conduct a thorough review of your history of healing events (prior surgery, trauma, infection, endometriosis, etc.) to determine if and where adhesions have likely formed and how they might be causing problems. In addition, we may require additional tests or correspondence from your physician before we can accept you for therapy.
Screening before surgery. Your surgeon should consult with you to review the goals, risks, and potential rewards you can expect from the procedure. They may order diagnostic tests to help rule out contraindications, such as active infection, and to help identify problem areas in the body that should be assessed during surgery.
Savaris, Ricardo & Giudice, Linda. (2007). The Influence of Hydrosalpinx on Markers of Endometrial Receptivity. Seminars in Reproductive Medicine. 25. 476-82. 10.1055/s-2007-991045.
Liakakos, T., Thomakos, N., Fine, P., Dervenis, C., & Young, R. (2001). Peritoneal adhesions: etiology, pathophysiology, and clinical significance. Recent advances in prevention and management. Dig Surg, 18(4), 206–273
Perousanksy, M. and Hemmings Jr, H.C. (2009). Neurotoxicity of General Anesthetics: Cause for Concern? Anesthesiology, 111(6), 1365-1371.
Binenbaum, S. & Goldfarb, M. (2006). Inadvertent enterotomy in minimally invasive abdominal surgery. Journal of the Society of Laparoendoscopic Surgeons, 10(3): 336-340
“After years of struggling with endometriosis pain and painful intercourse, I felt relieved to find a facility that would treat the root of my problems. Everyone was so professional, knowledgeable, and caring. Thank You!” – Rosie
Overview
The mechanical problems caused by endometrial implants are increased significantly by adhesions — internal scars that frequently form at endometrial sites throughout the body. Often bound to internal structures, endometrial tissues swell with each menstrual cycle. When this happens, the swelling can pull on the strong collagen fibers that comprise adhesions, causing pain or abdominopelvic dysfunction, including infertility. Unable to leave the body, endometriosis can spread or grow into additional areas of the body. Surgery is often recommended for women with endometriosis to remedy this problem or even diagnose it.
To avoid putting their patient through surgery, some gynecologists feel they can diagnose endometriosis from “signs and symptoms.” Others note that the only definitive diagnosis can be obtained by performing an exploratory surgery. This allows them to view the implants and stage the extent and severity of the endometriosis, from stage one to stage four.
Avoiding Surgery
The dual threat of adhesions that form at endometrial implants, coupled with post-surgical adhesions, has made some physicians and patients consider other methods to address these problems. Over the last two decades, a groundbreaking ‘all-natural’ treatment has been cited in medical literature for its ability to decrease the adhesions that form after surgery and at endometrial implants, without surgery or drugs.
While surgery under anesthesia marks a truly remarkable medical advance – one that saves lives daily, most surgical procedures come with risks. These include the formation of often powerful internal scars called adhesions. Acting like a glue in the body, adhesions can squeeze organs or bind internal structures together, sometimes causing severe pain or decreasing organ function.
In a mammoth 58-year study of medical literature, researchers found that surgery caused new adhesions to form in more than 90% of patients following major abdominal surgery and in 55-100% of women undergoing pelvic surgery.[iii] The study noted that “small-bowel obstruction, infertility, chronic abdominal and pelvic pain, and difficult re-operative surgery were the most common consequences of the adhesions.” Underlining the ongoing difficulty adhesions can cause, the study concluded, “Despite elaborate efforts to develop effective strategies to reduce or prevent adhesions, their formation remains a frequent occurrence after abdominal surgery.” Post-surgical adhesions are a major problem for physicians and patients alike.
Overview of Treatment Options
Clear Passage® Therapy to Decrease Endometrial Pain, Improve Function and Fertility
Over the last 20 years, numerous peer-reviewed studies and citations have cited a unique manual physical therapy (Clear Passage®) for its ability to help women with endometriosis, without the need for surgery. Medical studies show it has been effective at detaching the adhesive bonds that accompany endometriosis. The therapists focus on detaching the glue-like adhesive bonds that appear to be central to the structure of adhesions, and to much of the pain and infertility associated with endometriosis. Clinically, here is the process as we see it:
Two known facts are that:
Adhesions frequently accompany endometrial implants, and
Endometrial tissues swell each month, wherever they form.
After witnessing positive results treating endometriosis pain and infertility for over 30 years, we have surmised that the monthly swelling can pull on the adhesive bonds. When it does, it can cause significant pain or dysfunction to the underlying structures. The Clear Passage® Approach has been shown to decrease or eliminate the pain associated with menstrual cycles, apparently, by detaching these bonds from each other and the organs to which they attach. Additionally, the manual therapy has been shown to decrease pain and improve fertility at the same level and duration as surgery, but without creating post-surgical adhesions.
Description of the procedure. The Clear Passage® approach is a manual physical therapy; it is ‘all natural’ in that it is 100% ‘hands-on.’ While some patients describe CP as feeling like a very deep massage, others note that it can sometimes be much lighter, depending on the area and depth being treated. Highly trained physical therapists use their hands to deform and detach the tiny but powerful strands that comprise adhesions – similar to pulling out the strands of a nylon rope or pulling out the run of a 3-dimensional sweater. Therapists sometimes say it “feels like I’m pulling out taffy, in very slow motion.”
The therapy is very site-specific for adhesions and endometrial implants. Therapists certified to perform this work are experts at palpating and manipulating the soft tissues of the body, where endometrial implants and adhesions generally form. They use data from the patient’s history along with direct feedback from each patient during therapy. Each provider receives extensive training to provide the methods developed over 30 years to deform and detach the molecular/chemical bonds that bind endometrial implants to the underlying structures. In releasing those bonds, the body tends to return to an earlier state of pain-free mobility and function.
The usual protocol cited in the published studies consists of 20 hours of therapy spaced over five or more days. Patients often start therapy on Monday morning, receive four hours of therapy a day with a break for lunch, and are done Friday afternoon. Other than that, they are free to work, rest, or take a break from a busy lifestyle. Many women set aside these five days as a “special time to help their bodies heal.” Learn more and view a short video of Clear Passage® for endometriosis.
Advantages of Therapy
No hospitalization. Therapy is performed in a clean, private treatment room, one-on-one with a highly skilled physical therapist certified in the work. You are invited to bring a partner or family member along for company, if you like.
No anesthesia. While risks of anesthesia are small, they do exist. Our patients are awake and communicative during the procedure. We actively encourage patient involvement and feedback. In doing so, we invite each patient to be an active member of the team that is working hard to achieve their results. In addition, we provide education on the formation and deformation of adhesions anywhere in the body. We teach each patient self-treatment techniques she can use for her entire life, to help maintain pain-free function throughout life. This education and communication is not available to a person under anesthesia.
Decreased risk. Risk is minimal because there is no cutting or burning. There is no risk of forming post-surgical adhesions that can re-bind to the delicate reproductive structures or spread to other organs. Therapy also avoids the surgical risk of inadvertently cutting through a nearby structure, such as the bowel, bladder, or even stomach (we have seen all of these).
No foreign objects are placed deep within your body. No stitches, staples, films, or meshes are inserted into the body. No cameras, gas, lights, surgical instruments, or contaminants enter the abdominal cavity from the ‘outside world.’
Side effects are mild and transient. The most common side effects patients report are temporary tenderness, aching, fatigue, and hip or back pain. When they occur, these symptoms can generally be relieved with a 20-minute compress or bath in the evening after a treatment session.
Verified success rates. Several peer-reviewed studies measure the ability of this therapy to decrease pain and increase fertility for women diagnosed with endometriosis. In a ten-year study with hundreds of participants, our fertility success rates for women with endometriosis equaled those of surgery. You may view all of our success rates by clicking here.
Improvements in other areas of the body. Because therapy focuses on detaching adhesions throughout the body, it is common for patients to report significant increases in flexibility and range of motion after therapy. In addition, many report decreased pain and/or increased function in areas near the sites where they are being treated. Some report this phenomenon in areas they had forgotten or had not realized they were having a problem with, until therapy relieved the pain or tightness.
Full Reports: Major side effects documented in peer-reviewed studies, including increased desire, arousal, lubrication, and increased (or first-ever) orgasms, once the patient returns home.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Risks and Challenges of Therapy
Therapists cannot visualize the adhesions. Initially, we deduce the likelihood of adhesions by conducting a thorough review of your history and symptoms. To gain further insights, we may require diagnostic tests or documentation from your physician. We palpate the areas of your body related to your symptoms and other areas where we note spasm, asymmetry, thickened tissues, or increased temperature. Because our therapists have been doing manual therapy for most of their professional lives, they are experts at palpating and treating the body.
Costs of therapy are generally a fraction of the cost of surgery; as with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage® is an out-of-network provider for your insurer.
Travel and time are considerations. Designed for local and out-of-town patients, therapy is generally given for 20 hours over five days (e.g., Monday – Friday). It is provided by trained, certified therapists in several cities in the U.S. and the U.K.
Surgery to Remove Endometriosis and Adhesions
Description of endometriosis surgery. The intent of endometriosis surgery is to find and burn or surgically excise endometrial implants and adhesions. In a laparoscopy, the physician puts the patient under general anesthesia, then cuts several holes (ports) in the body. One of the ports is used to fill the cavity with a gas to separate the organs so that the surgeon can create a path through which s/he can visualize the structures s/he needs to remove or repair. Using the other ports, the doctor will insert a light, camera, and surgical instrument(s) with which they can see, then cut or burn adhesions and endometrial implants. You can observe a laparoscopy to decrease endometriosis by clicking here.
When adhesions are extensive, the physician may elect to perform an open surgery called a laparotomy. In that surgery, the physician cuts the body open via a much larger incision and may separate the sides with a metal retractor. Next, the surgeon enters with a scalpel, laser, or other surgical instrument to cut or burn any adhesions s/he may find. S/he will repair or cauterize any bleeding that occurs and will often check for other problems before exiting the body and sending the patient to a room for post-surgical recovery.
Advantages of Surgery
Direct visualization. The surgeon can directly see the area and visually assess the internal condition. In some cases, s/he may not be able to see through thick blankets of adhesions. This can lead to problems (inadvertent enterotomy), noted below.
Observe nearby areas. In addition to treating the adhered area, the physician can see and assess the condition of nearby structures, noting any areas that may be of concern.
Operative report. The doctor will dictate a report that describes what s/he observes and the procedures s/he performs during the surgery.
Surgical Risks and Challenges
Anesthesia complications. Recent studies note concerns about neurotoxicity, with mild to moderate brain damage for patients who undergo one or more sessions of general anesthesia.
Inadvertent enterotomy. When a patient has significant adhesions, it can be difficult for the doctor to see the structures beneath them. Thus, a surgeon can unintentionally cut into a nearby healthy organ or other structure, called an inadvertent enterotomy (IE). An IE can cause serious problems or death. Authors from a study in the Journal of the Society of Laparoscopic Surgeons note:
“Death from IE is not uncommon.”
“IE in laparoscopic abdominal surgery is underreported.”
“IE was the most common laparoscopic complication at our hospital.”
Hospitalization during recovery. Many surgeries are followed by a hospital stay during which the patient’s recovery can be monitored for post-surgical complications or infections.
New adhesions generally form after surgery. It is a well-accepted medical fact that nearly all surgeries in the abdomen or pelvis cause new adhesions to form. Thus, pain and adhesions can recur, sometimes worse than before the surgery to remove them.
There is no cure for endometriosis. In addition to post-surgical adhesions, endometriosis can and often does recur after surgery. Thus, surgery or therapy may need to be repeated. Some studies report that increased pain most frequently occurs in sites of prior surgery.
A note about surgical philosophies: The medical community has varied philosophies about the best surgical approaches to treat endometriosis and adhesions. While some are focused on doing the least damage possible, e.g., using lasers that burn just one cell deep, others feel they must cut deeply into an organ in order to fully remove endometrial implants. Before agreeing to a surgery, we encourage you to ask your surgeon his/her philosophy or surgical approach, to see if it aligns with your philosophy and goals.
Risks of laparoscopy include:
Hernia,
Infection,
Blood clots,
Adverse reactions to anesthesia,
Abdominal inflammation or infection,
Bleeding and the potential need for a blood transfusion,
Specific conditions that can increase your risk of complications during surgery include:
Stroke
Obesity
Diabetes
Smoking
Seizures
Drug allergies
High blood pressure
Obstructive sleep apnea
History of heavy alcohol use
History of adverse reactions to anesthesia
Medications, such as aspirin, that can increase bleeding
Other medical conditions involving your heart, lungs, or kidneys
Pre-Treatment Screening (Surgery and Therapy)
Screening every patient for appropriateness and contraindications before therapy or surgery is a necessary part of pre-treatment workup.
Screening before therapy. Clear Passage® directors and staff are available at no cost to consult with applicants to review goals, risks, and potential benefits that they can expect from therapy. We conduct a thorough review of your history of healing events (prior surgery, trauma, infection, endometriosis, etc.) to determine if and where adhesions have likely formed and how they might be causing problems. In addition, we may require additional tests or correspondence from your physician before we can accept you for therapy.
Screening before surgery. Your surgeon should consult with you to review the goals, risks, and potential rewards you can expect from the procedure. They may order diagnostic tests to help rule out contraindications, such as active infection, and to help identify problem areas in the body that should be assessed during surgery. It is reasonable to ask your doctor about the chance of post-surgical adhesions forming where s/he cut or burn.
Giudice LC, Kao LC. Endometriosis. Lancet. 2004;364(9447):789–799. doi: 10.1016/S0140-6736(04)17403-5
Counsellor VS. Endometriosis. A clinical and surgical review. Am J Obstet Gynecol. 1938;36:877
Liakakos, T., Thomakos, N., Fine, P., Dervenis, C., & Young, R. (2001). Peritoneal adhesions: etiology, pathophysiology, and clinical significance. Recent advances in prevention and management. Dig Surg, 18(4), 206–273
Perousanksy, M. and Hemmings Jr, H.C. (2009). Neurotoxicity of General Anesthetics: Cause for Concern? Anesthesiology, 111(6), 1365-1371.
Binenbaum, S. & Goldfarb, M. (2006). Inadvertent enterotomy in minimally invasive abdominal surgery. Journal of the Society of Laparoendoscopic Surgeons, 10(3): 336-340
Discover hope for adhesion-related pain and dysfunction with Clear Passage® Physical Therapy’s non-surgical, hands-on approach – Request Information and schedule your Free Consultation today to explore how our expert therapists can help you avoid surgery and improve your quality of life. To learn more about our innovative treatment methods and take the first step towards relief, visit our Apply to Therapy page.
“I want to express my gratitude to Clear Passage® Therapies for what you were able to do for me. The wonderful work you perform deserves recognition. I am a woman who has had four surgeries. For me, the surgery caused adhesions that became extremely painful. If it were not for Clear Passage® Physical Therapy, I would be contemplating another surgery for obstruction in my bowel caused by adhesions. I am hopeful that one day the medical doctors will prescribe this therapy to all patients who suffer from adhesions.” – Karyn
Suspected Adhesions. LaRues Story
Overview
Adhesions are internal scars that form wherever the body heals from tissue damage due to surgery, infection, inflammation, injury, radiation, or endometriosis. While adhesions are the first step in the healing process, they sometimes continue to grow in the body. They can create powerful glue-like bonds that can squeeze structures like straitjackets, decreasing their function or causing pain. Adhesions can attach organs, muscles, and other structures that are designed to be separate, decreasing their natural movement and function.
Because the body has no way to detach or eliminate them, adhesions tend to remain in place or grow over time. When their glue-like bonds wrap around structures or bind them to others, adhesions can cause significant problems. These problems may be deemed ‘unexplained’ because most adhesions cannot be seen on diagnostic tests (CT, MRI, X-ray, ultrasound).
Avoiding Surgery for Adhesion-Related Disorder (ARD)
Adhesions can become very serious, slowing or stopping the function of some of the body’s most important internal structures. Left untreated, they can prevent life when they block a woman’s fallopian tubes. When they form in the digestive tract, they can cause bloating, diarrhea, or constipation. In cases where they squeeze the intestines, they can end a person’s life by totally blocking the passage of food. Studies show how frequently adhesions form following surgery. Therefore, treating adhesions with surgery that will so often cause more adhesions seems counterproductive. Below, we have outlined and explained the advantages and disadvantages of two treatment options shown to be effective in decreasing adhesions: Clear Passage® Physical Therapy and Surgery.
Surgeries often cause more adhesions
Overview of Treatment Options
According to medical literature, there are only two known options to decrease adhesions in the body:
Clear Passage® Approach
Surgery
Therapy to Decrease Adhesions
Description of the procedure. The Clear Passage® Approach is a manual physical therapy that uses no drugs and no surgery. It has been cited in numerous peer-reviewed medical journals for its ability to decrease adhesions in the abdomen and pelvis. Some of the studies of its effectiveness include ‘before and after’ images and reports of individual patients, prepared by independent diagnostic physicians and published in reputable medical journals. Other studies examine larger groups; some compare our results to surgeries.
The therapy is ‘all natural’ in that it is 100% ‘hands-on.’ Patients describe it as often feeling like a very deep massage. The therapy can sometimes be much lighter, depending on the area and depth being treated. Clear Passage® therapists use their hands to locate adhered areas of the body related to the patient’s pain or symptoms. The therapist then transitions to very site-specific techniques to deform and detach the tiny strands that comprise adhesions. Therapy may be compared to pulling out the strands of a nylon rope or pulling out the run in a sweater. Our therapists describe it as feeling “like pulling out salt-water taffy, in very slow motion.”
Our therapists are experts at palpating and manipulating the soft tissues of the body, where adhesions generally form. They use data from the patient’s history, direct feedback from the patient during therapy, and a thorough training and understanding of methods developed over 30 years to locate adhesions. Then, they deform and detach the molecular/chemical bonds that are at their core. The usual protocol cited in the published studies consists of 20 hours of therapy, spaced over five or more days. You can view a short video of a Clear Passage® therapy session by clicking below.
Advantages of Therapy
No hospitalization. Therapy is always performed in a private treatment room, one-on-one with a highly skilled therapist certified in the work. Patients may bring a partner or family member along for company, if they like.
No anesthesia. The patient is awake and communicative during the entire procedure. Patient involvement is encouraged, with the patient invited to give feedback throughout the course of therapy.
Decreased risk. Risk is minimal. There is no cutting or burning, no risks associated with anesthesia, and no risk of inadvertently cutting through a nearby organ or other structure.
No foreign bodies are introduced. No staples, stitches, films, or meshes are inserted into the body. No cameras, gas, lights, or surgical instruments enter the body.
Side effects are mild and transient. The most common side effects reported with therapy are temporary tenderness, aching, fatigue, and hip or back pain. When they occur, these symptoms pass within a few days.
Improvements in other areas of the body. Because therapy focuses on detaching adhesions throughout the body, patients often report increases in flexibility and range of motion after therapy. Many report decreased pain and/or increased function in areas near the site where they are being treated or even in distant areas. This pain reduction is often noted in the lower back, due to the freeing of abdominal adhesions that were restricting the front of the lumbar vertebrae. Some report improvements in areas where they had forgotten or had not realized they were having a problem, until therapy relieved the pain or tightness.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Don’t Let the Cost Keep You From Finding Out If Clear Passage® Can Help
You’ve probably already spent money on doctor visits, tests, medications, procedures, and treatments that didn’t give you the answer you were hoping for. The last thing you need is to finally find a treatment worth exploring and then have the cost stop you in your tracks.
Therapists cannot visualize the adhesions. Initially, we deduce the likelihood of adhesions by conducting a thorough review of each patient’s history and symptoms. To gain further insights, we may require diagnostic tests or documentation from the patient’s physician. During therapy, we palpate the areas of your body related to your symptoms and other areas where we note scarring, tightness, spasm, or increased temperature. Because our therapists have been practicing manual therapy for their entire professional lives, they are experts at palpating the body.
Costs of therapy are generally a fraction of the cost of surgery; as with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage® is an out-of-network provider for your insurer. In weighing costs, many patients take into account the cost to their quality of life vs. the cost of living with adhesions.
Travel and time are considerations. Therapy generally takes five days (e.g., Monday – Friday); it is only provided by trained, certified therapists in several cities in the U.S. and U.K. The 5-day program is designed for out-of-town and out-of-country patients. We suggest that patients with a history of bowel obstructions remain in town for an extra day before returning home, to allow the body to return to homeostasis before undergoing the changes in air pressure that can accompany an airline flight.
Surgery to Decrease Abdominopelvic Adhesions
Description of common procedures. The intent of adhesiolysis surgery is to cut or burn adhesions with the goal of returning the body to an earlier state of mobility and function. In a laparoscopy, the physician puts the patient under general anesthesia, then cuts several holes (ports) in the body. The ports serve several functions. One is used by the physician to fill the abdominal cavity with gas to separate the organs. This separation allows the surgeon to see where s/he can insert surgical instruments and access the adhesions. Using the other ports, the doctor will insert a light, camera, and surgical instrument(s), which they can use to burn or cut adhesions that they see. You can observe a laparoscopy to decrease adhesions by clicking here.
When adhesions are extensive, the physician may elect to perform an open surgery called a laparotomy. In that surgery, the body is cut open with a scalpel, with the sides generally separated with a metal retractor. Next, the physician enters with a scalpel, laser, or other surgical instrument to cut or burn any adhesions s/he may find. S/he will repair or cauterize any bleeding that occurs, and may check the area for other problems before exiting the body, closing it with stitches, and sending the patient to a room where staff can monitor the patient’s recovery.
Advantages of Surgery
Direct visualization. It is a significant advantage that the surgeon can directly see and burn or cut adhesions that do not appear on diagnostic tests such as MRI or CT Scan. Complications can occur in patients with significant adhesions if the doctor has difficulty seeing through the layers s/he are cutting through (see below).
Observe nearby areas. In addition to treating the adhered area, the physician can see nearby structures, noting any additional areas that may be of concern.
Operative report. The doctor can film the surgery and dictate a report describing what s/he observes and the procedures s/he performs during the surgery.
Disadvantages: Surgical Risks and Challenges
Anesthesia complications. Recent studies note concerns about mild to moderate brain damage for patients who undergo one or more sessions of general anesthesia. (Perousakis & Hemmings, 2009)
Inadvertent enterotomy. When a patient has significant adhesions, it can be difficult for the doctor to see the structures beneath them. Thus, a surgeon can unintentionally cut into a nearby healthy organ or other structure, called an inadvertent enterotomy (IE). An IE can cause serious problems or death. In a study from the Journal of the Society of Laparoscopic Surgeons, the authors note that:
“IE in laparoscopic abdominal surgery is underreported.”
Hospitalization during recovery. Most patients must undergo a hospital stay after adhesion-related abdominal or pelvic surgery. During this time, hospital staff will monitor the patient to ensure their recovery and to avoid post-surgical complications or infections.
New adhesions generally form after surgery. According to a 50+ year review of abdominal and pelvic surgery in the U.S., nearly all abdominal and pelvic surgeries cause new adhesions to form. Thus, adhesions can recur – sometimes worse than before the surgery to remove them. The study notes that adhesions form after 55% to 100% of pelvic surgeries and after 90% of major abdominal surgeries.
Pre-Treatment Screening (Surgery and Therapy)
Therapy and surgery both require patients to be screened for appropriateness and contraindications before treatment.
Screening before therapy. Before we accept you for therapy, our staff will conduct a thorough review of your history of healing events (prior surgery, injury, infection, endometriosis, etc.) to determine if and where adhesions have likely formed and how they might be causing problems. We then consult with you to review goals, risks, and potential benefits you can expect.
We want you to do well and to have a reasonable chance of reaching your goals. We will accept you for therapy if we feel we can help you. Similarly, we will alert you if we have concerns that you will not do well with therapy; we will not accept you if we feel that you will not have a favorable outcome. Screening before surgery. Before surgery, physicians may order diagnostic tests to help rule out contraindications such as active infection and to help identify problem areas in the body that should be assessed during surgery. Your doctor should advise you of the goals of surgery, along with the risks and potential rewards you can expect. It is likely a good idea to ask your physician about the chance of developing post-surgical adhesions with the need for one or more additional surgeries.
“After years of incapacitating back problems, I have now received my first 12 hours of treatment at Clear Passage®. I am amazed that I feel physically so much better, in such a short time. It is remarkable to me that I can now bend over, virtually pain-free, for the first time in 14 years! Had I come here sooner, I would have saved myself so many years of pain and misery! Thank you so much.” – Midge
Overview
When diagnostic tests fail to show a cause of your pain, physicians who suspect a mechanical cause (e.g., adhesions, endometriosis) may suggest an exploratory surgery, hoping that the doctor can see and treat the cause of the pain or dysfunction.
Once medical and hormonal conditions have been ruled out, the pain or dysfunction is often thought to be mechanical in nature. If diagnostic images from X-ray, MRI, CT, or ultrasound fail to show a cause, physicians tend to suspect that adhesions, internal scars that bind structures together, are causing the pain.
Treatment of adhesions that cause ‘unexplained pain’ can be conducted via surgery or a non‑surgical technique, the Clear Passage® Approach. Below, we compare and contrast these two approaches for treating unexplained pain with suspected adhesions.
Avoiding Surgery
Adhesions in the abdomen or pelvis can become very serious, slowing or stopping the function of some of the body’s most important internal structures. Left untreated, they can cause or contribute to female infertility or end a person’s life by blocking the passage of food through the intestines. These adhesions generally lead to intense, debilitating pain by binding to strictures in the body with a pull that is exacerbated and provoked by inflammation. Surgery inevitably leads to more adhesions, making surgery a less-than-ideal treatment in many cases.
Overview of Treatment Options
According to medical literature, adhesions in the abdomen or pelvis can be addressed in two distinctly different ways:
The Clear Passage® Approach
Drugs and/or Surgery
Clear Passage® Therapy to Decrease Adhesions
Description of the procedure. The Clear Passage® Approach is a manual physical therapy that uses no drugs or surgery. It has been cited in numerous studies and peer-reviewed medical journals for its ability to decrease adhesions. The studies show effectiveness with numerous types of pain and dysfunction caused by adhesions. “Before and after” studies by independent diagnostic physicians are included within some of the published studies.
Chronic inflammation within the bowel/intestines is a major cause of adhesions and chronic abdominal pain.
The therapy is ‘all natural’ in that it is 100% ‘hands-on.’ Patients describe it as feeling like a very deep massage. At times, the therapy can be much lighter, depending on the area and depth being treated. Physical therapists use their hands to find adhered areas. Then, they work to deform and detach the tiny strands that comprise adhesions – similar to pulling out the strands of a nylon rope or pulling out the run in a sweater. They describe it as “pulling out salt-water taffy, in very slow motion.”
The therapy is site-specific for treating the adhered area. The therapists are experts at palpating and manipulating the soft tissues of the body, where adhesions often form. They use data from the patient’s history, direct feedback from the patient during therapy, and thorough training and understanding of methods developed over 30 years to deform and detach the molecular/chemical bonds called cross-links that are at the core of adhesions. The usual protocol, cited in the studies, consists of 20 hours of therapy over the course of five days. You can view a short video of a Clear Passage® therapy session by clicking below.
Advantages of Therapy
No hospitalization. Therapy is performed in a private treatment room, one-on-one with a highly skilled therapist certified in the work. Patients are invited to bring a partner or family member along for company, if they like.
No anesthesia. The patient is awake and communicative during the procedure. Patient involvement is encouraged, with the patient invited to give feedback throughout the course of therapy.
Decreased risk. Risk is minimal. There is no cutting, no burning, no risk of side effects from anesthesia or medications, and no risk of inadvertently cutting through a nearby organ or other structure.
No foreign bodies are introduced. No staples, stitches, films, or meshes are inserted into the body. No cameras, gas, lights, or surgical instruments enter the body.
Side effects are mild and transient. The most common side effects reported with therapy are temporary tenderness, aching, fatigue, and hip or back pain. When they occur, these symptoms pass within a few days.
Improvements in other areas of the body. Because therapy focuses on detaching adhesions throughout the body, patients regularly report significant increases in flexibility and range of motion after therapy. Many report decreased pain and/or increased function in areas near the site where they are being treated. Some report this in areas where they had forgotten or had not realized they were having a problem until therapy relieved the pain or tightness.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Disadvantages: Risks and Challenges of Therapy
Therapists cannot visualize the adhesions. Initially, we deduce the likelihood of adhesions by conducting a thorough review of your history and symptoms. To gain further insights, we may require diagnostic tests or documentation from your physician. During therapy, we palpate the areas of your body related to your symptoms and other areas where we note spasm, tightness, or increased temperature. Because our therapists are skilled professionals who have been practicing manual therapy for most of their professional lives, they are experts at palpating the body.
Costs of therapy are generally a fraction of the cost of surgery; as with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage® is an out-of-network provider for your insurer.
Travel and time are considerations. Therapy generally takes five days (e.g., Monday – Friday); it is only provided by trained, certified therapists in several cities in the U.S. and U.K. The 5-day program is designed for out-of-town and out-of-country patients. Most patients fly in on the weekend, start therapy Monday morning, and are done Friday afternoon.
Surgery to Decrease Abdominopelvic Adhesions
Description of common procedures. The intent of adhesiolysis surgery is to cut or burn adhesions to help return the body to an earlier state of mobility and function. In a laparoscopy, the physician puts the patient under general anesthesia, then makes several openings (ports) in the body. These ports serve several functions. One is used to fill the cavity with a gas to help separate the organs so the surgeon can create a space in which to insert surgical instruments to access the adhesions. Using the other ports, the doctor will insert a light, generally a camera, and the surgical instrument(s) with which they can cut or burn adhesions that they see. You can observe a laparoscopy to decrease adhesions by clicking here.
When adhesions are extensive, the physician may elect to perform an open surgery called a laparotomy. In that surgery, the body is cut open with a scalpel, and the sides may be separated with a metal retractor. Next, the physician enters with a scalpel, laser, or other surgical instrument to cut or burn any adhesions s/he may find. S/he will repair or cauterize any bleeding that occurs, and may check the area for other problems before exiting the body, stitching and/or stapling it shut, and sending the patient to a room where staff can monitor the patient’s recovery.
Advantages of Surgery
Direct visualization. The surgeon’s ability to directly see, then cut or burn adhesions, is a major advantage.
Observe nearby areas. In addition to treating the adhered area, the physician can visualize nearby structures and assess their health and condition, noting any additional areas that may be of concern.
Operative report. The doctor will dictate a report that describes what s/he observes and the procedures s/he performed during the surgery.
Pre-Treatment Screening (Surgery and Therapy)
Both therapy and surgery require patients to be screened for appropriateness and contraindications before treatment.
Screening before therapy. Before therapy, Clear Passage® directors consult applicants to review goals, risks, and potential benefits they can expect. We conduct a thorough review of the applicant’s history of healing events (prior surgery, trauma, infection, endometriosis, etc.) to determine if and where adhesions have likely formed, and the problems they may be causing.
We screen applicants for two reasons:
To determine the likelihood that we can help an applicant reach his/her goal,
To rule out contraindications that could decrease the effectiveness of therapy or cause problems.
Screening before surgery. Before surgery, physicians consult patients to review the goals, risks, and potential benefits they can expect from the procedure. They may order diagnostic tests to help rule out contraindications, such as active infection, and to help identify problem areas in the body that should be assessed during surgery. It is reasonable to ask your doctor about the likelihood of new adhesion formation after surgery.
Disadvantages: Surgical Risks and Challenges
Anesthesia complications. Recent studies note concerns about mild to moderate brain damage for patients who undergo one or more sessions of general anesthesia. (Perousakis & Hemmings, 2009)
Inadvertent enterotomy. When a patient has significant adhesions, it can be difficult for the doctor to see the structures beneath them. Thus, a surgeon can unintentionally cut into a nearby healthy organ or other structure, called an inadvertent enterotomy (IE). An IE can cause serious problems or death. In a study from the Journal of the Society of Laparoscopic Surgeons, the authors note that:
“IE in laparoscopic abdominal surgery is underreported.”
“Death from IE is not uncommon.”
“IE was the most common laparoscopic complication at our hospital.” (Binenbaum & Goldfarb, 2006)
Hospitalization during recovery. Most patients must undergo a hospital stay after any abdominal or pelvic surgery. Patients are monitored to ensure their recovery and that there are no immediate post-surgical complications or infections.
New adhesions generally form after surgery. Data compiled from over 50 years of abdominal and pelvic surgeries shows that nearly all surgeries cause new adhesions to form. Thus, despite the skills of the finest surgeon, adhesions often recur, sometimes worse than before the surgery to remove them. Because surgeries cause adhesions, some of our patients feel stuck in an unending cycle of adhesions-surgery-pain-adhesions-pain-adhesions.
Pre-Treatment Screening (Surgery and Therapy)
Both therapy and surgery require patients to be screened for appropriateness and contraindications before treatment.
Screening before therapy. Before therapy, Clear Passage® directors consult applicants to review goals, risks, and potential benefits they can expect. We conduct a thorough review of the applicant’s history of healing events (prior surgery, trauma, infection, endometriosis, etc.) to determine if and where adhesions have likely formed, and the problems they may be causing.
We screen applicants for two reasons:
To determine the likelihood that we can help an applicant reach his/her goal,
To rule out contraindications that could decrease the effectiveness of therapy or cause problems.
Screening before surgery. Before surgery, physicians consult patients to review the goals, risks, and potential benefits they can expect from the procedure. They may order diagnostic tests to help rule out contraindications, such as active infection, and to help identify problem areas in the body that should be assessed during surgery. It is reasonable to ask your doctor about the likelihood of new adhesion formation after surgery.