Digestion problems can disrupt your everyday routine and negatively impact your quality of life. If standard treatments have failed to provide relief, you may be dealing with a more serious underlying problem, such as blocked intestines or small bowel obstructions (SBO). This is even more likely if your symptoms include vomiting, painful bowel movements, or stringy poop. Read on to learn more about the symptoms associated with intestinal obstruction and what to do if you suspect you have SBO.
Are You Experiencing Common Bowel Problems or Intestinal Blockage?
Gastrointestinal problems such as acid reflux, gluten sensitivity, irritable bowel syndrome, hemorrhoids, and the like are pretty common. Physicians usually advise people with common bowel problems to drink more water, eat more fiber, and get more exercise. They may recommend laxatives, probiotics, and supplements – or they may prescribe medications.
On the other hand, blocked small intestines can be overlooked because it is less common. More severe gastrointestinal problems are more regularly misdiagnosed. These include:
Appendicitis
Perforated or ruptured organs
Inflammatory bowel diseases
Cancer, bleeding
Blockage of blood flow
Seven Symptoms of Intestinal Blockage
How do you know whether you have a common bowel problem or whether your small intestines are blocked because of your gastrointestinal disorder?
Bowel obstructions cause these symptoms:
No bowel sounds:
The absence of bowel sounds indicates underactive or inactive intestines. This means that waste is not being eliminated from the body on time. A buildup in your gastrointestinal tract can result in a life-threatening rupture.
Nausea and vomiting:
Food and liquids that should be moving forward are moving backward. If this happens often enough, other problems, such as ulcers, gastritis, and gastroesophageal reflux disease (GERD), may be present.
Stomach cramps:
These are pains that may come and go.
Diarrhea:
If the bowel is partially blocked, diarrhea may occur.
Swelling or bloating (distention):
Liquids and gases can build up in the abdomen.
Pain or tenderness:
The pain is often around or just below the belly button, but can be present in other areas.
Constipation and the inability to pass gas:
If the bowel is completely blocked, no material passes.
These are signs of a complete blockage, called a total bowel obstruction.
Severe abdominal pain, persistent bloating, nausea, and the inability to pass gas or stool can be a sign of blocked bowel that should be evaluated by a medical professional as soon as possible.
Traditional Small Bowel Obstruction Treatment Options
People with blocked intestines may have to be hospitalized to stabilize their condition. Nonsurgical treatment for intestinal blockage includes:
An IV to replenish fluids
Introduction of analgesics to relieve pain
Liquid nutrition.
Physicians may introduce a nasogastric tube (NG) to help empty the stomach to reduce swelling in the abdomen.
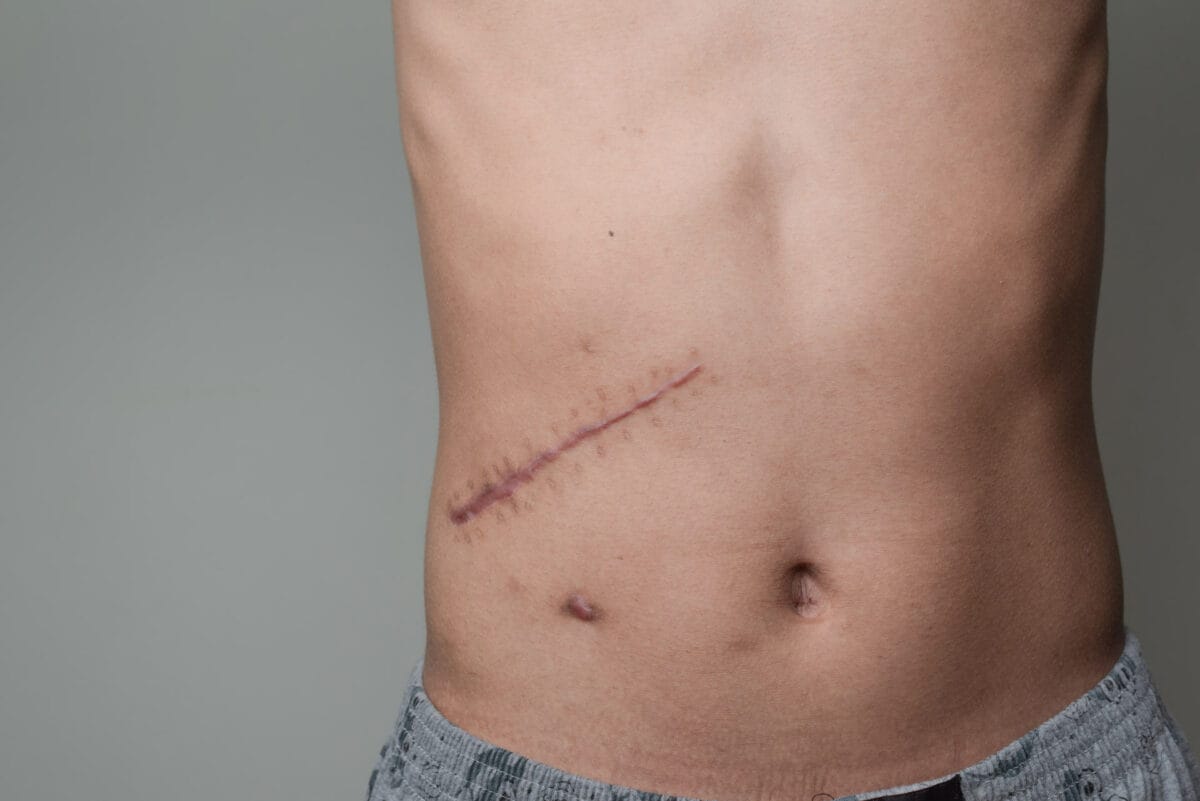
If conservative treatments do not resolve the situation or if repeated obstructions occur, surgery may be performed to remove the block along with any damaged tissue. However, bowel obstruction surgery can create even more scar tissue that can increase the likelihood of future bowel obstructions.
The Best Nonsurgical Treatment for Intestinal Blockage
What if you didn’t have to go to surgery, and the nonsurgical treatment was successful? You’re in luck. Because blocked intestines can be caused by abdominal adhesions (bands of scar-like tissue that attach to organs, muscles, and other structures), they can be dissolved!
Fortunately, there is an effective non-invasive treatment for abdominal adhesions called the Wurn Technique®. It is a manual adhesion release physical therapy shown to reduce adhesions and significantly improve SBO symptoms without surgery.
With this method, highly trained and skilled therapists use their hands to detach adhesions, barrier by barrier. In doing so, they break down the adhesions and restrictions that have been created over a lifetime of healing from inflammation, infection, trauma, and abdominal or pelvic surgery. These Wurn Technique® therapists apply pressure in very site-specific affected areas. This pressure is titrated (slowly adapted) to reduce the adhesions formed in the body over time and return the intestines to normal mobility, tone, and function. When asked how they feel 90 days after treatment, patients have overwhelmingly reported improved quality of life.
You May Need to Advocate for Yourself
Unfortunately, many physicians are either unaware of manual adhesion release small bowel obstruction physical therapy or have not taken the time to review results and are therefore not yet convinced of its effectiveness.
If you experience severe abdominal pain or other bowel obstruction symptoms, you should seek immediate medical care. The highly trained therapists at Clear Passage® can act independently or as an extension of your physician’s care.
Either way, Clear Passage® therapists will screen you thoroughly for contraindications and provide your physician with an extensive Initial Evaluation and Discharge Summary.
Patients often describe Clear Passage® therapy as a profound relief, saying it is “something my body has needed for a long time.” Their therapists often hear, “You have found the area I’ve been telling my doctor(s) about for years – but they couldn’t find anything.”
To avoid repeated hospitalizations and/or surgery, contact Clear Passage® for treatment. Clinical research has quantified and validated Clear Passage® results published in some of the world’s top medical journals.
WE’RE OPEN: Clear Passage® clinics are open and receiving patients. Staff and therapists follow CDC guidelines and safety procedures to ensure everyone’s health and well-being, while providing world-class care and life-saving treatment.
Welcome!
Our quarterly newsletters bring you event announcements, exciting news, and helpful resources.
Our researchers and physical therapists have studied the internal scars called adhesions for over 30 years. Where we can, we will share insights from several decades of experience in this area.
This forum is a place for anyone interested in this subject to ask questions that we (or others) may be able to answer accurately – preferably with medically or scientifically verifiable facts.
We are not here to promote our services or anyone else’s. We invite members to share their experiences with providers – or anything that has helped them (food, drink, exercise, supplement, etc.) We are not interested in second-hand accounts (e.g., my friend told me she followed a regimen of [blank] and did well). We support first-hand accounts and published scientific data.
FEMALE INFERTILITY FORUM
If you or someone you know is struggling with infertility, please feel free to stop by and speak with others going through the same thing. You can join by following this link: https://www.facebook.com/groups/naturalinfertility
ENDO AWARENESS MONTH IS OVER, ENDO IS NOT: PREVIOUS PATIENT SUCCESS STORY
Six Years of Infertility and Stage IV Endometriosis-Liz’s Story
When I was 24 years old, I was diagnosed with stage IV endometriosis. After I underwent surgery, my pain increased in severity and frequency.
Two years later, I married my long-time boyfriend, and we planned to have a perfect family. Because of my complications with endometriosis, I sought help from a fertility specialist and underwent another laparoscopic surgery. The surgeon drained a cyst, removed any endometriosis she found, and removed a stapled sac that was attached to the left ovary from my previous surgery.
Although the surgeon was optimistic that my endometriosis pain would be reduced, she told my husband and me we had a 1% chance of conceiving naturally. I was heartbroken; words cannot express the pain I endured at that moment.
I prayed for a miracle or a sign of hope. Then, I received a phone call from my sister. On her local news, there was a feature about a manual physical therapy treatment that could help women with endometriosis and infertility.
My husband was skeptical at first, but I needed to try it out. I immediately called and received a packet of information about the therapy. What we read made sense to us, so my husband and I decided to sign me up for the treatment. We packed our bags and headed to Florida.
The rest is history. Ten days after the treatment and six years of battling infertility, I was pregnant! My husband and I were so shocked that we had to administer the pregnancy test three times to be sure.
I had a full-term pregnancy and gave birth to our beautiful baby boy. My son will be four at the end of this month, and we also have another addition to the family. I was able to conceive another baby three years later. She is almost a year old now. When we look at our children’s faces and into their eyes, we are still amazed by our little miracles.
ENDOMETRIOSIS PATIENT TESTIMONIALS
Adhesions frequently accompany endometrial implants. When these tissues swell each month, the pull of adhesions can restrict normal function and cause pain and infertility.
The Clear Passage® Approach focuses on detaching these adhesions. After we release them, the endometrial tissue can swell and shrink freely without causing pain and discomfort.
Clear Passage® Therapies was recently featured in several podcasts. Larry and Belinda Wurn had the pleasure of discussing their journey from developing their technique for relieving Belinda’s pain to treating infertility and endometriosis patients. To listen, navigate to each podcast episode using the links below.
To see published studies on Clear Passage®’s effectiveness with endometriosis, infertility, SIBO, Crohn’s, chronic pain, and bowel obstructions, go to our published studies.
Clear Passage® Physical Therapy has remained open over the course of the COVID-19 pandemic. As vaccinations are being distributed, we are noticing a decline in COVID-19 cases throughout the state of Florida. Many of our clinic staff have been vaccinated as well. In Gainesville, where our main clinic is located, we currently have very few COVID cases.
Many patients continue to drive or fly to Gainesville or US locations. Those who live near London or New York find that those clinics are easily accessible. Once in a Clear Passage® clinic, you can be assured that we are taking the proper steps to ensure patient safety.
One advantage for Clear Passage® patients is that we typically treat very few patients each week. Even in our Gainesville, Florida headquarters, we generally treat a maximum of three patients a week. Thus, your exposure to any potential threat is much lower than at most health clinics in the USA or UK. Additionally, you have been reserved a room for your treatment; that room is disinfected and sanitized twice daily. Our staff takes all precautions to ensure a safe and healthy treatment.
Florida clinic: Flying directly to the Gainesville airport may give you a greater comfort level than flying into Jacksonville, Orlando, or Tampa (which are up to 2 hours away from our clinic). Once patients arrive, many choose to stay in a private rental home. You can order food delivered and even order food before you arrive. The grocery stores here are not crowded, and the positive cases here are significantly lower than elsewhere.
Rent a car to take advantage of the numerous uncrowded outdoor sites. In Gainesville, the 400‑acre Kanahapa Botanical Gardens has beautiful topography with lakes. It is filled with plants and flowers from all over the world. After a day of therapy, a one-hour drive to Cedar Key treats you to sunset over the Gulf of Mexico. Staying in a private home is a bit like staying at your own home, interspersed with visits to a safe, clean clinic in which you are probably the only patient you are going to see.
Thus, making a determination of whether to save your life, restore your quality of life, or return fertility need not be a scary decision. Feel free to call us for more information; we look forward to helping you heal.
STAFF PICK: FAVORITE SPRINGTIME ACTIVITY
We understand that many people have been affected by the COVID-19 pandemic. Stress can take a toll on the body and even create adhesions, leading to chronic pain – especially in the neck and back. Our staff chimed in with some activities that decrease stress and get them outside and active!
Larry: “Relaxing and breathing deeply while lying on my back in the grass, looking up at the clouds (in the daytime) and at the stars (at night)!”
Belinda: “Visit somewhere new, read a new book, and take wildlife photos.”
Autumn: “Having picnics in the park with my daughter and friends!”
Brenda: “I enjoy gardening in the spring, and making time to be outside in the sunshine.”
Julie: “Riding my bicycle and paddle boarding!”
Lidia: “Spring Cleaning. Well, the general concept is more enjoyable to me than the activity, but it’s necessary.”
Kristen: “I always enjoy visiting a local blueberry farm to pick fresh blueberries with my family on a beautiful spring day!”
Jessica: “My family enjoys planting new flowers and getting our yard looking pretty!”
However you choose to enjoy springtime, remember to follow CDC guidelines for safety and health. The best way to get through this pandemic is by working together. Wear a mask, social distance, and hang in there!
About Us
Clear Passage® Physical Therapy is a network of physical therapy clinics in the US and UK. Our clinicians have been highly trained to provide a non-surgical, drug-free treatment that has been shown to decrease adhesions in the body that cause chronic pain, female infertility, life-threatening bowel obstructions, and contribute to SIBO (Small Intestinal Bacterial Overgrowth).
Our clinics are the home of the Clear Passage® Approach, a unique hands-on physical therapy protocol developed over 30+ years of extensive study and clinical research by Belinda Wurn, PT, and Larry Wurn, LMT.
Small bowel obstruction creates major challenges for physicians and their patients. While a total small bowel obstruction is life-threatening and must often be dealt with surgically, it is an accepted fact that surgery is the number one cause of recurring bowel obstructions. Thus, the last resort medical treatment for small bowel obstruction is also the primary cause of future obstructions, underlining the need for a non-surgical treatment that can break this vicious cycle.
Many people who have undergone surgery or infection in the abdomen undergo recurring “partial small bowel obstructions” due to internal adhesions that squeeze or kink the intestines. In these cases, food may finally pass, often aided by a hospital visit. The hospitalization generally includes the insertion of a nasogastric (NG) tube through the nose into the stomach. Hospital staff will turn on an electric pump designed to constantly empty the stomach contents and relieve pressure on the digestive tract. The physician will often insert intravenous lines to introduce fluids for hydration or narcotic pain relief, in an attempt to relax and hydrate the bowel, so that food will pass. Similar intravenous lines will provide nutrition since the bowels no longer work. Patients describe the experience as a scary, uncomfortable, and harrowing experience that can take many hours or days to clear.
After a partial bowel obstruction, the patient’s ongoing concern is that despite the obstruction clearing, nothing has structurally changed. The patient is sent home with the advice, “This may and probably will happen again.” Thus, many patients feel as if they are living with a time bomb in their gut, concerned with what they can eat, what social or work activities they can and cannot do, whether they can travel, etc. By far, their greatest fear is “What happens next time – if the obstruction does not clear?”
Treating the adhesions that cause recurring bowel obstructions without surgery is considered a major advance. Our manual (hands-on) physical therapy has been shown to greatly improve quality of life and significantly decrease the incidence of small bowel obstruction in patients who receive the therapy. To date, we know of no other non-surgical treatment actually shown to clear adhesions that obstruct the bowel.
Break free from the cycle of recurrent small bowel obstructions and regain control of your life with Clear Passage® Physical Therapy’s Free Consult and Request Info – discover their groundbreaking, non-surgical approach that has been clinically proven to reduce adhesions, decrease pain, and significantly improve quality of life for patients suffering from this debilitating condition. To learn more, visit our Apply to Therapy page.
Treatment Options For Recurrent Bowel Obstructions
Clear Passage®️ Therapy to Decrease Adhesions
Description of the procedure. The Clear Passage® approach is a manual physical therapy that uses no drugs and no surgery. It has been cited in peer-reviewed medical texts and journals for its ability to decrease adhesions in the abdomen and pelvis, non-surgically. Some of the published studies include ‘before and after’ images and reports of individual patients prepared by independent diagnostic physicians. Others examine the effects of the therapy on treating adhesions for conditions, including recurring small bowel obstruction. Some studies show that the results of the therapy equal or exceed the results of surgery for improving structure and function.
The therapy is ‘all natural’ in that it is 100 percent ‘hands-on.’ Many patients describe it as feeling like a very deep massage. Our physical therapists use their hands to locate adhered areas of the body related to the patient’s pain or symptoms. They then transition to very site-specific techniques to deform and detach the tiny strands that comprise adhesions. Therapy may be compared to pulling out the strands of a nylon rope or pulling out the run in a sweater. Our therapists describe it as feeling like “pulling out salt-water taffy, in very slow motion.”
Our therapists are experts at palpating and manipulating the abdomen and pelvis, where bowel adhesions cause problems. They use data from each patient’s history and direct feedback from the patient during therapy, along with training and understanding of methods developed over 30 years to locate and detach adhesions. The protocol cited in the studies consists of 20 hours of therapy, spaced over five or more days. View a short video of what Clear Passage®️ therapy is like.
Advantages of Therapy
No hospitalization. Therapy is always performed in a private treatment room, one-on-one with a highly skilled therapist certified in the work. Patients may bring a partner or family member along for company, if they like.
No anesthesia. Without general anesthesia, there is no risk of neurotoxicity to the brain or other areas of the body. The patient is not only awake and communicative during the procedure, but we also encourage patient involvement; each patient is invited to give feedback throughout the course of therapy. We feel that involving each patient in their care and soliciting their feedback during each therapy session generates better results.
Decreased risk. Risk is minimal. There is no cutting or burning, no risk from anesthesia, and no risk of inadvertently cutting through a nearby organ or other structure.
No foreign bodies are introduced. No staples, stitches, films, or meshes are inserted into the body. No cameras, gas, lights, or surgical instruments enter the body.
Side effects are mild and transient. The most common side effects reported with therapy are temporary tenderness, aching, fatigue, and hip or back pain. Temporary soreness is generally relieved with a 20-minute Epsom salt bath or compress in the evening.
Improvements in other areas of the body. Because therapy focuses on detaching strong adhesions that tend to form in various areas of the body, most patients report increases in flexibility and range of motion after therapy. Many report decreased pain and/or increased function in areas near the site where they are being treated – or even at distal sites. This pain reduction is often noted in the low back due to the freeing of abdominal adhesions from the front of the lumbar vertebrae. Some patients report improvements in areas where they had forgotten or had not realized they were having a problem, until therapy relieved the pain or tightness.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Disadvantages: Risks and Challenges of Therapy
Therapists cannot visualize the adhesions. Initially, we deduce the likelihood of adhesions by conducting a thorough review of each patient’s history and symptoms. To gain further insights, we may require diagnostic tests or documentation from your physician. During therapy, we palpate the areas of your body related to your symptoms and other areas where we note scarring, tightness, spasm, or increased temperature. Because our therapists have been practicing manual therapy for most of their professional lives, they are experts at palpating and treating the body.
Costs of therapy are generally a fraction of the cost of surgery. As with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage®️ is an out-of-network provider for your insurer. When considering the costs, we encourage patients to measure the cost of their quality of life and peace of mind vs. the sacrifices they make due to living with adhesions. Download our Insurance PDF to send to your insurance.
Travel and time are considerations. Therapy generally takes five days (e.g., Monday – Friday); it is only provided by trained, certified therapists in several cities in the U.S. and U.K. The 5-day program is designed for out-of-town and out-of-country patients. We suggest that patients with a history of bowel obstructions remain in town for an extra day before returning home. The goal is to allow the body to return to homeostasis before undergoing changes in bowel air pressure that can accompany an airline flight.
Surgery to Decrease Abdominopelvic Adhesions
Description of common procedures. Some patients with recurring bowel obstructions are encouraged to undergo surgery to decrease adhesions in the abdomen or pelvis. The intent of adhesion surgery (adhesiolysis) is to cut or burn adhesions affecting the bowel and return the intestines to an earlier state of mobility and function. In a laparoscopy, the physician places the patient under general anesthesia and then makes several holes (ports) in the body. Using one of these ports, the doctor will first fill the abdominal cavity with gas to separate the organs. This separation allows the surgeon to view a path to insert the surgical instruments s/he will use to cut or burn adhesions affecting the bowel. The doctor will also insert a light and a camera through the other port(s). You can observe a laparoscopy to decrease adhesions by clicking here.
When intestinal adhesions are extensive, the physician may perform or transition to an open surgery called a laparotomy. In that surgery, the body is cut open with a scalpel, and then the skin and outer layers are separated with a metal retractor. Next, the physician enters with a scalpel, laser, or other surgical instrument to cut or burn any adhesions s/he may find that are affecting the intestines. S/he will repair or cauterize any bleeding that occurs, and may check the area for other problems before exiting the body. Finally, s/he will close the body with stitches and send the patient to a room where recovery can be monitored. You can view an open bowel resection by clicking here.
In a laparotomy, the surgeon will often remove (then replace) all 21 feet (7 meters) of the bowel to search for problem areas.
Advantages of Surgery
Direct visualization. The surgeon can directly see, then burn or cut adhesions that do not appear on diagnostic tests such as MRI or CT scan. Complications can occur in patients with significant adhesions if the doctor has difficulty seeing through the layers s/he is cutting (see below).
Observe nearby areas. In addition to treating the adhered area, the physician can visualize nearby structures. Thus, s/he can note and possibly treat any other problem areas in the vicinity.
Operative report. The doctor will dictate a report that describes what s/he observes and the procedures performed during the surgery.
Disadvantages: Surgical Risks and Challenges
Anesthesia complications. Recent studies have considered whether general anesthesia may have a neurotoxic effect on the brain or other areas of the body. (Perousakis & Hemmings, 2009)
Inadvertent enterotomy. When a patient has significant adhesions, it can be difficult for the doctor to see the structures beneath them. Thus, a surgeon can unintentionally cut into a nearby healthy organ or other structure, called an inadvertent enterotomy (IE). An IE can cause serious problems or death. In a study from the Journal of the Society of Laparoscopic Surgeons, the authors note that:
“IE in laparoscopic abdominal surgery is underreported.”
Hospitalization during recovery. Abdominopelvic lysis of adhesions is a major surgery, and most patients undergo a hospital stay afterwards. During this time, the patient’s condition was closely monitored to ensure recovery and avoid post-surgical complications or infections.
New adhesions generally form after surgery. A mammoth 50-year review of abdominal and pelvic surgery in the U.S. revealed that nearly all abdominal and pelvic surgeries cause new adhesions to form. Thus, adhesions can recur – sometimes worse than before the surgery to remove them.
Surgery is widely regarded as the primary cause of bowel obstructions due to post-surgical adhesion formation.
Pre-Treatment Screening (Surgery and Therapy)
Both therapy and surgery require patients to be screened for appropriateness and contraindications before treatment.
Screening before therapy. Before we can accept you for therapy, our staff will conduct a thorough review of your history of healing events (prior surgery, trauma, infection, endometriosis, etc.) to determine where adhesions have likely formed and how they might be causing problems related to your symptoms and complaints. We then consult with each patient to review goals, risks, and the potential benefits they can expect.
We want you to do well and to have a reasonable chance to reach your goals. We will accept you if we feel we can help you; we will alert you if we have concerns that you will not do well with therapy. Similarly, we will not accept you if we feel that you will not have a favorable outcome.
Screening before surgery. Before surgery, your physician may order diagnostic tests to help rule out contraindications, such as active infection, and to help identify problem areas in the body that should be assessed during surgery. Your doctor should consult with you to review the goals of surgery, along with the risks and potential rewards you can expect. We encourage you to ask your doctor about the risk of post-surgical adhesion formation and an estimate of the need for future surgeries.
Discover hope for adhesion-related pain and dysfunction with Clear Passage® Physical Therapy’s non-surgical, hands-on approach – Request Information and schedule your Free Consultation today to explore how our expert therapists can help you avoid surgery and improve your quality of life. To learn more about our innovative treatment methods and take the first step towards relief, visit our Apply to Therapy page.
“I want to express my gratitude to Clear Passage® Therapies for what you were able to do for me. The wonderful work you perform deserves recognition. I am a woman who has had four surgeries. For me, the surgery caused adhesions that became extremely painful. If it were not for Clear Passage® Physical Therapy, I would be contemplating another surgery for obstruction in my bowel caused by adhesions. I am hopeful that one day the medical doctors will prescribe this therapy to all patients who suffer from adhesions.” – Karyn
Suspected Adhesions. LaRues Story
Overview
Adhesions are internal scars that form wherever the body heals from tissue damage due to surgery, infection, inflammation, injury, radiation, or endometriosis. While adhesions are the first step in the healing process, they sometimes continue to grow in the body. They can create powerful glue-like bonds that can squeeze structures like straitjackets, decreasing their function or causing pain. Adhesions can attach organs, muscles, and other structures that are designed to be separate, decreasing their natural movement and function.
Because the body has no way to detach or eliminate them, adhesions tend to remain in place or grow over time. When their glue-like bonds wrap around structures or bind them to others, adhesions can cause significant problems. These problems may be deemed ‘unexplained’ because most adhesions cannot be seen on diagnostic tests (CT, MRI, X-ray, ultrasound).
Avoiding Surgery for Adhesion-Related Disorder (ARD)
Adhesions can become very serious, slowing or stopping the function of some of the body’s most important internal structures. Left untreated, they can prevent life when they block a woman’s fallopian tubes. When they form in the digestive tract, they can cause bloating, diarrhea, or constipation. In cases where they squeeze the intestines, they can end a person’s life by totally blocking the passage of food. Studies show how frequently adhesions form following surgery. Therefore, treating adhesions with surgery that will so often cause more adhesions seems counterproductive. Below, we have outlined and explained the advantages and disadvantages of two treatment options shown to be effective in decreasing adhesions: Clear Passage® Physical Therapy and Surgery.
Surgeries often cause more adhesions
Overview of Treatment Options
According to medical literature, there are only two known options to decrease adhesions in the body:
Clear Passage® Approach
Surgery
Therapy to Decrease Adhesions
Description of the procedure. The Clear Passage® Approach is a manual physical therapy that uses no drugs and no surgery. It has been cited in numerous peer-reviewed medical journals for its ability to decrease adhesions in the abdomen and pelvis. Some of the studies of its effectiveness include ‘before and after’ images and reports of individual patients, prepared by independent diagnostic physicians and published in reputable medical journals. Other studies examine larger groups; some compare our results to surgeries.
The therapy is ‘all natural’ in that it is 100% ‘hands-on.’ Patients describe it as often feeling like a very deep massage. The therapy can sometimes be much lighter, depending on the area and depth being treated. Clear Passage® therapists use their hands to locate adhered areas of the body related to the patient’s pain or symptoms. The therapist then transitions to very site-specific techniques to deform and detach the tiny strands that comprise adhesions. Therapy may be compared to pulling out the strands of a nylon rope or pulling out the run in a sweater. Our therapists describe it as feeling “like pulling out salt-water taffy, in very slow motion.”
Our therapists are experts at palpating and manipulating the soft tissues of the body, where adhesions generally form. They use data from the patient’s history, direct feedback from the patient during therapy, and a thorough training and understanding of methods developed over 30 years to locate adhesions. Then, they deform and detach the molecular/chemical bonds that are at their core. The usual protocol cited in the published studies consists of 20 hours of therapy, spaced over five or more days. You can view a short video of a Clear Passage® therapy session by clicking below.
Advantages of Therapy
No hospitalization. Therapy is always performed in a private treatment room, one-on-one with a highly skilled therapist certified in the work. Patients may bring a partner or family member along for company, if they like.
No anesthesia. The patient is awake and communicative during the entire procedure. Patient involvement is encouraged, with the patient invited to give feedback throughout the course of therapy.
Decreased risk. Risk is minimal. There is no cutting or burning, no risks associated with anesthesia, and no risk of inadvertently cutting through a nearby organ or other structure.
No foreign bodies are introduced. No staples, stitches, films, or meshes are inserted into the body. No cameras, gas, lights, or surgical instruments enter the body.
Side effects are mild and transient. The most common side effects reported with therapy are temporary tenderness, aching, fatigue, and hip or back pain. When they occur, these symptoms pass within a few days.
Improvements in other areas of the body. Because therapy focuses on detaching adhesions throughout the body, patients often report increases in flexibility and range of motion after therapy. Many report decreased pain and/or increased function in areas near the site where they are being treated or even in distant areas. This pain reduction is often noted in the lower back, due to the freeing of abdominal adhesions that were restricting the front of the lumbar vertebrae. Some report improvements in areas where they had forgotten or had not realized they were having a problem, until therapy relieved the pain or tightness.
Written reports. After therapy, we send each patient a typed, detailed Initial Evaluation along with a typed Progress Report or Discharge Summary. If needed, we are glad to send you daily notes of every therapy session.
Don’t Let the Cost Keep You From Finding Out If Clear Passage® Can Help
You’ve probably already spent money on doctor visits, tests, medications, procedures, and treatments that didn’t give you the answer you were hoping for. The last thing you need is to finally find a treatment worth exploring and then have the cost stop you in your tracks.
Therapists cannot visualize the adhesions. Initially, we deduce the likelihood of adhesions by conducting a thorough review of each patient’s history and symptoms. To gain further insights, we may require diagnostic tests or documentation from the patient’s physician. During therapy, we palpate the areas of your body related to your symptoms and other areas where we note scarring, tightness, spasm, or increased temperature. Because our therapists have been practicing manual therapy for their entire professional lives, they are experts at palpating the body.
Costs of therapy are generally a fraction of the cost of surgery; as with surgery, insurance reimbursement may vary based on your insurer and your plan. Clear Passage® is an out-of-network provider for your insurer. In weighing costs, many patients take into account the cost to their quality of life vs. the cost of living with adhesions.
Travel and time are considerations. Therapy generally takes five days (e.g., Monday – Friday); it is only provided by trained, certified therapists in several cities in the U.S. and U.K. The 5-day program is designed for out-of-town and out-of-country patients. We suggest that patients with a history of bowel obstructions remain in town for an extra day before returning home, to allow the body to return to homeostasis before undergoing the changes in air pressure that can accompany an airline flight.
Surgery to Decrease Abdominopelvic Adhesions
Description of common procedures. The intent of adhesiolysis surgery is to cut or burn adhesions with the goal of returning the body to an earlier state of mobility and function. In a laparoscopy, the physician puts the patient under general anesthesia, then cuts several holes (ports) in the body. The ports serve several functions. One is used by the physician to fill the abdominal cavity with gas to separate the organs. This separation allows the surgeon to see where s/he can insert surgical instruments and access the adhesions. Using the other ports, the doctor will insert a light, camera, and surgical instrument(s), which they can use to burn or cut adhesions that they see. You can observe a laparoscopy to decrease adhesions by clicking here.
When adhesions are extensive, the physician may elect to perform an open surgery called a laparotomy. In that surgery, the body is cut open with a scalpel, with the sides generally separated with a metal retractor. Next, the physician enters with a scalpel, laser, or other surgical instrument to cut or burn any adhesions s/he may find. S/he will repair or cauterize any bleeding that occurs, and may check the area for other problems before exiting the body, closing it with stitches, and sending the patient to a room where staff can monitor the patient’s recovery.
Advantages of Surgery
Direct visualization. It is a significant advantage that the surgeon can directly see and burn or cut adhesions that do not appear on diagnostic tests such as MRI or CT Scan. Complications can occur in patients with significant adhesions if the doctor has difficulty seeing through the layers s/he are cutting through (see below).
Observe nearby areas. In addition to treating the adhered area, the physician can see nearby structures, noting any additional areas that may be of concern.
Operative report. The doctor can film the surgery and dictate a report describing what s/he observes and the procedures s/he performs during the surgery.
Disadvantages: Surgical Risks and Challenges
Anesthesia complications. Recent studies note concerns about mild to moderate brain damage for patients who undergo one or more sessions of general anesthesia. (Perousakis & Hemmings, 2009)
Inadvertent enterotomy. When a patient has significant adhesions, it can be difficult for the doctor to see the structures beneath them. Thus, a surgeon can unintentionally cut into a nearby healthy organ or other structure, called an inadvertent enterotomy (IE). An IE can cause serious problems or death. In a study from the Journal of the Society of Laparoscopic Surgeons, the authors note that:
“IE in laparoscopic abdominal surgery is underreported.”
Hospitalization during recovery. Most patients must undergo a hospital stay after adhesion-related abdominal or pelvic surgery. During this time, hospital staff will monitor the patient to ensure their recovery and to avoid post-surgical complications or infections.
New adhesions generally form after surgery. According to a 50+ year review of abdominal and pelvic surgery in the U.S., nearly all abdominal and pelvic surgeries cause new adhesions to form. Thus, adhesions can recur – sometimes worse than before the surgery to remove them. The study notes that adhesions form after 55% to 100% of pelvic surgeries and after 90% of major abdominal surgeries.
Pre-Treatment Screening (Surgery and Therapy)
Therapy and surgery both require patients to be screened for appropriateness and contraindications before treatment.
Screening before therapy. Before we accept you for therapy, our staff will conduct a thorough review of your history of healing events (prior surgery, injury, infection, endometriosis, etc.) to determine if and where adhesions have likely formed and how they might be causing problems. We then consult with you to review goals, risks, and potential benefits you can expect.
We want you to do well and to have a reasonable chance of reaching your goals. We will accept you for therapy if we feel we can help you. Similarly, we will alert you if we have concerns that you will not do well with therapy; we will not accept you if we feel that you will not have a favorable outcome. Screening before surgery. Before surgery, physicians may order diagnostic tests to help rule out contraindications such as active infection and to help identify problem areas in the body that should be assessed during surgery. Your doctor should advise you of the goals of surgery, along with the risks and potential rewards you can expect. It is likely a good idea to ask your physician about the chance of developing post-surgical adhesions with the need for one or more additional surgeries.
“By the time I found Clear Passage®, my health was plummeting. At my initial evaluation, my therapist told me there was very little mobility in my abdominal organs. She was also concerned that I was becoming adhered in the muscles and support structures on the front of my body. I attended treatment and found that my pain had reduced markedly. I stopped experiencing pain in my bowels, neck, and back. Things in life that most people take for granted, but that had been denied to me for so long, slowly began to return. I can still remember the first day I was finally able to have a bowel movement without pain or laxatives, and the first time I was finally able to eat without pain. It was amazing.”
The images above show the ability of the Clear Passage® Approach to clear bowel obstructions without surgery. Noting the severe narrowing in the ‘Before’ images, the physician scheduled the patient for emergency surgery to remove and repair two obstructions in the intestine.
In the left images, we see “BEFORE” images of
A six-inch long ‘string stricture’ as narrow as a coffee straw in the lower bowel, and
An ‘hourglass obstruction’ severely restricts the upper bowel.
The patient requested Clear Passage® therapy instead of surgery. Images AFTER Clear Passage®’s hands-on treatment (only) show that our therapy cleared both obstructions – without surgery. The physician canceled the surgery as it was “no longer necessary.”
Stopping Repeat Obstructions with Natural Bowel Obstruction Treatments
In a series of ground-breaking studies, a hands-on physical therapy (Clear Passage® Approach) designed to reduce or eliminate adhesions has been shown to decrease recurring total SBO events by 15 times the norm, with just five days of therapy. Using no surgery and no medications, this treatment was shown to be safe and highly effective at reducing or eliminating adhesions and bowel obstructions.
Treating Recurring Bowel Obstructions:
What therapy is like:
Our treatment program generally consists of 20 hours of hands-on therapy designed to decrease the adhesions in your intestines and nearby areas. Treatment is often delivered in two-hour sessions, each morning and afternoon, for five days. Patients are free to relax in their hotel or explore the local area between sessions.
Sometimes likened to deep, site-specific pressure, the therapy is specific to your adhesions – bonds that can form over years or decades. During your sessions, we will instruct you in self-treatment techniques to further clear your intestines of adhesions and to help you avoid future obstructions.
Complete our online Request Consultation form to receive a free phone consultation with an expert therapist and learn more.
Causes and Frequencies of Blocked Intestines
What Causes a Bowel Obstruction?
Despite the greatest education, training, skill, and compassion of any surgeon, internal scars called adhesions form as the body’s first step in healing from surgery. Unfortunately, post-surgical adhesions are widely regarded as the primary cause of bowel obstruction. Thus, the surgery that may save your life is often the cause of subsequent blockages.
Bowel obstructions (which people often refer to as blocked intestines) are usually due to internal scars (adhesions) that form in the small intestines (small bowel) and sometimes in the large intestine (colon). Adhesions form as the first step in healing from surgery, infection, inflammation, or trauma. Adhesions are a primary cause of obstruction or blockage in the bowel. Regardless of where they form, adhesions join structures with strong glue-like bonds that prevent organs from functioning properly.
Adhesions may form as curtains or ropes within or between the loops of the bowel, completely blocking the passage designed to transport food. When these adhesions prevent the body from processing food, a bowel obstruction can quickly become a life-threatening condition. In fact, bowel surgery was cited by the AMA as the second most common emergency room surgery in the USA. Adhesion removal is the fifth most common ER surgery.
Foods That Cause Bowel Obstruction
Certain foods, particularly those high in fiber or difficult to digest, can contribute to the risk of developing a bowel obstruction in individuals with underlying digestive issues or a history of gastrointestinal surgery. Foods such as nuts, seeds, corn, and raw vegetables are notorious for their potential to form indigestible masses, especially in cases where the bowel is already narrowed or compromised by conditions such as diverticulitis or prior adhesions. Ingesting large quantities of these foods without adequate hydration can lead to the formation of bezoars — hardened, indigestible masses that can block the intestines. Download Clear Passage®’s FREE diet guide to help you avoid further bowel obstructions and learn about an SBO diet right for you!
Blocked bowel symptoms can include severe pain, nausea, or vomiting accompanied by difficulty or inability to pass gas or stool. Blocked from its normal clear passage, food becomes backed up. The intestines stop functioning, preventing the patient from eating or eliminating waste.
A more comprehensive list of bowel obstruction symptoms includes:
No bowel sounds
Hyperactive bowel sounds
Nausea and vomiting
Stringy stools*
Stomach cramps that come and go
Diarrhea (if the bowel is partially blocked)
Swelling or bloating of the stomach (distention)
Pain or tenderness around or just below the belly button
Constipation and the inability to pass gas (a sign of complete blockage)
*Stringy Stool
One of the lesser-known indicators of a bowel blockage is the appearance of a pencil-thin BM, sometimes referred to as stringy stool. This symptom, often overlooked, suggests a partial obstruction, allowing only a narrow passage for stool to pass. The stringy consistency results from the stool being squeezed through the constricted section of the intestine, highlighting a change in bowel habits that warrants further investigation.
If you experience severe abdominal pain or other bowel obstruction symptoms, you should seek immediate medical care.
Severe abdominal pain, persistent bloating, nausea, and the inability to pass gas or stool can be a sign of a blocked bowel that should be evaluated by a medical professional as soon as possible.
How Do You Clear Bowel Obstruction without Surgery: The Clear Passage® Wurn Technique®
The Clear Passage® Approach is a very site-specific manual therapy, the result of decades of study and investigation by Clear Passage® staff. It is quite different from any other physical therapy that we know of. Like peeling apart the run in a three-dimensional sweater, this non-surgical technique focuses on reducing or eliminating adhesions, cross-link by cross-link (bond by bond).
This therapy has been credited with saving lives and returning normal lifestyles to many people, including those who suffer from recurring bowel obstructions. Clear Passage® therapists have had hundreds of successes decreasing or eliminating obstructions and adhesions that block the intestines. We have broken the repetitive “adhesion-obstruction-surgery” cycle that many of their patients describe as their life before Clear Passage®.
Other Small Bowel Obstruction Management
Once hospitalized with a bowel obstruction, the patient will generally have a nasogastric (NG) tube passed through the nose and into the stomach to relieve pressure. Physicians then place a PICC line into a vein to draw blood and to give the patient nutrition, pain medications, etc. Then, the medical team will wait (sometimes for several days) to see if the obstruction clears on its own.
If the obstruction does not clear, patients generally must undergo surgery as the primary method to clear small bowel obstructions. While this surgery can save the lives of those in immediate danger, obstructions tend to recur for many patients as post-surgical adhesions form due to the very surgery performed to repair the bowel. Thus, many patients find themselves in a repeating cycle of “adhesions-obstruction-surgery-adhesions” with no end in sight.
Surgical lysis (destruction) of bowel adhesions is a major drawback due to the formation of new adhesions to repair the underlying tissue. Besides the creation of new scar tissue, the risks associated with general anesthesia.
A multi-decade study published in Digestive Surgery found that more than 90% of patients develop adhesions after open abdominal surgery, and 55% to 100% of women develop adhesions following pelvic surgery. (Liakakos et al., 2001) Another study reported that 35% of all open abdominal or pelvic surgery patients were readmitted to the hospital more than twice to treat post-surgical adhesions during the 10 years after their original surgery. (Ellis et al., 1999) Thus, abdominal surgery has been identified as a major cause of adhesion formation, leaving many patients trapped in the “surgery-adhesions-surgery” cycle described earlier.
Published Studies and Success Rates – Clear Passage® Physical Therapy
To view a complete list of published success rates treating Bowel Obstructions with Clear Passage®, please visit our Bowel Obstruction Success Rates page.
A large (Phase 2) controlled study authored by physicians from Harvard, Stanford, and Washington University medical schools examined repeat obstructions for patients who received the therapy vs. those who did not. Twenty hours of Clear Passage® therapy (often given over five days) decreased repeat bowel obstructions by several times the norm for patients who received the treatment vs. those who did not receive therapy. The results are shown below.
Bowel obstructions are a serious medical condition. Left untreated, they can lead to serious complications or death. The severity and potential fatality of a bowel obstruction depend largely on the cause, location, and duration of the obstruction, as well as the timely initiation of treatment. Without appropriate medical intervention, complications such as bowel perforation, sepsis, and severe dehydration can occur, significantly increasing the risk of mortality. Seek immediate medical attention if you are experiencing an obstruction. Treatment at Clear Passage® Therapies has been shown to decrease or stop further bowel obstructions and improve the quality of life!
Survival with Bowel Obstruction
Life dealing with recurring bowel obstruction is full of uncertainty, pain, and a decrease in function. Surgical intervention generally creates more scar tissue. Clear Passage® has been shown to decrease adhesions and clear bowel obstructions. When that happens, we find that pain and the fear of hospitalization for new obstructions decrease, followed by improved quality of life.
The hands-on therapy at Clear Passage®️ focuses on decreasing the adhesions (internal scars) that form when the body heals. Published studies show good results without surgery. To learn more about how we achieve results, click the appropriate condition in the menu at the top of any page of our website.
Complete our online Request Consultation form to schedule a phone consultation, at no cost to you, and to learn whether our natural treatment may help you.
Patient testimonials on Clear Passage® taking care of their abdominal pain.
Overview
Adhesions form anywhere in the body, including the abdomen and pelvis – the area between the ribs and the pubic bone. Like adhesions elsewhere in the body, abdominal adhesions can act like an internal glue or a straitjacket, binding organs to other structures when they should be able to move freely around each other. Adhesions can also squeeze parts of organs or entire organs, decreasing function and sometimes causing pain.
Adhesions can slow or totally stop the movement of food through our digestive tract, creating a life-threatening condition called a small bowel obstruction (SBO). Adhesions can trap excess bacteria sometimes found within the intestine (SIBO, or small intestinal bacterial overgrowth), decreasing or eliminating the effectiveness of medications.
SBO treatment: When published studies showed we could open fallopian tubes blocked by adhesions, we began developing therapy to clear the adhesions from the larger tubes, the intestines. We have had success in preventing repeat bowel obstructions for over a decade. You can read about our success in this area in published studies and on our Bowel Obstruction website page.
SIBO treatment: We found we could help SIBO when physician experts in the condition came to us, asking for our help. They said, “We can treat the excess bacteria with effective medications, but if there are adhesions in the intestines, the SIBO just returns. When you decrease the adhesions, the treated bacteria can finally exit the body.” They began referring patients with SIBO, and the results have generally been excellent. The combination of clearing bowel adhesions along with pharmaceutical and/or natural ingredients to stop the overgrowth turns out to be ‘just what the doctor ordered’ for many patients with SIBO.
Experience – We have been treating adhesions in the body since 1989. We hand-pick each therapist based on years of manual therapy experience, courses attended before we train them, their palpation and treatment skills, their focus, and their compassion. We train each extensively in the therapy we have researched and developed over the course of three decades.
Safety – We have developed our treatment over 30+ years with two goals: safety and effectiveness. We screen each patient for contraindications to therapy. We have treated several thousand complex cases and conditions. We often consult with physicians and scientists throughout the treatment process to ensure positive outcomes. Our procedures have been documented as safe. They are tailored to each patient’s needs.
Risks – We avoid risks due to our thorough screening process. The major risk is temporary soreness. Side effects of therapy are generally positive, including increased function, increased range of motion, and decreased pain.
Success rates – Our success rates are clear. They are peer-reviewed and published. Our success with long-term outcomes is encouraging. View our success rates here.
Published Results
With published studies and citations in a dozen respected medical journals, Clear Passage®️
is the Gold Standard in the world for decreasing abdominal adhesions non-surgically. Study data authored by independent physicians support our credibility, efficacy, and success rates.
Clear Passage®️ constantly strives to measure our results scientifically and share them with the public – as reported in peer-reviewed medical journals. We have been researching and developing our therapy since 1989; our success rates are documented and housed in the U.S. Library of Medicine. Over the course of 30+ years, we have worked with physicians, surgeons, and scientists to develop a therapy that has been shown to be safe and effective.
We Treat Pain or Problems From Childhood Surgery and Trauma Without Surgery or Drugs
Surgery can create problems for children and young adults as the body attempts to grow around tissues that become adhered as a result of early surgery. Untreated, these problems can persist or become worse in adulthood, affecting the body for a lifetime. Severe trauma and/or surgical repair can cause scarring and adhesions to form in children, leading to pain and limiting their quality of life.
Clear Passage® has over two decades of experience decreasing the adhesions caused by childhood surgeries and traumas using a non-surgical, manual physio/physical therapy. We often treat severe cases of adhesions and post-trauma or post-surgical pain in adults, and in children accompanied by a parent or guardian. Studies on our work have been published in peer-reviewed U.S. and international medical journals.
Complete our online Request Consultation form to receive a free phone consultation with an expert therapist and learn whether this therapy can help.
Childhood Surgery and Trauma Overview
It is not uncommon for infants and children to undergo surgery as a result of the repair of a congenital disorder, trauma, or disease. As the body recovers from the surgery, it creates internal scars and adhesions as part of the healing process.
Ideally, the scar will grow and expand with the rest of the body as the child grows, but this does not always happen. When tightly bound scars or adhesions persist and fail to expand fully as the body around them grows, they can create problems that can last a lifetime.
A childhood surgery can cause severe scarring and adhesions in delicate tissues. We have treated this condition in the intestines when digestion becomes compromised or life-threatening in the case of bowel obstructions. We have also treated adhered joints that were causing pain or that showed decreased range of motion. Our therapy has been quite successful in cases of adhesions after partial or total removal of organs and in cases of severe trauma. In all of these cases, adhesions tend to bind the structures in straitjackets with a strength of nearly 2,000 pounds per square inch (140 kilograms per square centimeter), restricting their mobility and function and often causing pain.
Like their parents, traumatized children want control of their lives and what is happening to their bodies – and to be recognized as important members of their healing team. Thus, we treat our young patients (and their parents) with the compassion, consideration, respect and dignity that we give to our adult patients.
Treatments
Clear Passage®️ Treatment
Clear Passage® Therapists have been treating the adhesions that form in infants and children for over three decades. In fact, our work began when our director, Belinda Wurn, P.T., began her search for relief from her own post-surgical adhesions. In our focus on adhesions, we have treated several thousand patients since that time.
We use our hands to slowly peel apart adhered tissues, always working within the patient’s comfort and tolerance levels. We gently break apart the hundreds of tiny strands that comprise adhesions – powerful bonds in the complex network of the patient’s body – that are causing pain, tightness, or dysfunction. Most of our post-surgical patients find that our therapy restores mobility that has not existed in their bodies for years – or ever, in the case of early surgery.
We treat children (age 10 and above) who have endured severe trauma and multiple surgeries, such as kids with severe scarring or adhesions and those with recurrent bowel obstructions. We always treat them with the skilled hands we are known for – with this additional consideration…
We also understand the need to treat children and adults in a ‘safe place’. We provide an atmosphere with the utmost emphasis on dignity and sensitivity. While our work is physical, we also understand the psychological issues that can naturally accompany pain, dysfunction, or simply the idea that the patient feels different from everyone else. We are happy to consult and work with a patient’s physician or counselor before, during, or after therapy.
Other Treatment Options (Surgery, Drugs)
Other treatment options for early surgery and trauma range from pain medication to additional surgeries.
Pain medication can be useful to reduce the severity of symptoms; however, it is a temporary fix, as the medication is a mask for the symptoms; it doesn’t address the cause of the problem.
Physicians generally envision surgery as a last option. Surgery poses the risk of additional formation of adhesions, creating more pain and more dysfunction for the patient in future years.
An early surgery can cause severe scarring and adhesions in delicate tissues. As the child grows, the adhesions remain in the body like nylon ropes or straitjackets – with a strength approaching 2,000 pounds per square inch (140 kilograms per square centimeter). Untreated, the child’s body must grow around the adhered tissues, which do not expand as the child grows.
Published Research
Read a case study on avoiding further surgeries in a dramatic pediatric patient here. This is a case in which a child’s pelvis was split open like a book when the child was run over by the wheels of his school bus.
Additionally, read our published study on treating abdominopelvic adhesions with the Clear Passage® Approach here.
Testimonials
To read past patient success stories, please visit our Testimonials page.
Following the ‘scientific method’ for investigative new modalities, we began by publishing some remarkable case studies, all of which can be read on our Published Studies page. These studies included a woman who managed to stay alive despite a bowel that was virtually totally blocked. When she first arrived for therapy, it was clear that her only nutrition was through an intravenous PICC line. After several hours of therapy, her physician was able to remove her PICC line because she found she could eat normally. This and other surprising results inspired us to investigate further, with more involved studies.
Due to the complex structure and numerous functions of the bowel, measuring success in treating patients with recurring small bowel obstruction (SBO) presented several opportunities. In short, we found three major areas of concern that we could measure by comparing conditions before and after therapy:
Structure – Independent radiographic images taken before and after therapy
Repeat Events – Number of repeat obstructions before and after therapy
Quality of Life – Graded by patient, results tabulated by biostatisticians
STRUCTURE – BEFORE AND AFTER X-RAYS
Some patients allowed us to document the structure of their intestines by undergoing a “small bowel follow-through” test (SBFT) before and after therapy. In this test, the patient would swallow a cocktail that contained a barium tracer, which would give precise images of the interior of the bowel. Concerned that they might obstruct the test, many patients avoided taking this test, which involves swallowing a rather thick liquid with a radio-opaque barium tracer. Nevertheless, the test does give a good picture of the inside of the bowel; it can show where narrowing or obstructions might be occurring. Using this test, we’ve been able to get some very clear images that document bowel obstructions in patients who arrive for therapy, and the result of our hands-on care on their previously blocked intestines.
In the images shown here, one can clearly see the progress of the liquid (shown in white) as it passes through the small intestine, and where it becomes blocked. These images give a dramatic testament to the positive changes we can actually see in ‘before and after’ images.
In the two-part image shown here, we see in the image taken “Before” therapy, an hourglass-shaped stricture (narrowing) is visible in this patient’s intestines. The constriction is so significant that very little dye goes through to the bowels below, beyond the stricture. In fact, the patient was scheduled for emergency surgery before we treated her. Instead, she decided to try Clear Passage® therapy first.
Comparing that with the “After” image, one can easily see that the stricture completely resolved (disappeared) after therapy designed to clear adhesions from the area. Notice also how open the intestines are above and below the site of the prior stricture, in the areas beyond the previously narrowed bowel. The radiologist cited this as a “normal bowel” after therapy.
In the second set of images, we see a very dramatic string stricture “Before” therapy. This is a 3-inch-long section where the contents of the bowel are passing through an area that is narrowed to the size of a coffee straw. Certainly, no food was going to pass through this area. Again, this patient opted to first try Clear Passage® therapy, rather than undergo abdominal surgery to repair her bowel.
In the image taken “After” therapy, we can see that the area that was once so narrow for its entire length has broadened dramatically. In fact, this radiologist noted after therapy, “This patient now has a normal bowel.”
We have published other similar “before and after” images, but these are clearly quite clear and demonstrative. Once thought impossible, these images clearly demonstrate the effectiveness of a manual therapy, designed and tested for its ability to decrease adhesions, to dramatically improve the structure of the bowel.
REPEAT EVENTS – DECREASING RECURRING OBSTRUCTIONS
Surgery as a Cause of SBO
It is a well-known fact that surgery is the primary cause of bowel obstruction. No matter how compassionate, brilliant, or skilled the surgeon, the body must heal from the cuts or burns imposed by the surgery. The first step in the process of healing from surgery is the laying down of adhesions (scar tissue) in a random pattern over the tissue that has been damaged. Thus, the surgery designed to cure the obstruction can be the cause of the next obstruction.
Unwanted Complications
In some cases, a drop of bacteria-laden bowel contents can leak unseen into the abdomen before the physician closes the patient. Set free in this warm, moist, and dark environment, bacteria can proliferate quickly. Perhaps for that reason, roughly one in five (18 % per HHS) of all bowel resection patients are readmitted to the hospital within 30 days of their SBO surgery, often for peritonitis or other infection that occurs when bacteria freed from the intestine grow in the post-surgical abdomen. In this case, the physician will often reopen the patient surgically to introduce antibiotics directly into the infected spaces. The surgeon may choose to leave the body open to continue to administer medications directly into the abdomen and allow scarring to occur from the inside out to treat all of the infection. Naturally, this tends to create even more adhesions.
Even for those who are not re-admitted to the hospital during the month after surgery, the chance of a repeat obstruction caused by a prior surgery is too high. While surgery is routinely cited as the primary cause of bowel obstruction, a recent study in the Journal of the American Medical Association[i] notes that bowel resection is the 2nd most common emergency surgery in the U.S.A. and carries the highest complication rate (47%). The mortality rate was 6.5%, so 1 in 15 died during or after the procedure.
Most of our SBO patients are too familiar with the problem of repeated obstructions. They come to us with the goal of “no more obstructions.” They tell us they are tired of a lifetime of wondering, “Is this the day I’m going to die?” or “Is this the day I’m going to have to be struck down with severe pain and have to go to an emergency room with an obstruction?” Our patients ask us about their chances of avoiding future obstructions so they can get back to living their lives without dread or uncertainty. In order to give a truthful answer, we put this question to our research staff.
To conduct a study of this nature, we enlisted the help of physicians and researchers from several medical schools, including Harvard, Stanford, Washington University, the University of Florida, and the University of Arizona. Their guidance helped design a controlled study of 239 patients who were experiencing recurring bowel obstructions.
We treated 103 of the patients (the Therapy Group) and did not treat 136 of them (the Control Group). The typical Therapy patient received our usual protocol: 20 hours of Clear Passage® treatment over 5 days. Control patients received the present Standard of Care, which is no therapy. We measured repeat Total and Partial Obstructions and Repeat Surgeries 90 days after the study closed.
Results (shown here) were remarkable. The group we did not treat had 15 times more total bowel obstructions than those we treated. In fact, less than 1% of the patients we treated underwent another total bowel obstruction measured 90 days after the study closed. By contrast, close to 15% of the Controls (no therapy) had another total obstruction within the same 90-day period. Measured in both statistical and humanitarian ways, we found these results to be wonderful.
As shown in these images, the untreated group also had 2½ times more partial obstructions and 3 times as many surgeries as the patients we treated.
IMPROVING QUALITY OF LIFE
We find quality of life to be an important measure of success for patients who have undergone the traumas of bowel obstruction (with or without surgery), followed by years of fear of having another one or more. So many of these patients are miserable, often in pain, frustrated at a medical system they feel has let them down. Many report that their physicians say, “There’s nothing you can do to change this.” We are glad that our therapy is beginning to turn that attitude around.
Virtually all of these people live in fear of another obstruction that could happen at any time. Thus, we hired a biostatistician to design, validate, and publish a questionnaire and rating tool to measure quality of life in the five major ‘domains’ where they report problems:
The questionnaire was given to patients when they enrolled in the study, and then again 90 days after the study closed. The biostatistician was able to measure changes (if any) between the start and end dates for both the Therapy and the Control Group.
Realizing that both the degree of pain and the ability to move freely affect Quality of Life, we added a “pain rating” section and a section that compared ‘before and after’ Trunk Range of Motion for each participant.
The Diet Domain assessed the diet of the subject from inability to tolerate any liquid to a normal solid food diet.
The Pain Domain reported pain throughout the body, with oral intake of food or liquid, and with bowel function.
The Gastrointestinal (GI) Symptom Domain quantified symptoms often associated with SBO, such as nausea, emesis, bowel spasm, and constipation.
The Medication Domain reports the frequency of medications required to maintain bowel function.
The Quality of Life Domain quantified the amount of time off work and social activities. In addition, it quantified each patient’s overall concern regarding their bowel function. We found that all of these tend to be major lifetime concerns for many people who experience recurring bowel obstructions.
QUALITY OF LIFE – STATISTICALLY MEASURED RESULTS
A Note on Statistics
Statisticians measure results by asking, “What is the chance this result could have occurred by chance?” In this study, they used the common statistical measure (p=.05). This means if the measure is smaller than “5 out of 100”, the result is statistically significant (reliable). Any number greater than “.05” is considered clinically insignificant (unreliable). The data in the controlled study shown here, and published in the prestigious World Journal of Gastroenterology, showed very high statistical significance (reliability) at p<0.0001. Thus, the chance that the numbers are unreliable was less than 1 out of 10,000 for Clear Passage® patients in the domains shown below. In essence, these results are considered highly reliable.
Trunk Range of Motion measurements showed that all Clear Passage® patients demonstrated overall improvement in Range of Motion (p<0.0001) extrapolated statistically in the table below.
In addition to the statistical measures shown above, the journal notes or implies other major or obvious Quality of Life advantages of Clear Passage® over the present Standard of Care (no therapy). These tend to include hospitalization, insertion of an NG tube, intravenous hydration, possible surgery, and ongoing fear of another obstruction. (The difference in this fear was significant in the Quality of Life domain.) These “other advantages” are shown here in an image labeled Quality of Life.
RESULTS (direct quote from the study)
Despite histories of more prior hospitalizations, obstructions, surgeries, and years impacted by bowel issues, the 103 CP-treated subjects reported a significantly lower rate of repeat SBO than 136 untreated controls (total obstructions, P = 0.0003; partial obstructions, P = 0.0076).
Subjects treated with the therapy demonstrated significant improvements in five of six total domains in the validated Small Bowel Obstruction Questionnaire (SBO-Q).
Domains of diet, pain, gastrointestinal symptoms, quality of life (QOL), and pain severity when compared to post CPA treatment were significantly improved (P < 0.0001).
The medication domain was not changed in the CPA treated group (P = 0.176).
A Note on Comparing Groups
In all controlled studies, researchers try their best to gather identical groups. This process can be challenging and costly. While large medical schools generally have the funding to do this, our small group lacked that option. This was a major disadvantage for us.
As our study developed, we realized that patients in the group we treated (the CP Therapy Group) averaged 18 years older than untreated subjects. In addition, those in the CP Therapy Group had roughly double the number of prior surgeries, partial bowel obstructions, and years impacted with bowel symptoms than people in the Control Group.
The biostatistician noted statistical significance that the CP-treated patients:
Averaged 18 years older
54.5 vs 36.4
Averaged over twice as many prior surgeries
4.56 vs 2.07
Averaged over twice as many partial obstructions
3.97 vs 1.88
Averaged being impacted by SBOs for twice the number of years
10.7 vs 5.5
The Controls did report a few more prior total SBOs, but the numbers were considered so close that the biostatistician judged that statistically insignificant, 1.68 vs 2.17
Because patients in the Therapy Group had much more complex histories, the authors expected that group to do much worse than the Controls. Given the above, it is perhaps even more remarkable that after the study concluded, untreated patients had:
15 times more total obstructions,
2.5 times more partial obstructions, and
3 times as many surgeries as the ones treated by Clear Passage®.
[i] Scott JW, Olufajo OA, Brat GA, et al. Use of National Burden to Define Operative Emergency General Surgery. JAMA Surg. 2016;151(6):e160480. doi:10.1001/jamasurg.2016.0480
The most common cause of bowel obstructions is adhesions. In fact, 65%-75% of bowel obstructions are caused by adhesions. Adhesions are collagenous bands of scar tissue that form after some sort of trauma during the healing process. Think of it like a scab forming on your skin after a cut. Adhesions are internal “scabs” that assist in the healing of trauma; however, they can have serious side effects. These collagenous bands of scar tissue can wrap around your intestines and strangulate them, causing obstructions in the bowel. We usually use the metaphor of a hose that is being pinched shut. Adhesions can form following any type of trauma, for example, after infection, radiation therapy, or inflammation, and most commonly, they form after some type of surgery.
Adhesions form to help the body heal from surgery, infection, or trauma. After healing, adhesions can create strong glue-like bonds that last a lifetime.
Other, rarer causes of bowel obstruction are hernias, Crohn’s Disease, malignancy, volvulus, and diverticulitis. Hernias can squeeze the bowel shut, making it difficult or impossible for contents to pass through the intestines. Crohn’s Disease is a chronic inflammatory bowel disease. These persistent inflammations lead to scarring and, inevitably, the formation of adhesions through the never-ending inflammation of the delicate tissues. Malignancy, the presence of a tumor, can obstruct the intestine, causing blockage. Volvulus is an obstruction that occurs when the intestine is twisted or knotted. Diverticulitis is fairly similar to Crohn’s, an inflammation or infection in the digestive tract that can cause scar tissue (adhesions) and constipation.
Symptoms of a Small Bowel Obstruction
Nausea and vomiting
Constipation and inability to pass gas
Abdominal distention, which can be confused with bloating
Fever
Tachycardia (higher than normal resting heart rate)
Loss of appetite
Recurring or extreme abdominal pain
If you are experiencing several of these symptoms, it is important to notify your doctor. A bowel obstruction can be a life-threatening condition.
Here, you can see adhesions forming in different areas of the intestine, leading to a bowel obstruction
When a bowel obstruction occurs, doctors and physicians generally turn to surgery as the first option. But is it the best? What are the risks of surgery? Do you have options that are better suited for you? Below, we will discuss the risks and recovery of bowel obstruction surgery as well as other treatment options that are less well-known in the medical field.
Surgery
As written above, doctors generally turn to surgery as the “cure-all” for bowel obstructions. While this surgery is life-saving, it does come with some associated risks and validated concerns from patients. We now know that 65-75% of bowel obstructions are caused by internal adhesions. We also know that an internal trauma, such as a major abdominal surgery, will cause more adhesions. In fact, 90% of patients who undergo a major abdominal surgery develop adhesions. It seems somewhat counterintuitive that you would undergo surgery to treat adhesions causing your bowel obstruction, with a 90% chance of forming even more adhesions that will lead to another bowel obstruction following your surgery. It is important to note that surgery may be required in order to remove infected or necrotic (dead) tissue or to repair perforations to the bowel.
Risks Associated with Surgery/Side Effects of Surgery
7-day hospital stay recovery
Risk of developing more adhesions (scar tissue), leading to future bowel obstructions
There’s a much less-known treatment for bowel obstructions that involves no surgery, drugs, or medications to eliminate small bowel obstructions and assist you in gaining your life back after struggling with recurring bowel obstructions. For over two decades, Clear Passage® has been extremely successful in clearing bowel strictures by treating the root cause–adhesions–naturally. The Clear Passage® Treatment uses a hands-on approach by gently breaking apart the adhesions restricting your intestines over a 20-hour treatment course and educating you on how you can treat yourself after therapy. View our published studies and success rates in treating bowel obstructions here.
Risks Associated with Physical Therapy/Side Effects of Surgery
For most patients, side effects from this treatment have been transient and minimal, such as temporary minor soreness of the treated areas, soreness in other areas of the body following treatment, possible spotting for women after internal treatment, and fatigue.
Small Bowel Obstruction Prevention Options
Drink plenty of fluids: Drinking more water will help food move more easily through your digestive tract.
Chew your food thoroughly: Chewing your food thoroughly will decrease the amount of work your digestive tract must do, and help to prevent intestinal obstructions.
Diet Change: Changing your diet to be more digestive health-friendly may help prevent future small bowel obstructions. Read through our Digestive Health Guide for Bowel Obstructions to learn more.
Take note: Many of our patients have found it very helpful to keep a food journal. Learn what agrees with your stomach and what triggers your issues. Many people find it helpful to slowly reintroduce foods into their diet to make sure they can pinpoint what is causing the issue.
Don’t Let the Cost Keep You From Finding Out If Clear Passage® Can Help
You’ve probably already spent money on doctor visits, tests, medications, procedures, and treatments that didn’t give you the answer you were hoping for. The last thing you need is to finally find a treatment worth exploring and then have the cost stop you in your tracks.
Unlock the potential for pain-free movement and improved quality of life with Clear Passage® Physical Therapy’s Free Consult and Request Info – discover how their unique, non-surgical manual therapy approach can effectively treat fascial adhesions, addressing chronic pain, infertility, and various other symptoms without the risks of additional scar tissue formation. To learn more, visit our Apply to Therapy page.
What is Fascia?
Fascia, pronounced fah-sha, is an incredibly important but often misunderstood type of tissue in the body. Fascia is the most abundant connective tissue inside the body. A thin casing of connective tissue, fascia, wraps around and holds everything inside your body together, including muscles, organs, nerves, blood vessels, etc. On top of connecting every part of your body together, the fascia also has its own nerves that can make it as sensitive as skin, which is why it plays such a vital role in chronic pain conditions.
Although to the blind eye, fascia may look like a single piece of tissue, it is composed of several layers with fluid in between them called hyaluronan. The goal of this fluid is to allow frictionless movement between different structures of the body while you move, aiming to prevent injury.
How do Adhesions Affect Fascia?
Now that you are familiar with how fascia works, we’re going to talk about how adhesions or inflammation can reduce the effectiveness of fascia, creating mechanical dysfunction within the body.
As stated above, fascia is supposed to create a frictionless surface to allow structures, like joints, to move freely without pain. Inflammation can damage the surface of the fascia; subsequently, scar tissue is formed in order to repair the damaged tissue. The scar tissue, also known as adhesions, can sometimes cause abnormal attachments between body tissues, preventing the structures from functioning properly and eventually causing pain.
What are adhesions?
Adhesions, more commonly known as scar tissue, are tiny strands of collagen that form during the healing process. They can form after any kind of trauma or injury, such as inflammation, surgery, radiation therapy, or infection. You may have even formed adhesions when you fell off your bike as a child. Since everyone has developed adhesions throughout their life without even noticing, they usually don’t cause any issues. However, many people suffer from conditions caused by adhesions.
Fascial adhesions can restrict blood supply and damage nerves, leaving you with chronic pain and dysfunction. One of the most common conditions caused by fascial adhesions is carpal tunnel syndrome. Caused by repetitive strain, nerve pain develops in many people who spend long periods at the computer.
Once adhesions are formed, they are extremely difficult to get rid of. Adhesions restrict movement and cause damage to the surrounding area, triggering more inflammation. The increase in inflammation tells the body to send in more collagen links, resulting in even more adhesion development. Over time, as the movement of the area becomes more restricted, the adhesions harden and solidify. This can be easily witnessed in conditions like a frozen shoulder, where the shoulder is literally stuck in place due to scar tissue and adhesions restricting its mobility.
Now picture a more sensitive structure inside the body, like the bowel or fallopian tube. If adhesions can restrict the movement of the shoulder, they can easily cause a blockage in the bowel or a fallopian tube. Similar to the shoulder, adhesions (most commonly formed after an abdominal surgery or some type of pelvic infection like PID) will wrap around delicate organs and block the flow of material.
Common symptoms that mean you have adhesions
You are probably wondering if you have adhesions. Most likely, yes. If you have had a surgery, infection, sports injury, or some other form of physical trauma, you have adhesions. This becomes an issue when you start noticing chronic issues somewhere in the body. Adhesion-related disorders can manifest as chronic pain, infertility, or digestive problems.
Here are the main symptoms you should watch out for to establish if you have adhesions:
Did you answer yes to one or more of these symptoms? Do you also have a history of surgery, infection, or physical trauma? There is a very good chance your condition is being caused by fascial adhesions.
How do you treat fascial adhesions?
So you answered yes to the questions above. Now what? As I explained earlier, the body has no way to remove adhesions on its own. Once the adhesions have solidified and become attached to your fascia, they are stuck there until you seek some form of treatment. What are your treatment options?
Foam rolling – Depending on the severity of your condition, you can attempt foam rolling. The basic idea behind foam rolling is applying pressure with a moderately hard surface to the area where you have fascial adhesions. Although you can’t completely get rid of the adhesions, you can loosen and detach them to return mobility and decrease pain in the area.
Stretching routine – Since adhesions reduce the mobility and function of a muscle or the fascia in a surrounding area, stretching can be incredibly beneficial to relieve pain and restore mechanical function to the site of fascial adhesions. Similar to foam rolling, when you stretch consistently, the adhesions become loosened, and you will slowly regain an increased range of motion. Think of it as stretching an elastic waistband further and further each day; eventually, the elasticity will be reduced to almost nothing.
Medication –Sometimes medical intervention is necessary to relieve fascial adhesion symptoms. Many people experience chronic pain in association with fascial adhesions, so some form of pain medication or anti-inflammatory may be needed in conjunction with the above treatment methods. However, please note that medication only treats the symptoms of your fascial adhesions—not the root problem.
Lysis of adhesions – This is the surgical process of cutting adhesions to allow the mechanical function of the fascia or affected organs to be restored. Since surgery is the most common cause of adhesions, this method only provides temporary relief and isn’t a permanent solution. It can also cause more adhesions to form as the body uses internal scar tissue to repair itself from surgery.
Manual therapy – Manual therapy is an approach in which a highly trained physical therapist uses a specific treatment protocol to detach and loosen adhesions with their hands. This treatment is incredibly effective at treating conditions that are too advanced for a patient to treat themselves or as a replacement for surgical intervention. Since manual therapy is a non-surgical treatment, there isn’t the risk of additional adhesion formation as seen in the surgical intervention of conditions like infertility, bowel obstruction, or chronic pain. With more than 25 years of experience treating adhesive disorders, we have found this to be the most effective treatment.